She spent the first minute of Lecture 9 describing the exam before she touched the content. This is the most useful minute of audio in the block, so it is reproduced here rather than summarized away.
| What she said | What it means for revising |
|---|---|
| “There’s gonna be like clinical vignettes or pretty much all clinical vignettes … make sure that you are able to recognize conditions by the vignette.” | The vignette sets are the format-matched practice. Every topic on this site has two of them alongside its two recall quizzes. The recall quizzes are for learning the facts; the vignette sets are for sitting the paper. If you only have time for one, do the vignettes. |
| “There might be some question, what’s the most likely diagnosis, but a lot of them are — what’s the next management plan? What’s your first line treatment plan? … what’s the proper patient education?” | Naming the disease is the easy half. Most marks sit in what you do next. The vignette sets are now built to that shape — diagnosis is capped at 6 of 30, and education, treatment and next-step lead-ins outnumber it. |
| “There are some pictures, but I would say way more non-pictures than pictures — but there’s a couple.” | A couple of image questions, so the photographs in this guide and in the comparison chart are worth a pass, but they are not where the paper lives. |
| “65 questions, and I think that’s everything.” | Note the master exams here are 5 forms of 60, which is this site’s standing format rather than a guess at hers. Sixty-five is the real paper. |
She also said, three times, which question she is going to write. On squamous cell carcinoma: “what’s our diagnostic testing? We’re biopsying it … I should definitely give you a question on that.” On melanoma: “Biopsy, great. I’m totally gonna write a question for that. I haven’t done these questions yet.” On cutaneous T-cell lymphoma: “you guys know that question for everyone for this lecture at least … do a biopsy is how you’re gonna diagnose this.”
The answer is never just “biopsy”, though, because the slides never say that. Squamous cell needs depth enough to separate in situ from invasive. Basal cell is shave or punch. Kaposi needs a representative lesion with human herpesvirus 8 findings. Cutaneous T-cell lymphoma needs an active, representative, untreated lesion, possibly several, and a single nondiagnostic biopsy does not exclude it. Section 9 covers each, and the quizzes now ask all of them.
1 · Clinical Reasoning and Problem Solving
Instructional Objectives
- Compare and contrast sensitivity and specificity.
- Define pretest probability.
- Define posttest probability.
- Discuss clinical principles and decision-making.
- Discuss the naturalistic approach.
- Compare and contrast screening and diagnostic testing.
- Discuss the implications for treatment.
- Recall counseling strategies to help patients adhere to treatment plans, including behavior modifications
1.1 · Objective a — Compare and contrast sensitivity and specificity
| Sensitivity | Specificity | |
|---|---|---|
| Definition | Probability the test shows a person has the condition when they do have it | Probability the test shows a person does not have the condition when they do not have it |
| In one phrase | How well a test detects disease | How well a test excludes disease |
| Reduces | False-negatives | False-positives |
| Says nothing about | False-positives | False-negatives |
| Memory aid | SnNout — high Sn, Negative result, rules out | SpPin — high Sp, Positive result, rules in |
| Best used for | Screening | Confirming a diagnosis |
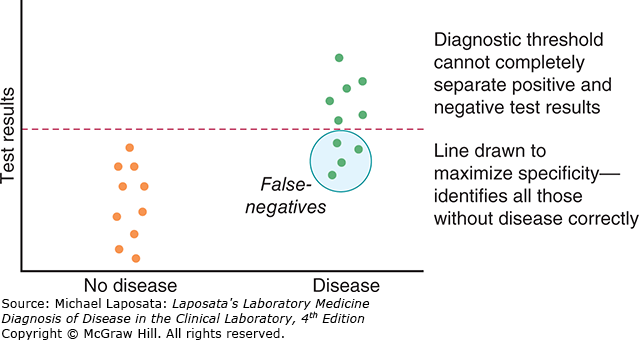
The worked example. Screening for human immunodeficiency virus (HIV) uses a highly sensitive test so that very few infected individuals are missed; confirmatory (supplemental) testing is highly specific, which minimizes false-positive diagnoses. The lecture's justification is worth keeping, because it is a judgment rather than a rule: it is better to accept a few false-positives that a confirmatory test can later correct than to fail to identify people who might unknowingly infect others. That trade flips for a disease that is serious and not curable — in cancer diagnosis a false-positive is catastrophic for the patient.
Conditional probability is the umbrella idea underneath all of this: the probability of a disease or event if another event, test result, or condition is present.
Also tested
- Sensitivity. It is related to fewer false-negatives and does not address false-positives.
- Highly sensitive test. A negative result is most useful for ruling the disease out in that patient (SnNout: high Sensitivity and a Negative result help rule out a disease).
- False-positives in human immunodeficiency virus (HIV) screening. A few are acceptable because they can be corrected by later confirmatory testing, whereas a missed case may unknowingly infect others.
1.2 · Objectives b & c — Define pretest and posttest probability
| Pretest probability | Posttest probability | |
|---|---|---|
| Definition | Likelihood of the condition before the test result is known | Likelihood of the condition after the test result is known |
| Built from | Signs and symptoms · history and risk factors · how common the condition is in the population | The pretest estimate, revised by the test's sensitivity and specificity |
Also tested
- Posttest probability. Posttest probability is the likelihood after the result is known, the pretest likelihood revised by the test's sensitivity and specificity; with identical tests, different pretest probabilities give different posttest probabilities.
- Pretest versus posttest probability. Pretest probability is estimated from signs, symptoms, history and frequency; posttest probability additionally reflects the test result.
1.3 · Objective f — Compare and contrast screening and diagnostic testing
| Screening testing | Diagnostic testing |
|---|---|
| Identifies the likelihood of occult disease | Complements the history and physical examination Reduces uncertainty about diagnosis and/or prognosis Helps decide management |
1.4 · Objective d — Discuss clinical principles and decision-making
The clinical reasoning process, in six steps.
| Step | What happens |
|---|---|
| 1 | Gather initial patient information |
| 2 | Organize and interpret clinical information |
| 3 | Synthesize clinical information and develop the problem representation |
| 4 | Generate hypotheses |
| 5 | Test hypotheses and establish a working diagnosis |
| 6 | Plan the diagnostic and treatment strategy |
The three questions a clinician has to answer: what disease does the patient have, should testing be done, and should this patient be treated? Clinical decision-making covers what information to gather, what diagnostics to order, how to interpret and integrate what comes back, and what management the patient needs.
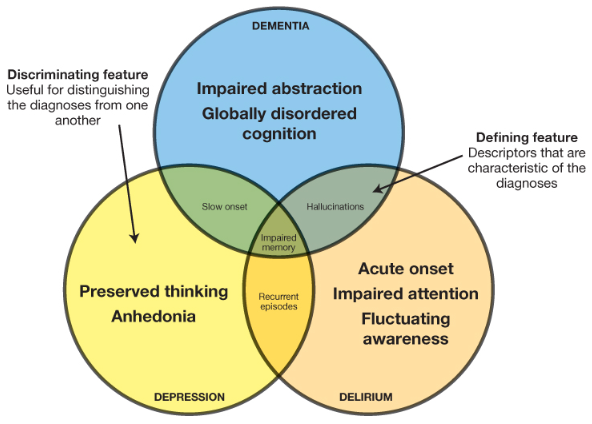
Building a differential. Start from the signs and symptoms and ask which organ or system is involved — for shortness of breath, is this cardiac, pulmonary or hematologic? Then consider the anatomy of those systems. When stuck, run a checklist mnemonic.
| VINDICATE | Worked example — chief complaint of “confusion” |
|---|---|
| Vascular | Stroke, transient ischemic attack, subarachnoid hemorrhage |
| Infectious | Meningitis, encephalitis, sepsis |
| Neoplastic | Primary brain tumor or metastasis |
| Degenerative | Alzheimer's disease, Huntington's disease, other dementias |
| Iatrogenic / intoxication | Narcotics, alcohol intoxication or withdrawal |
| Congenital | Epilepsy (post-ictal state) |
| Autoimmune | Central nervous system lupus, neurosarcoidosis, anti-NMD encephalitis |
| Trauma | Traumatic brain injury, traumatic epidural or subdural hematoma |
| Endocrine (metabolic) | Hypoglycemia, hypo- or hyperthyroidism, hypo- or hypernatremia, hypercalcemia, hepatic or uremic encephalopathy |
The alternative organ-system checklist is “Tom G. Prince, MD, Psychiatrist, General Hospital”: Toxin/Trauma (including medications), Oncologic, Musculoskeletal/rheumatologic, Gastrointestinal, Pulmonary, Renal, Infectious, Neurologic, Cardiovascular, Endocrine, Metabolic/Genetic, Dermatologic, Psychiatric, Genitourinary/Gynecologic, Hematologic.
The hypothetico-deductive method — proposing hypotheses and testing whether they are acceptable by deciding whether the data is consistent with what is observed.
| Stage | What it does |
|---|---|
| Cues | Initial history · initial examination · screening diagnostic testing |
| Hypothesis generation | List potential diagnoses triggered by patient cues |
| Hypothesis evaluation | Gather data to confirm or exclude those hypotheses |
| Hypothesis refinement | Add new hypotheses triggered by the data gathered |
| Hypothesis verification | Confirm the “fit” of the hypotheses with the assembled data |
| Patient management | Gather data to monitor the patient's response |
Two modes of thinking. In straightforward or common situations clinicians use an intuitive system — quick, automatic, pattern-based. Pattern recognition is easy to use but is the lowest level of decision making, and it errs precisely because other possibilities are never considered. Complex situations call for a deliberate, controlled process using logic and probabilities: evidence-based medicine, clinical guidelines, and quantitative techniques.
| Analytic method | How it runs, and where it falls short |
|---|---|
| Evidence-based medicine | Formulate a clinical question → gather evidence (literature review, MEDLINE, UpToDate) → evaluate its quality and validity → decide how to use it. Limitations: time consuming, and many clinical questions have no relevant studies. |
| Clinical guidelines | Common practice, often an “if then” rule — if a patient is febrile and neutropenic, then use broad-spectrum antibiotics. Straightforward, cost-effective, the “standard of care”. Caution: apply only to patients with similar characteristics. |
| Quantitative techniques | Odds and probability — the sensitivity, specificity and pre/posttest material above. |
Suggestions for good decision-making: slow down; be aware of the base rate of disease for the diagnoses on your differential; consider what data is truly relevant; actively seek alternative diagnoses; ask questions to disprove rather than confirm your current hypothesis; and remember you are often wrong, considering the immediate implications of that.
Also tested
- VINDICATE mnemonic. A category-based differential framework: vascular, infectious, neoplastic, degenerative, iatrogenic, congenital, autoimmune, trauma, and endocrine or metabolic.
- Common things occur commonly. Bet on uncommon manifestations of common conditions rather than common manifestations of uncommon conditions: when you hear hoof beats, think horses, not zebras. An unusual presentation of a common condition is more probable than a textbook presentation of a rare one.
- Clinical guideline. A clinical guideline following an if-then rule, for example: if a patient is febrile and neutropenic, then use broad-spectrum antibiotics.
- Three questions a clinician must answer. What disease is present, should testing be done, and should this patient be treated. Which clinician should take over the patient's care is not among them.
- Clinical decision making. Setting the sensitivity and specificity of the tests available is not part of it; these are fixed properties of a test, not decisions a clinician makes at the bedside.
- Clinical guideline caution. Guidelines are straightforward and easy to use but should be applied to patients with similar characteristics to those studied.
- Clinical reasoning first steps. Gather initial patient information, then organize and interpret it, then synthesize it into a problem representation, before hypotheses are generated and tested.
- Good clinical decision-making. Remember you are often wrong, and consider the immediate implications; also slow down, weigh base rates, consider what data is truly relevant, and seek alternatives.
1.5 · Objective e — Discuss the naturalistic approach
The naturalistic (event-driven) approach means treating signs and symptoms before a definitive diagnosis. It is used mostly in emergency medicine, for:
- Unstable patients
- Atypical presentations
- Ruling out the worst-case scenario
- Following responses to interventions
Also tested
- Naturalistic (event-driven) approach. It is characterized by treating signs and symptoms before a definitive diagnosis is reached.
- Naturalistic approach. It suits unstable patients and atypical presentations, along with ruling out the worst-case scenario and following responses to interventions.
1.6 · Objective g — Discuss the implications for treatment
To treat versus not to treat. The value of treatment versus no treatment is a linear function of the probability of disease, weighed alongside the likelihood of success and the patient's ability to tolerate treatment.
Risk versus benefit. Because a diagnosis almost always carries some uncertainty, the decision to treat has to balance the benefit of treating a sick person against the risk of erroneously treating a well person, or one with a different disorder. Benefit and risk encompass both financial and medical consequences, and the balance must account for both the likelihood of disease and the magnitude of the benefit and the risk.
Also tested
- Treating despite diagnostic uncertainty. The value of treatment versus no treatment is a linear function of the probability of disease, together with the likelihood of success and the ability to tolerate treatment, weighed as risk against benefit.
1.7 · Objective h — Recall counseling strategies to help patients adhere to treatment plans
Providers must be able to communicate evidence on prognosis, treatments, diagnostic testing and prevention, so patients understand their risks and options.
| Framework | Elements |
|---|---|
| Five As | Ask · Advise · Assess · Assist · Arrange |
| FRAMES | Feedback about personal risk · Responsibility of the patient · Advice to change · Menu of options · Empathetic style · promote Self-efficacy |
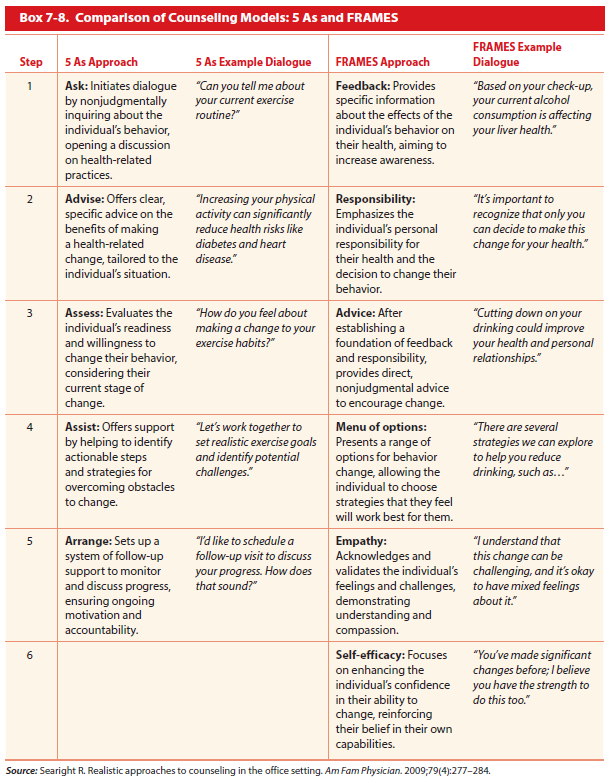
Specific counseling guidelines for adults on unhealthy alcohol use, tobacco smoking cessation and sexually transmitted infections are in Bates' Chapter 7.
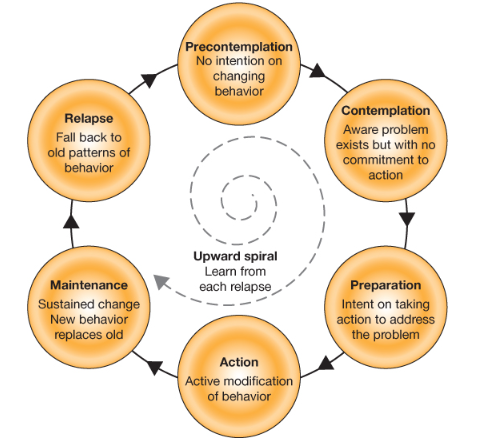
Behavior modification. Changing behaviors is difficult, and behavioral counseling is one of the most important skills for helping patients make those changes. Identify where your patient sits on the continuum of behavior change, and tailor interventions to their readiness and self-efficacy.
| Barriers to treatment and medication adherence | |
|---|---|
| Cost and affordability of medications or services | Low health literacy or lack of understanding |
| Cultural or religious beliefs about treatment | Fear of side effects or mistrust of providers |
| Transportation or time constraints | Mental health challenges or cognitive impairment |
| Poor communication or follow-up by the care team | |
Also tested
- Tzanck smear. It gives rapid evaluation of vesicular lesions for herpesvirus cytologic changes. Polymerase chain reaction is preferred for confirmation: the smear is fast, the polymerase chain reaction is definitive.
- Barriers to treatment and medication adherence. Cost and affordability of medications or services, low health literacy or lack of understanding, and cultural or religious considerations.
- Barriers to treatment and medication adherence. Mental health challenges or cognitive impairment are listed among the barriers, alongside cost, low health literacy, cultural or religious beliefs, fear of side effects, transportation and poor follow-up.
- FRAMES elements. Responsibility of the patient is the element that places the decision to change with the patient; FRAMES also includes feedback, advice, a menu of options, an empathetic style and promoting self-efficacy.
2 · General Dermatology I
Instructional Objectives
- Review anatomy of the integumentary system
- Review physiology of the integumentary system
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following dermatological conditions:
- Eczema
- Diaper
- Nummular
- Periorbital
- Dyshidrosis
- Dermatitis
- Atopic
- Diaper
- Stasis
- Contact
- Seborrheic
- Perioral
- Xeroderma
- Vesiculobullous disease
- Bullous pemphigoid
- Pemphigus
- Psoriasis
- Pityriasis rosea
- Lichen planus and lichen simplex dermatitis
- Alopecia
- Areata
- Androgenetic
| She said | What it means for the exam |
|---|---|
| “I am going to expect you to know names from my class — I'm gonna be very clear which names — but I'm not expecting necessarily to know all the doses.” | Learn the agents she names. Do not memorize dosing. |
| “I would not make you guys memorize hundreds of brands of steroids.” | Only the seven agents on the potency table below are in scope. |
| On the NAAT and polymerase chain reaction hierarchy: “This is not going to be on your exam. This is just to help you for the future.” | Slides 30 and 31 are background. Know that a viral polymerase chain reaction detects viral genetic material; the taxonomy of RT-PCR, qPCR and multiplex is not examinable. |
| On the Tzanck smear and mineral oil preparation: “I've never seen this used clinically, however you need to know it because it could be on your board.” | Both are in scope despite being clinically obsolete. |
| “Make sure when you go over the PowerPoints, read headers — that's really important, because I'm separating here.” | The slide headers carry the organizing structure of the material. |
| “These are like how your PANCE-style questions will be, so I want to make sure you guys understand what the expectation is.” | The four Knowledge Check vignettes at the end of the deck are the format of her exam questions. She worked all four in class. |
One line was left out deliberately. Answering a student question about image interpretation she said either “I would” or “I wouldn't actually have you interpret the picture” — two independent transcriptions disagree on the negation, and the student's question itself is inaudible. Since getting it wrong would mean telling you to skip something, treat images as fair game until she confirms otherwise.
Source: General Dermatology I lecture recording, 2026-08-19.
2.1 · Objectives a & b — Review anatomy and physiology of the integumentary system
The skin is the largest organ of the body, and everything in this block rests on knowing which layer a disease sits in. The three layers, outermost first:
| Layer | What is in it | Why it matters clinically |
|---|---|---|
| Epidermis | Keratinocytes in five strata, melanocytes, Langerhans cells, Merkel cells. Avascular — fed by diffusion from the dermis. | Impetigo, pemphigus and the superficial fungal infections live here. Loss of this layer alone means no scarring. |
| Dermis | Collagen and elastin, blood vessels, nerves, hair follicles, sebaceous and sweat glands. | Erysipelas, cellulitis and bullous pemphigoid involve this layer. Damage here scars. |
| Subcutaneous tissue | Fat, larger vessels, the base of the follicles. | Furuncles, abscesses and panniculitis such as erythema nodosum sit at this depth. |
Physiology. The skin provides a barrier against water loss, chemicals and microorganisms; regulates temperature through vasodilation, vasoconstriction and sweating; carries the sensory apparatus for touch, pressure, temperature and pain; synthesizes vitamin D under ultraviolet B; and performs immune surveillance through Langerhans cells.
2.2 · Objective c — The eczema and dermatitis family
Eczema and dermatitis name the same reaction pattern. What distinguishes the members is distribution, trigger and age rather than the appearance of an individual lesion.
| Condition | Who and where | The defining feature |
|---|---|---|
| Atopic dermatitis | Infants on cheeks and extensors; children and adults in flexures | Personal or family atopy — asthma, hay fever, food allergy |
| Contact dermatitis | Anywhere the contactant touched | Sharp margins in the shape of the exposure; patch testing identifies it |
| Seborrheic dermatitis | Scalp, eyebrows, nasolabial folds, ears, central chest | Greasy yellow scale on erythema in sebum-rich sites |
| Nummular eczema | Extremities, often older adults | Discrete coin-shaped plaques |
| Dyshidrotic eczema | Palms, soles, sides of fingers | Deep-seated tapioca-like vesicles, intensely itchy |
| Stasis dermatitis | Lower legs, gaiter area, bilateral | Venous insufficiency with edema and hemosiderin pigmentation |
| Diaper dermatitis | Convex surfaces of the napkin area | Spares the skin folds; candidal overgrowth involves them with satellite lesions |
| Perioral dermatitis | Around the mouth, sparing the vermilion border | Often follows topical corticosteroid use on the face |
| Periorbital dermatitis | Eyelids and around the eyes | Thin skin, so potent steroids are avoided |
| Xeroderma | Shins and forearms, worse in winter | Dry cracked skin from impaired barrier function |
What these look like
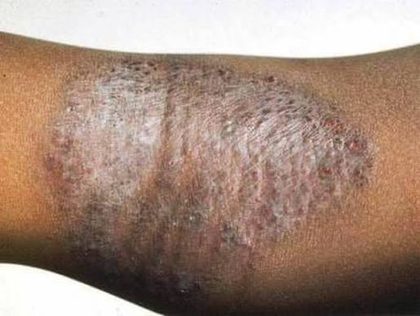
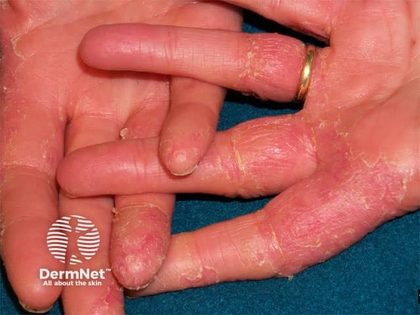
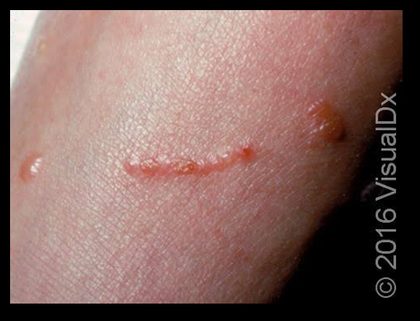
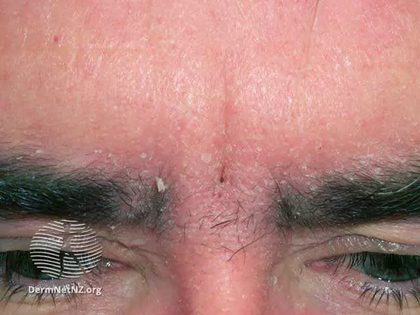
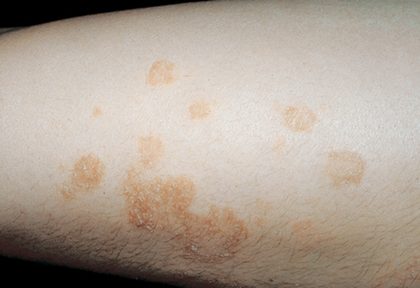
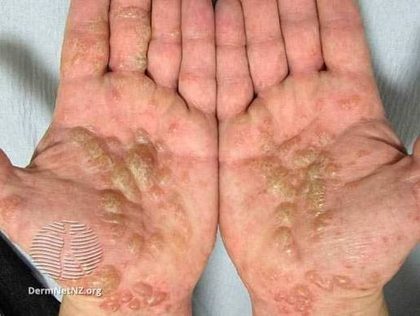
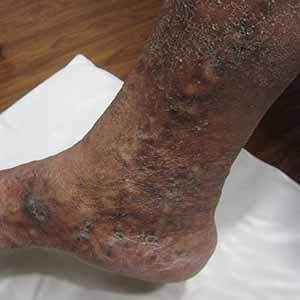

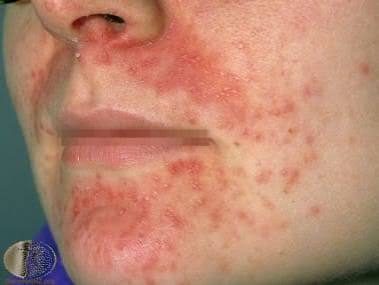
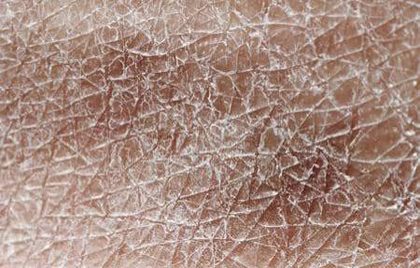
She spent real time on this and was direct about why. “All the descriptions, all the textbooks, and what you're gonna be tested on, is gonna describe the rash on Caucasian skin. This is not a Dr Jaquith thing, this is a medicine thing, this is a history thing — medicine has not been nice to minorities. It is really important that you know how to identify all of these on every single skin type.” She noted she had sourced images across ethnic groups for every condition in the deck bar one.
| Condition | On lighter skin | On darker skin |
|---|---|---|
| Atopic dermatitis | Angry, inflamed, clearly erythematous | Can appear almost silvery; erythema is far less obvious |
| Stasis dermatitis | Erythematous patches in the gaiter region | Erythema appears violaceous, gray or deep brown; palpate for warmth and edema rather than relying on color |
| Pityriasis rosea | Salmon-colored lesions, resolving without mark | Post-inflammatory hyperpigmentation that can persist for months |
| Lichen planus | Pink to violaceous flat-topped papules | Violaceous shades read as darker; the flat-topped, shiny quality and Wickham striae carry more weight than color |
The practical consequence: on darker skin, stop using erythema as the primary signal and rely on palpation, distribution, lesion shape and secondary change instead. She also raised the Fitzpatrick scale here as the way skin type is classified.
Source: lecture recording, 2026-08-19, with 2. General Dermatology I.pptx, Slides 114, 169 and 176.
Also tested
- Resistant dermatophytosis. Suspect it when disease is widespread, intensely inflammatory, epidemiologically linked, or refractory to an adequate terbinafine course; obtain species identification and susceptibility testing when available.
- Severe or extensive allergic contact dermatitis. Treat with high-dose oral corticosteroids tapered over two to three weeks, because early discontinuation causes high rates of rebound; limited eruptions can be managed with high-potency topical steroids.
- Urushiol lesions. They are intensely pruritic vesicular lesions in linear distributions, erupting within 4 to 96 hours and persisting up to 3 weeks; the linear pattern comes from grazing the plant in passing.
- Seborrheic dermatitis treatment. The mainstay is topical antifungals such as ketoconazole, with steroids used early to reduce inflammation; scalp disease uses ketoconazole or selenium sulfide shampoo, and facial disease uses ketoconazole cream or lotion.
- Stasis dermatitis priorities. The two primary clinical priorities are distinguishing it from cellulitis, and determining whether compression therapy can be used safely.
- Irritant versus candidal diaper rash. Fold involvement separates them: irritant disease affects convex surfaces and generally spares the inguinal folds, while candidal disease gives beefy erythema in the folds with satellite papules and pustules.
- Tinea corporis versus nummular eczema. Both are red or pink itchy circular patches. Tinea corporis is a fungal infection that is annular and clears centrally; nummular eczema is non-infectious and coin-shaped without central clearing.
- Stasis dermatitis red flag. Acute unilateral swelling or pain should raise concern for deep venous thrombosis, particularly when it is a new unilateral change on chronic bilateral changes.
- Atopic dermatitis diagnosis. Diagnosis is usually clinical, supported by family history, personal history of atopy and recurrent rash. Immunoglobulin E may be elevated but is not routinely tested, and routine laboratory testing is not required.
- Irritant reaction timing. Mild irritants such as soaps may cause subacute symptoms progressing over weeks; alkalis and acids may present minutes after exposure or delayed up to 24 hours or more. Concentrated agents can cause chemical burns and necrosis.
- Perioral dermatitis versus acne vulgaris. Open or closed comedones point to acne vulgaris; perioral dermatitis produces grouped monomorphic papules, papulovesicles or papulopustules without comedones.
- Emollient use in atopic dermatitis. Apply emollient to the skin after rinsing, avoid irritants, and keep skin care fragrance-free. Clinicians should also demonstrate medication quantity and correct application.
- Toxicodendron (urushiol) dermatitis. Urushiol sap produces intensely pruritic vesicular lesions in linear distributions. Lesions erupt within 4 to 96 hours and may appear in multiple stages.
- Contact dermatitis pattern. It is often distinguishable from other dermatologic conditions by its clearly demarcated, unnatural patterns, tracing the shape of whatever touched the skin rather than a biological distribution.
- Contact dermatitis versus cellulitis. Contact dermatitis is itchy with vesicles and no fever, whereas cellulitis is tender and warm rather than itchy.
- Atopic dermatitis epidemiology. About 20% of children worldwide are affected, and it is more common in males. It often begins in infancy or childhood; adult-onset disease occurs but is rare.
- Allergic contact dermatitis cause. The most common cause is urushiol sap from Toxicodendron species, and approximately 50 to 75% of people in the United States react to it, which explains why not everyone who contacts poison ivy, sumac or oak reacts.
- Xerosis. It reflects impaired stratum-corneum hydration, promoted by aging, low humidity, hot water, detergents, atopy and systemic disease. It commonly affects older adults, especially in winter, causing tightness, pruritus, rough scale, fissuring or eczema.
- Nummular eczema plaques. They are intensely pruritic, round coin-shaped, light pink, scaly, thin plaques 1 to 10 cm, uniform without central clearing, most commonly on the extremities though they can occur on the trunk.
- Atopic dermatitis education. Apply emollient after rinsing, avoid irritants, use fragrance-free skincare, demonstrate quantity and application, and give a written flare and infection action plan. Corticosteroid concerns are addressed directly rather than avoided.
- Extensive allergic contact dermatitis. When the eruption is extensive rather than limited, high-dose oral corticosteroids replace the high-potency topical steroid used for limited disease. Soothing measures such as oatmeal baths and cool compresses are used throughout.
- Atopic dermatitis prognosis. The disease is chronic and relapsing, but many patients improve with age; it may improve, persist or recur.
- Irritant contact dermatitis timing. Mild irritants such as soaps may progress over weeks, while alkalis and acids may present within minutes or be delayed up to 24 hours or more. The agent determines the tempo.
- Counseling for atopic dermatitis steroid worries. Address the concern directly, review the side effects, demonstrate how much to apply, and provide a written flare and infection action plan.
- Chronic hand dermatitis from detergent exposure. Avoid the exposure and repair the barrier with emollients, sleeping in cotton gloves after applying a heavy emollient such as petroleum jelly, with antihistamines such as hydroxyzine or diphenhydramine for itch.
- Stasis dermatitis with acute leg swelling. Acute unilateral swelling or pain should raise concern for deep venous thrombosis, so order venous duplex ultrasonography to evaluate for it.
- Childhood atopic dermatitis treatment. A flexural distribution (antecubital and popliteal fossae) with family atopy history is classic. Initial treatment is topical hydrocortisone with regular emollient use: a low-potency steroid plus barrier repair is first line.
- Allergic contact dermatitis to adhesives. A rash that reproduces the shape of the object is the hallmark. A rectangular rash sparing a central area reflects a reaction to the adhesive in the dressing, with the spared center corresponding to the cotton pad.
- Nickel allergy. Nickel is the most common metal allergen, and eruptions reproduce the shape of the item worn, such as under a necklace or beneath a jeans button.
- Greasy scaling of the scalp and face. Initial treatment is ketoconazole shampoo and topical ketoconazole cream. Topical antifungals are the mainstay because Malassezia overgrowth drives the condition; steroids may be added early to reduce inflammation.
- Recurrent greasy scaling of the scalp and nasolabial folds. The condition is chronic and relapsing, so repeated and long-term use of medication is often required.
- Culture in atopic dermatitis. Bacterial culture is indicated for purulent, pustular or significantly crusted lesions, such as weeping, thickly crusted plaques with pustules, to rule out infection.
- Infantile atopic dermatitis. Weeping inflammatory patches and crusted plaques on the cheeks, scalp, and extensor surfaces; rubbing commonly replaces scratching at this age. Roughly 80 percent of patients have a personal or family history of atopy.
- Allergic contact dermatitis. It is an immunologic cell-mediated, delayed, type IV hypersensitivity reaction, most often to urushiol, the sap of Toxicodendron species (poison ivy, sumac, oak); roughly 50 to 75 percent of people in the United States are allergic.
- Patch testing. It is the diagnostic test for atypical, adult-onset or treatment-resistant eczema, and eyelid and hand involvement raises contact allergy.
- Irritant contact dermatitis. The eyelids and face are among the commonest sites, from makeup and masks, with a glazed, well-demarcated appearance.
2.3 · Objective c — Vesiculobullous disease
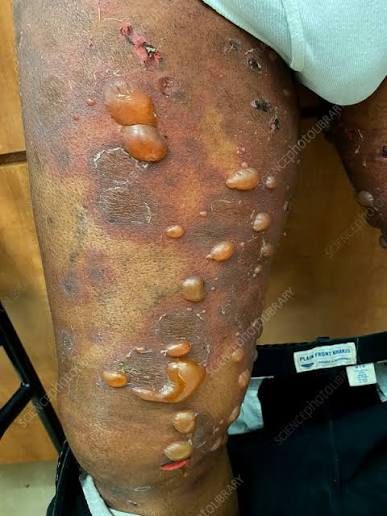
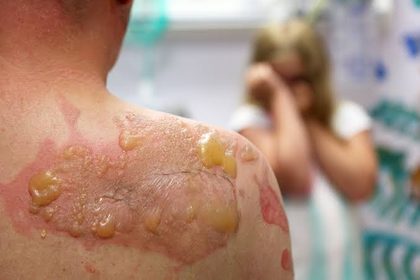
| Bullous pemphigoid | Pemphigus vulgaris | |
|---|---|---|
| Age | Elderly | Middle-aged |
| Split level | Subepidermal — below the whole epidermis | Intraepidermal — within the epidermis |
| Bullae | Tense, do not rupture easily | Flaccid, rupture easily leaving erosions |
| Nikolsky sign | Negative | Positive |
| Mucosal involvement | Uncommon | Common, often the first site |
| Prognosis | Better | Worse; was frequently fatal before corticosteroids |
What these look like
Also tested
- Prodromal bullous pemphigoid. Weeks of intense itching with pruritic urticarial or edematous lesions and no blisters may be the prodromal phase, which may precede bullae by weeks to months.
- Bullous pemphigoid diagnosis. Biopsy the lesion for histopathology and perilesional tissue for direct immunofluorescence. Serum indirect immunofluorescence or enzyme-linked immunosorbent assay can identify anti-basement membrane zone antibodies.
- Pemphigus mechanism. Autoantibodies to adhesion molecules cause loss of keratinocyte-to-keratinocyte adhesion, called acantholysis, producing intraepithelial blisters in a life-threatening blistering disorder of skin and mucous membranes.
- Light microscopy in bullous pemphigoid. Neutrophils are aligned in a straight narrow row at the dermal-epidermal junction. Biopsy a lesion for histopathology and perilesional tissue for direct immunofluorescence.
- Confirming bullous pemphigoid. Biopsy of perilesional tissue for direct immunofluorescence confirms the diagnosis. Lesional tissue goes for histopathology, with serum studies or ELISA identifying anti-basement membrane zone antibodies.
- Acantholysis. On biopsy of flaccid skin bullae with painful oral erosions, it is the defining histological feature: loss of keratinocyte-to-keratinocyte adhesion. Immunofluorescence and serum ELISA are confirmatory.
- Pemphigus treatment. Pemphigus is life-threatening, so treatment is urgent: rituximab or high-dose oral prednisone. A steroid-sparing agent is usually added so steroids can be tapered.
- Nikolsky sign. A positive sign is when the top layers of skin slip away or slough off from the lower layers when rubbed; it is positive in pemphigus and negative in bullous pemphigoid.
2.4 · Objective c — Papulosquamous disease
| Condition | Lesion | Distribution and course |
|---|---|---|
| Psoriasis | Well-demarcated plaques with thick silvery scale; Auspitz sign on removal | Extensor surfaces, scalp, nails; chronic and relapsing |
| Pityriasis rosea | Herald patch first, then smaller oval lesions with a collarette of scale | Christmas-tree pattern along skin lines on the trunk; self-limiting over 6 to 8 weeks |
| Lichen planus | Purple, polygonal, pruritic, planar papules; Wickham striae on the surface | Flexor wrists, ankles, oral mucosa |
| Lichen simplex chronicus | Thickened lichenified plaque with accentuated skin markings | Wherever the patient can reach to scratch; the itch-scratch cycle sustains it |
What these look like
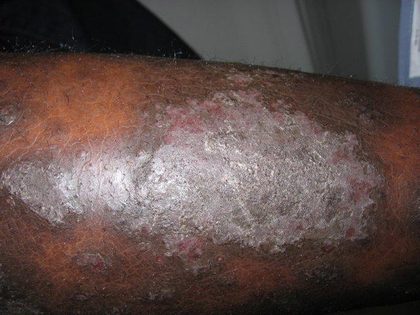
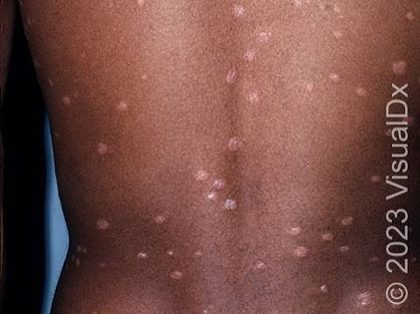
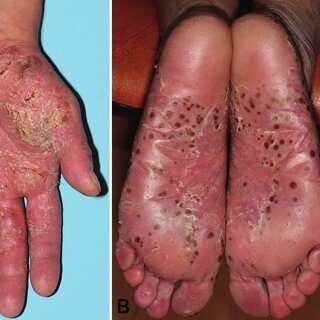
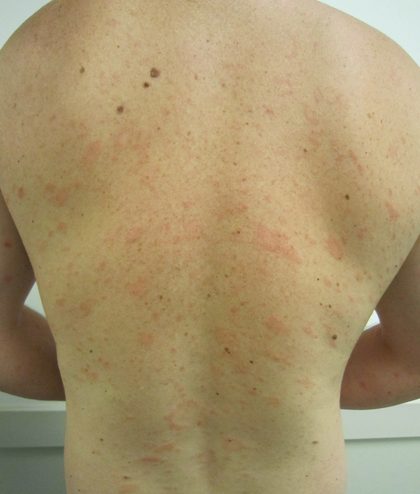
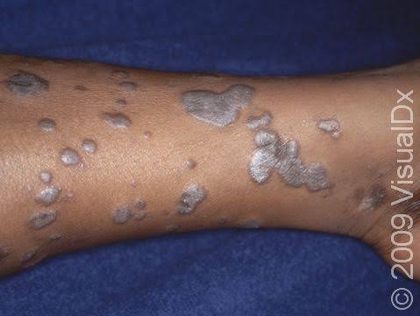
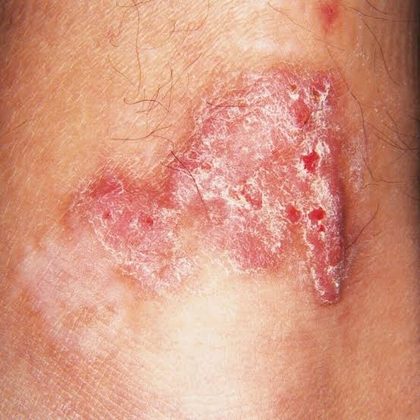
The six Ps for lichen planus — purple, polygonal, pruritic, planar, papules and plaques — is worth memorizing because the description alone is close to diagnostic.
Also tested
- Psoriatic arthritis radiograph. The expected finding is a pencil-in-a-cup deformity; psoriatic arthritis is associated with HLA-B27 and affects the distal and proximal interphalangeal joints while sparing the metacarpophalangeals.
- Pityriasis rosea course. It is self-limited and typically fades over 4 to 6 weeks, though darker skin may show post-inflammatory hyperpigmentation for several months; reassurance is the mainstay, with antihistamines or topical steroids used cautiously for itch.
- Von Zumbusch pustular psoriasis. A rare, severe, abrupt and life-threatening form associated with other forms of psoriasis; it may follow systemic steroid withdrawal, begins with several days of fever, and is commonly mistaken for bacterial or viral infection.
- Impetigo herpetiformis. The psoriasis of pregnancy, typically in the third trimester, with erythematous patches whose margins are studded with subcorneal pustules. Onset brings fever, chills, malaise, diarrhea, nausea and arthralgia.
- Psoriasis heredity. About 8 percent of children are affected when one parent has psoriasis and 41 percent when both do, reflecting a genetic predisposition in which PSORS1 is the major susceptibility locus.
- Pityriasis rosea management. It is self-limited, so reassurance is the mainstay, with oral antihistamines or topical steroids used cautiously for pruritus. Ultraviolet B phototherapy or sunlight helps if begun in the first week; severe cases may be treated with acyclovir.
- Lichen planus histology. Biopsy shows a band-like lymphocytic infiltrate in the dermis, plus hyperkeratosis without parakeratosis, basal layer vacuolisation, Civatte bodies in the lower epidermis and saw-tooth shaped rete ridges.
- Guttate psoriasis. It presents as raindrop-shaped erythematous papules and plaques in children, typically 2 to 3 weeks after a streptococcal infection or upper respiratory infection. It often needs no treatment, though phototherapy and topical steroids may be used.
- Lichen planus histology. A biopsy shows a band-like infiltration of lymphocytes in the dermis, a classic descriptive phrase worth recognizing on sight.
- Herald patch. It is a single 2 to 5 cm round or oval, sharply demarcated pink or salmon plaque on the chest, neck or back, occurring in 50 to 90% of cases. It precedes the general eruption by one to two weeks.
- Lichenoid drug reactions. Nonsteroidal anti-inflammatory drugs, sulfonamides, tetracyclines, hydrochlorothiazide, quinidine and some beta blockers can produce them. Ask about these, since the eruption can mimic idiopathic lichen planus.
- Von Zumbusch pustular psoriasis. Onset is abrupt and life-threatening: several days of fever, then generalized 2 to 3 mm pustules over trunk and extremities, including nail beds, palms and soles, that may form lakes of pus. It may follow systemic steroid withdrawal.
- Lichen planus biopsy. The confirming finding is a band-like infiltration of lymphocytes in the dermis, with hyperkeratosis without parakeratosis, basal vacuolization, Civatte bodies and a saw-tooth rete ridge.
- Lichen planus counseling. Genital and erosive oral disease carry an increased risk of squamous cell carcinoma, so ongoing surveillance is needed. This is why mucosal involvement must be identified and followed.
- Lichenoid eruption after a new medication. Review the medication list, since several drugs produce lichenoid reactions: nonsteroidal anti-inflammatory drugs, sulfonamides, tetracyclines, hydrochlorothiazide, quinidine and some beta blockers.
- Oval scaly plaque followed by smaller oval lesions down the trunk. Diagnosis is clinical, based on the herald patch and the typical pattern. The herald patch and cleavage-line distribution are enough.
- Guttate psoriasis. No specific treatment is required, though phototherapy or topical steroids may be used. It often needs no treatment.
- Diagnosing psoriasis. It is generally a clinical diagnosis, though skin biopsy may be needed for definitive diagnosis, for example when the picture is not clear-cut and treatment has failed.
- Four Ps of lichen planus. Pruritic, purple, polygonal, papules or plaques: flat-topped, pink to violaceous and shiny, coalescing into larger plaques.
2.5 · Objective c — Alopecia
| Alopecia areata | Androgenetic alopecia | |
|---|---|---|
| Pattern | Discrete smooth round patches of complete loss | Gradual thinning — temporal recession and vertex in men, widened part in women |
| Mechanism | Autoimmune attack on the hair follicle | Androgen-driven follicular miniaturisation with a genetic component |
| Clue on examination | Exclamation point hairs at the edge of a patch | Preserved follicular openings with progressively finer hairs |
| Scarring | Non-scarring — regrowth is possible | Non-scarring, but the miniaturisation is progressive |
| Treatment | Intralesional or topical corticosteroid; associated with other autoimmune disease | Topical minoxidil; finasteride in men |
What these look like
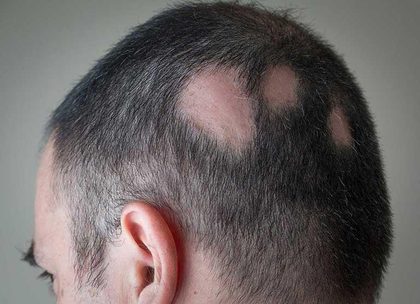
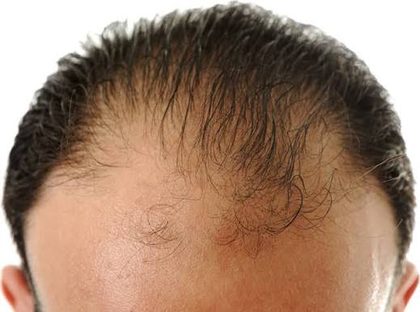
Also tested
- Male-pattern hair loss. Dihydrotestosterone is the androgen chiefly responsible; it is an androgen-dependent trait with a strong paternal influence on risk.
- Minoxidil. It is primarily effective in the crown region of the scalp; it prevents further loss and may produce regrowth, working best with finasteride.
- Scalp biopsy in alopecia. It is performed when scarring alopecia, diffuse atypical loss or persistent diagnostic uncertainty remains after clinical and dermoscopic assessment.
- Finasteride. It is an oral 5-alpha-reductase type 2 inhibitor; about 2% of men report reduced libido and erectile function, reversible on stopping. It works best combined with minoxidil, is not indicated in women and is contraindicated in pregnancy.
- Supportive care in alopecia areata. Psychological support, with support groups offered, is one of the most important considerations.
- Female-pattern hair loss treatment. Options are limited; oral antiandrogens such as combined oral contraceptives may be considered, and finasteride is not indicated in women.
- Female-pattern hair loss. It produces diffuse thinning of the central and parietal scalp without significant change to the frontal hairline, with increased frequency of balding among first-degree male relatives.
- Alopecia areata dermoscopy. Yellow dots, black dots, broken hairs, tapered hairs and short regrowth support the diagnosis. The diagnosis is clinical and dermoscopy strengthens it.
- Alopecia areata extent. Alopecia totalis describes loss of all scalp hair, and alopecia universalis describes loss of all body hair.
- Alopecia areata counseling. Psychological support is one of the most important considerations in managing this condition, and support groups may be offered.
- Non-scarring patchy hair loss with exclamation point hairs and nail pitting, in children. Topical corticosteroids are first line in children 10 years old and younger, avoiding the discomfort of intralesional injection in a young child.
- First-line treatment of alopecia areata by age. Topical steroids are first line in children ten and under; intralesional steroids are first line in adolescents and adults, since injections are avoided in young children.
- Alopecia areata treatment. Intralesional corticosteroids are first line in adolescents and adults; topical steroids are first line for children aged ten and under.
2.6 · Common dermatologic pharmacology
Four families carry most of the treatment in this lecture: emollients and barrier preparations, topical corticosteroids, topical antifungals and topical retinoids. Topical corticosteroids are usually applied twice a day for two weeks; prolonged use causes atrophy, striae, telangiectasia and hypopigmentation, so potency is chosen by site and severity.
| Potency | Agent |
|---|---|
| Mild | Hydrocortisone — all strengths (0.1%, 0.5%, 1%, 2.5%) |
| Moderate | Betamethasone valerate 0.025% |
| Medium to high | Triamcinolone acetonide 0.1% · betamethasone valerate 0.1% · betamethasone dipropionate 0.05% |
| High | Clobetasol propionate 0.05% |
Her words: “These are the ones I want you to know. If I give you a question and my slide says treatment would be a low dose corticosteroid, you might have these answer choices — you need to know that it's gonna be your hydrocortisone.” She added that she reduced the list “from a hundred to five — this is true for my class only”, so do not carry the simplification into Pharmacology.
The clinical rule she gave alongside it: a steroid on a sensitive area — the face or the genitals — should be hydrocortisone, or another low-potency agent. Betamethasone comes in two salts, valerate and dipropionate, and they sit at different potencies; the concentration alone does not tell you which tier an agent is in.
Source: 2. General Dermatology I.pptx, Slides 39–44, and the lecture recording, 2026-08-19.
Topical retinoids — adapalene, tretinoin, tazarotene, trifarotene — treat acne and photoaging, and tazarotene also treats psoriasis. Start gradually because of irritation, dryness and photosensitivity, and observe pregnancy precautions. She was specific about the titration: begin at the lowest strength and work up to nightly use, and avoid the eyes, nose and mouth.
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Atopic dermatitis | Site-appropriate topical corticosteroid — low potency or non-steroid on the face, low to medium on the body, applied sparingly. Emollients throughout. |
| Dyshidrotic eczema | High-potency topical corticosteroid. |
| Nummular eczema | Medium to high potency topical corticosteroid for active lesions. |
| Irritant contact dermatitis | Avoid the exposure and repair the barrier with emollients. |
| Allergic contact dermatitis | Limited: soothing measures — oatmeal baths, cool wet compresses, topical astringents — plus a high-potency topical steroid. |
| Seborrheic dermatitis | Topical antifungal — ketoconazole is the mainstay. Scalp: ketoconazole or selenium sulfide shampoo. Face: ketoconazole cream or lotion. |
| Perioral dermatitis | Stop facial topical corticosteroids — continued exposure perpetuates it. Stop non-essential cosmetics and occlusive moisturizers; simplify the routine. Mild disease: topical metronidazole, erythromycin, pimecrolimus or azelaic acid. |
| Diaper dermatitis | Reduce moisture and irritant exposure — frequent changes, gentle cleansing, air exposure, superabsorbent nappies. Thick zinc oxide or petrolatum barrier at every change. |
| Stasis dermatitis | Compression therapy is the cornerstone once arterial circulation is established. Leg elevation, walking, calf exercises, weight management, treat the underlying venous disease. Fragrance-free emollients. |
| Bullous pemphigoid | Mild: ultrapotent topical steroids. Moderate-severe: oral prednisone or doxycycline. Dapsone is particularly effective with mucous membrane involvement. Low-dose methotrexate is safe and effective in the elderly — with folic acid. |
| Pemphigus (vulgaris) | Urgent treatment needed. Rituximab, or high-dose oral prednisone. |
| Psoriasis — plaque | Mild: emollients, topical steroids, calcipotriene (vitamin D analog — quickest action, caution with nephrotoxicity), ultraviolet B phototherapy for smaller stubborn areas. |
| Psoriasis — guttate | No treatment needed, though phototherapy and topical steroids may be used. |
| Psoriasis — pustular | Acitretin (contraindicated in pregnancy) or methotrexate. If pregnant: high-potency topical steroids. |
| Pityriasis rosea | Self-limited — reassurance. Oral antihistamines and/or cautious topical steroids for itch. |
| Lichen planus | Superpotent topical steroids. |
| Lichen simplex chronicus | Break the itch-scratch cycle — education, treat the trigger, emollients, behavioral substitution, nail care, safe physical occlusion. Appropriate potent topical corticosteroid for a limited course. |
| Alopecia areata | Adolescents and adults: intralesional steroids. Children 10 and under: topical steroids. |
| Androgenetic alopecia | Male-pattern: topical minoxidil (mainly effective at the crown); oral finasteride, a 5-alpha-reductase type 2 inhibitor. Works best in combination. Female-pattern: treatments are limited; oral antiandrogens. |
| Xeroderma (xerosis) | Short lukewarm showers, gentle fragrance-free cleanser only where needed, thick ointment or cream within minutes of bathing. |
Also tested
- Biopsy of lichen simplex chronicus. Biopsy a plaque that is atypical, unilateral, nodular, ulcerated or treatment-resistant, to exclude neoplasia or another inflammatory disorder.
- Psoriasis comorbidities. Patients are at increased risk of cardiovascular events, type 2 diabetes mellitus, metabolic syndrome and lymphoma; psoriasis is a systemic inflammatory disease, not only a skin condition.
- Refractory bullous pemphigoid. When prednisone and doxycycline fail, immunosuppressives such as methotrexate and azathioprine are used, with biologics and intravenous immunoglobulin also used. Low-dose methotrexate is described as safe and effective in the elderly, with folic acid.
- Compression for stasis dermatitis. Consider an ankle-brachial index or toe pressure before starting substantial compression. Arterial status has to be clarified first, because compression on an ischemic limb causes harm.
- Dyshidrotic eczema hand care. Use lukewarm water and soap-free cleansers, dry thoroughly, then apply emollient immediately and as often as possible. Also avoid detergents, solvents, hair lotions or dyes, and acidic foods.
- Lichen simplex chronicus recurrence. Recurrence depends on whether the initiating itch is controlled; it is common if the itch is not controlled. Sleep, anxiety, neuropathic symptoms and the primary dermatosis all need addressing.
- Extensive or persistent perioral dermatitis. When it persists despite stopping the topical corticosteroid and simplifying the routine, treat with oral tetracycline or doxycycline.
- Reducing flares of recurrent palmar vesicles. Avoid irritants such as detergents, solvents and hair dyes, wash with lukewarm water and soap-free cleanser, dry hands thoroughly, and apply emollients immediately afterwards.
- Perioral dermatitis after stopping corticosteroid. The eruption may temporarily worsen after corticosteroid withdrawal before it improves. Telling the patient in advance stops her restarting the steroid.
- Topical retinoid counseling. Start gradually and expect irritation; the important considerations are irritation, dryness and photosensitivity, and pregnancy precautions apply.
- Before compression therapy. Perform an ankle-brachial index (or toe pressure) when peripheral arterial disease is suspected, such as with diminished pulses; compression is the cornerstone only once adequate arterial circulation is established.
- Papules and pustules around the mouth with topical corticosteroid use. Initial management is to discontinue the corticosteroid and simplify the skin-care routine. Topical corticosteroid exposure is the most important modifiable association, and continued use perpetuates the condition.
- Choosing a vehicle for barrier preparations. Ointments are more occlusive than creams (or lotions). Emollients and barrier preparations are foundational for many inflammatory conditions, including xerosis, eczema, irritant dermatitis and diaper dermatitis.
3 · Dermatology II
Instructional Objectives
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following dermatological conditions:
- Erythema multiforme
- Dermatitis herpetiformis
- Acanthosis nigricans
- Epidermolysis bullosa
- Urticaria
- Erythema nodosum
- Granuloma annulare
- Pyoderma gangrenosum
- Acne rosacea
- Hyperhidrosis
- Drug Eruptions
- Steven Johnson Syndrome
- Toxic epidermal necrolysis
- Photoreactions
- Sunburn
- Photosensitivity — drug-induced, photodermatitis, polymorphous light eruption
- Solar lentigo, keratosis
- Dermatoheliosis
3.1 · Objective a — Reactive and immune-mediated conditions
| Condition | Defining feature | The one thing to carry into the exam |
|---|---|---|
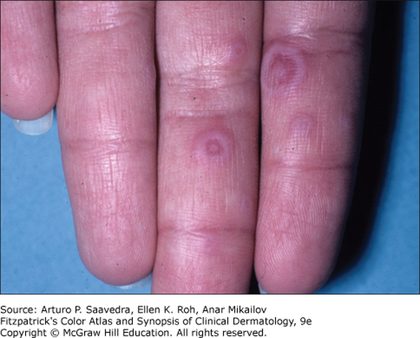
| Erythema multiforme | Target lesions with three zones, acral distribution | Herpes simplex virus triggers over 50% of cases |
| Urticaria | Wheals that individually resolve within 24 hours | A wheal persisting beyond 24 hours means biopsy for urticarial vasculitis |
| Erythema nodosum | Tender bilateral anterior shin nodules that do not ulcerate | Sarcoidosis, inflammatory bowel disease, tuberculosis, streptococcus, drugs |
| Granuloma annulare | Annular ring of papules with no scale on the border | Absent scale is what separates it from tinea |
| Pyoderma gangrenosum | Rapidly enlarging ulcer with an undermined violaceous border | Pathergy — debridement makes it worse, so do not debride |
| Acne rosacea | Central facial erythema with flushing and telangiectasias, no comedones | Absence of comedones separates it from acne vulgaris |
| Hyperhidrosis | Primary is bilateral, focal, adolescent onset, absent in sleep | Generalized or nocturnal sweating means look for a secondary cause |
What these look like
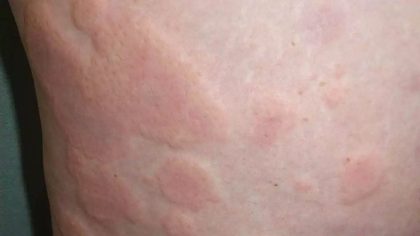
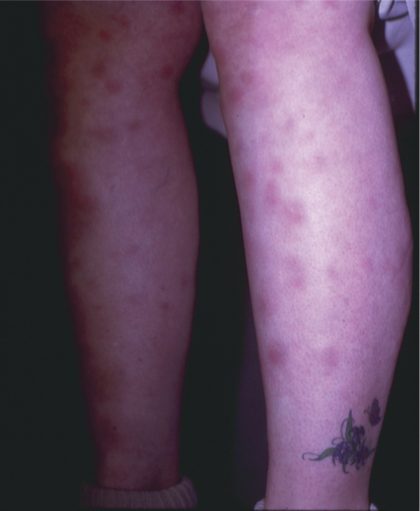
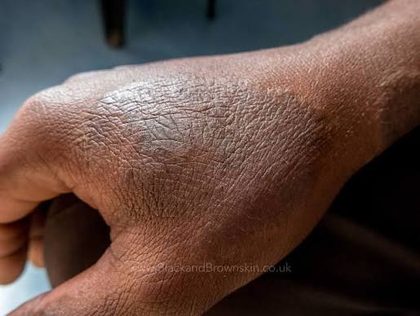
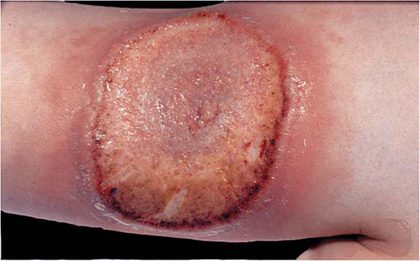
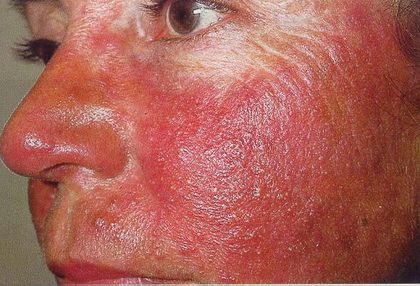
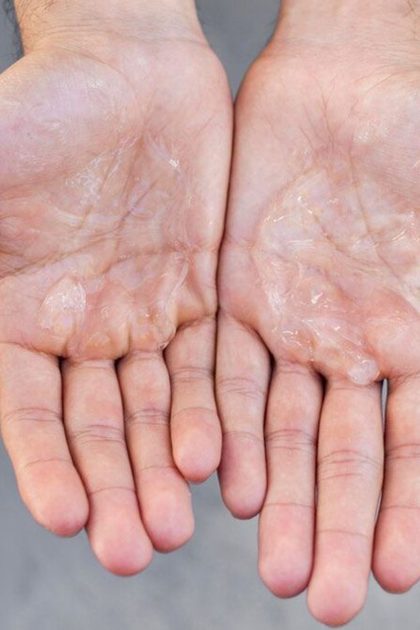
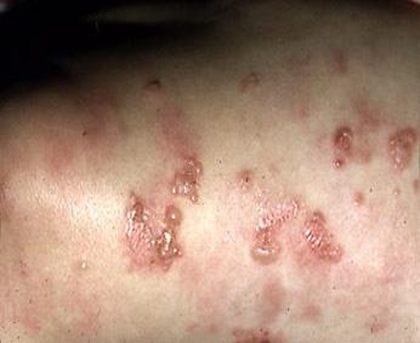
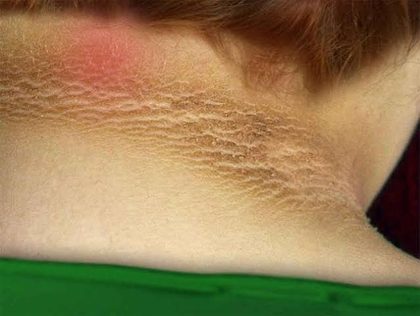
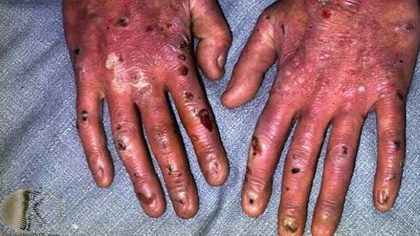
78 minutes of audio. Two statements in it point in opposite directions and are worth more than anything else in the lecture — one telling you what is on the exam, one telling you what is not.
Standing rule for anything taken from these recordings: where the audio and the slide disagree on a fact, THE SLIDE WINS. Words get said wrong in a live lecture, and one claim in this one is wrong — it is kept below with the correction attached rather than quietly removed, because knowing which spoken facts to distrust is itself worth having. What the recording is authoritative for is emphasis: what she flagged, what she excluded, and the mechanisms she explains that the slide only asserts.
| She said | What it means for you |
|---|---|
| “This is different… if you think it’s different from any other disease, what’s the likelihood it’s going to be on the test? Probably pretty high. There’s not many I can do diagnostic testing on, since they’re all clinical… it’s likely going to be on the test, just trying to help you a lot.” [12:35] | Said while pointing at dermatitis herpetiformis, and it is a rule for the whole lecture, not one condition. Almost everything here is a clinical diagnosis. The handful that are not are therefore the memorable ones, and she said outright that being different is what makes something testable. Dermatitis herpetiformis: skin biopsy is the gold standard. |
| “Don’t worry. That’s not going to be on the test. I won’t do that to you. I’m not testing for lupus right now… but that is one of, like, clinically, I want you know, one of the big ways to tell — is this lupus, is this rosacea?” [44:18] | Explicitly excluded. She taught the lupus-versus-rosacea distinction and then took it off the exam in the same breath. Worth knowing clinically and worth not spending revision time on: the lupus butterfly rash spares the nasolabial folds; rosacea involves them. And on the antinuclear antibody test — a negative result lowers the probability, a positive one only means more testing, because plenty of things make it positive. |
| “Dapsone… we also want to check the glucose-6-phosphate dehydrogenase deficiency. This is a condition you cannot take dapsone in.” [13:45] | The full dermatitis herpetiformis package, and the deck does not spell all of it out: dapsone acutely, but check for glucose-6-phosphate dehydrogenase deficiency first because it is a contraindication; strict gluten-free diet long term; refer to gastroenterology for colonoscopy, because there is a high chance of celiac disease; and refer to a registered dietitian. |
| “Metronidazole, by far the first line treatment… azelaic acid can be effective, you do have to watch, as azelaic acid can be a little bit more drying… these patients already have impaired barrier.” [44:58] | Topical metronidazole is first line for rosacea. Azelaic acid is an alternative but is drying, and these patients already have a compromised barrier. If it is really bad, low-dose doxycycline — started twice daily and stepped down to once. |
| “This is by far the classic presentation, the one that I want you to really know about.” [37:36] | On pyoderma gangrenosum. The presentation she wants: begins as a small pustule or nodule, becomes a rapidly expanding painful ulcer with a well-undermined border, and the lower extremity is the most common site. |
| “Allopurinol is the most common cause worldwide of this… it’s drug induced in 80% of cases.” [57:15] | Half right, and the slide is the half to trust. The proportion is correct — slide 87 says toxic epidermal necrolysis is drug-induced in more than 80% of cases. But the slide says allopurinol is “the most common cause in Asia”, not worldwide, and it is one of several leading culprits alongside the aromatic anticonvulsants, sulfonamides, oxicam non-steroidals and nevirapine. Go with the slide. |
| “I’ve never seen it, but you need to know it, in case you happen to be one of those… what I want you to know: this is caused by a mutation in structural proteins.” [20:58] | On epidermolysis bullosa. Rare enough that she has not seen a case, and flagged anyway — and what she wants from it is the mechanism, a structural protein mutation, rather than a clinical picture. |
| “Epinephrine, or EpiPen, is a brand name for that” — introduced as the take-home [27:26] | On urticaria and angioedema. She marked this one as the take-home point of that section. |
| “Anywhere from one to five centimeters, on anterior shins or your tibial surface, is the most common” [31:23]; “strep throat… which is the most common form of it” [30:50] | Erythema nodosum: 1–5 cm, anterior shins, and streptococcal pharyngitis is the commonest trigger. |
| “The most common idiopathic photodermatosis… particularly young middle-aged women… higher altitudes” [1:06:36] | Polymorphous light eruption. Three discriminators in one sentence: commonest of its class, the demographic, and the altitude association. |
Quoted from the 19 August 2026 lecture recording, with timestamps, and cross-examined against Notability’s independent transcript. Where the recording and a slide disagree on a number, the slide wins.
Also tested
- Highest-mortality epidermolysis bullosa subtype. Junctional epidermolysis bullosa, especially the Herlitz subtype, carries the highest mortality, so early palliative care integration is appropriate in severe Herlitz disease.
- Hyperhidrosis counseling. It is not about poor hygiene or anxiety; suggest moisture-wicking clothing, which reduces impairment, and set realistic expectations, including botulinum toxin retreatment every three to six months.
- Primary hyperhidrosis. It is a medical condition rather than a problem of hygiene or anxiety, with quality-of-life impairment comparable to severe psoriasis.
- Acanthosis nigricans counseling. It is a metabolic warning sign of insulin resistance rather than a hygiene problem, and losing even 5 to 10% of body weight improves the findings.
- Most common acanthosis nigricans. Hyperinsulinemia stimulates keratinocyte and fibroblast proliferation through insulin-like growth factor 1 receptor cross-activation; this insulin-resistant or benign form is the commonest, and malignant, drug-induced and endocrine forms make up the rest.
- Epidermolysis bullosa referrals. Referral is needed to essentially every specialty, given the multisystem burden; palliative care, genetics and family support are all involved.
- Fixed drug eruption versus erythema multiforme. Fixed drug eruption recurs at the same site, leaves residual hyperpigmentation, and has few lesions without three concentric zones; the three-zone target defines an erythema multiforme lesion.
- Granuloma annulare counseling. It is benign and self-limiting, with about half resolving within two years and no malignant potential, so treatment is for cosmesis or discomfort.
- Pyoderma gangrenosum. Despite its name, it is a neutrophilic dermatosis that is not infectious; dysregulated innate immune activation with neutrophil recruitment causes the tissue destruction.
- Pyoderma gangrenosum in inflammatory bowel disease. Infliximab at 5 mg/kg intravenously is the biologic of choice and is approved for pyoderma gangrenosum in inflammatory bowel disease.
- Ocular rosacea. Ocular rosacea with keratitis, visual symptoms or corneal involvement needs urgent ophthalmology referral for slit-lamp examination, since untreated disease risks corneal scarring.
- Rapidly expanding ulcer before treating as pyoderma gangrenosum. Malignancy and infection must be excluded because the diagnosis is one of exclusion and the immunosuppression used would worsen an infection.
- Granuloma annulare variants. The generalized or disseminated variant carries the strongest systemic associations: diabetes, thyroid disease, dyslipidemia and lymphoma. It is more common in adults over forty.
- Endoscopic thoracic sympathectomy risk. The principal risk is compensatory sweating elsewhere, occurring in over 30%. The procedure is permanent, so the trade-off must be discussed thoroughly beforehand.
- Urticaria mechanism. Mast cell degranulation releases histamine, prostaglandins and leukotrienes, causing transient dermal edema. Immunoglobulin E mediated immunologic triggers include shellfish, nuts, eggs, penicillin and insect stings.
- Velvety hyperpigmented plaques of the neck and axillae. Primary management is treating the underlying cause through weight loss and glycemic control, discontinuing any offending drug. Metformin reduces insulin resistance and may improve the skin findings.
- Ocular rosacea. Keratitis, visual symptoms or corneal involvement warrants urgent ophthalmology referral; visual symptoms and photophobia raise exactly those concerns.
- Epidermolysis bullosa and cancer. Dystrophic epidermolysis bullosa causes severe scarring and carries the greatest long-term squamous cell carcinoma risk, so its multidisciplinary team includes hematology and oncology for surveillance. Scarring subtypes carry the malignancy risk.
- Localized granuloma annulare. The localized variant (about 75 percent of cases) is asymptomatic, with flesh-colored to erythematous papules in an annular ring on the dorsal hands, feet and ankles. It is a benign, self-limiting granulomatous dermatosis.
- Rosacea triggers. Sun exposure is the most universal trigger, alongside heat, alcohol, spicy foods and stress. Chronic ultraviolet exposure is also a listed risk factor.
- Acne vulgaris epidemiology. It is the most common skin disease in the United States, affecting about 80% of Americans in their lifetime, and usually begins with the onset of puberty.
- Beremagene geperpavec. It is a topical gene therapy gel approved in 2023 for dystrophic epidermolysis bullosa, accessible through dermatology referral centers and gene therapy trials.
- Referrals in generalized granuloma annulare in older adults. Refer to oncology if lymphoma is suspected, alongside dermatology for phototherapy or systemic therapy and endocrine workup for diabetes or thyroid disease.
- Erythema nodosum. Histologically it is a septal panniculitis without vasculitis; it is the most common form of panniculitis, a delayed hypersensitivity reaction in subcutaneous fat.
- Localized granuloma annulare course. Half of cases resolve spontaneously within two years, so watchful waiting is reasonable. Treatment is primarily for cosmesis or discomfort, and there is no malignant potential.
- Most common epidermolysis bullosa. Epidermolysis bullosa simplex accounts for about 70% of cases, with intraepidermal cleavage, keratin 5 and 14 mutations, and autosomal dominant inheritance.
- Genetics of dermatitis herpetiformis. HLA-DQ2 and HLA-DQ8 are strongly associated, the same haplotypes that underlie celiac disease.
- Key diagnostic feature of urticaria. Individual lesions last less than twenty-four hours; lesions persisting beyond that suggest urticarial vasculitis.
- Erythema multiforme minor. It shows three-zone target lesions (dusky center, pale swollen ring, outer red halo) on acral surfaces after herpes simplex, with skin involvement only and no mucosal involvement.
- Botulinum toxin for axillary hyperhidrosis. It is effective for three to six months, so retreatment will be needed; setting that expectation is named in the patient education.
- Rosacea counseling. It is a chronic condition that therapy controls rather than eliminates, so long-term management and daily sun protection are expected, alongside a trigger diary and gentle non-irritating skincare.
- Severe Herlitz junctional epidermolysis bullosa. Early palliative care integration is appropriate, alongside genetics counseling and family support resources; goals-of-care discussion, pain optimization and psychosocial support are all indicated.
- Primary axillary hyperhidrosis not helped by aluminum chloride. Use glycopyrronium 2.4% cloth applied once daily, which is approved for axillary disease, or an oral anticholinergic as second line.
- Trigger testing for target lesions with oral erosions after cough and fever. Order Mycoplasma pneumoniae immunoglobulin M serology or polymerase chain reaction; elevated Mycoplasma immunoglobulin M is characteristic in children and atypical presentations.
- Biopsy in erythema multiforme. Negative direct immunofluorescence with interface dermatitis on histology supports the diagnosis; negativity distinguishes it from pemphigoid and pemphigus.
- Course of chronic urticaria. About half resolves spontaneously within a year, and over half of cases have no identifiable trigger, so the search for a cause often finds none.
- Angioedema without wheals. It should raise hereditary angioedema, and initial testing is complement C4 with C1-esterase inhibitor level and function.
- Episodic sweating with headache, palpitations and hypertension. This points to pheochromocytoma, and initial testing is twenty-four hour urine metanephrines and catecholamines.
- Pyoderma gangrenosum and debridement. The ulcer worsens with trauma, a phenomenon called pathergy, so debridement makes it larger; this is the single most consequential management point in the condition.
- Velvety, darkened, thickened skin at the neck and axillae. It is a visible marker of insulin resistance and warrants metabolic assessment: fasting glucose, hemoglobin A1c, fasting insulin and a lipid panel.
- Recessive dystrophic epidermolysis bullosa. Annual squamous cell carcinoma surveillance starts after the age of ten, because the severe scarring of dystrophic disease carries a substantial carcinoma risk.
- Malignant acanthosis nigricans. Rapid onset, extensive velvety hyperpigmentation, mucosal change and tripe palms without obesity call for urgent evaluation for an underlying malignancy, particularly of the gastrointestinal tract.
- Erythema nodosum infectious triggers. The most common is Group A Streptococcus, alongside Yersinia, tuberculosis, coccidioidomycosis, histoplasmosis and hepatitis B and C.
- Dapsone for dermatitis herpetiformis. Check glucose-6-phosphate dehydrogenase status before the first dose, then monitor the blood count for hemolytic anemia and methemoglobinemia.
- Secondary versus primary hyperhidrosis. Generalized sweating, nocturnal sweating, or an asymmetric distribution should raise suspicion of secondary disease. Primary disease is bilateral, focal and absent during sleep.
- Generalized granuloma annulare in an adult over fifty. Screen for diabetes, thyroid disease and dyslipidemia, with age-appropriate malignancy screening. These associations include lymphoma.
- Urticaria versus erythema multiforme. Urticarial wheals are pruritic, migratory and blanch fully, with no fixed target lesions; wheals migrate and last under 24 hours. Fixity over days identifies erythema multiforme.
- Drugs causing acanthosis nigricans. Niacin, corticosteroids, oral contraceptives and protease inhibitors; drug-induced disease sits alongside the insulin-resistant and malignant forms.
- Erythematotelangiectatic rosacea. The most common subtype: persistent central facial erythema, flushing, and telangiectasias with sensitive, stinging skin, and specifically no papules or pustules.
- Generalized granuloma annulare screening. Fasting glucose and hemoglobin A1c screen for diabetes, alongside a lipid panel and thyroid studies for associated systemic disease.
- Epidermolysis bullosa diagnosis. Skin biopsy with transmission electron microscopy is the gold standard for the level of cleavage. Immunofluorescence antigen mapping localizes missing or reduced proteins; genetic testing is confirmatory and guides prognosis and family counseling.
3.2 · Objective a — Lesions that signal systemic disease
| Skin finding | What to screen for |
|---|---|
| Dermatitis herpetiformis | Celiac disease in all patients; autoimmune thyroid disease; T-cell lymphoma |
| Acanthosis nigricans | Type 2 diabetes, polycystic ovarian syndrome, metabolic syndrome; gastrointestinal malignancy where onset is sudden in an adult |
| Erythema nodosum | Chest radiograph, antistreptolysin O titre, tuberculin or interferon gamma testing, colonoscopy |
| Pyoderma gangrenosum | Inflammatory bowel disease in 25 to 50%; hematologic malignancy; monoclonal gammopathy; rheumatoid arthritis |
| Generalized granuloma annulare | Diabetes, thyroid disease, dyslipidemia; lymphoma in adults over fifty |
| Secondary hyperhidrosis | Phaeochromocytoma, hyperthyroidism, lymphoma, menopause |
Dermatitis herpetiformis is diagnosed by perilesional direct immunofluorescence showing granular immunoglobulin A deposits at the dermal papillae. Treatment is dapsone for rapid symptom control plus a lifelong gluten-free diet, which is what allows dapsone to be tapered.
Epidermolysis bullosa is diagnosed by transmission electron microscopy with immunofluorescence antigen mapping, supported by a genetic panel.
Also tested
- Dermatitis herpetiformis distribution. The eruption is symmetric on the knees, elbows, buttocks and back, with intensely pruritic papules and vesicles that group in a herpetiform pattern.
- Löfgren syndrome. Erythema nodosum, bilateral hilar lymphadenopathy, fever and arthralgia form its recognized presentation, and it is referred to pulmonology or rheumatology.
3.3 · Objective a — Stevens-Johnson syndrome and toxic epidermal necrolysis
| Stevens-Johnson syndrome | Overlap | Toxic epidermal necrolysis | |
|---|---|---|---|
| Epidermal detachment | Under 10% body surface | 10 to 30% | Over 30% |
| Mortality | 1 to 5% | Intermediate | 30 to 35% |
What these look like
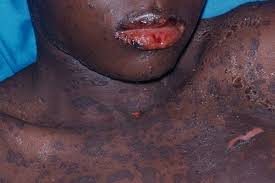
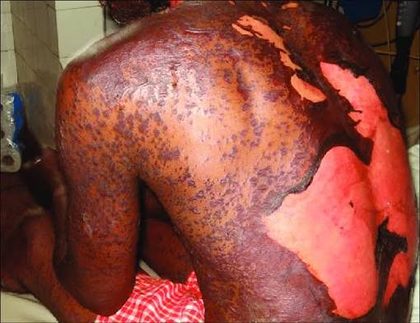
Both are severe type IV hypersensitivity reactions, drug-induced in over 80% of cases. The leading culprits are the aromatic anticonvulsants (carbamazepine, phenytoin, lamotrigine, phenobarbital), sulfonamide antibiotics, allopurinol (the commonest cause worldwide and in Asia), oxicam nonsteroidal anti-inflammatory drugs and nevirapine. Mycoplasma pneumoniae and herpes simplex virus are the infectious triggers, especially in children.
| SCORTEN — each variable scores one point, calculated within 24 hours and repeated on day 3 | |
|---|---|
| Age over 40 | Malignancy present |
| Heart rate over 120 | Initial detachment over 10% body surface |
| Blood urea nitrogen over 28 mg/dL | Bicarbonate under 20 mEq/L |
| Glucose over 252 mg/dL | |
| Predicted mortality: 0–1 → 3.2% · 2 → 12% · 3 → 35% · 4 → 58% · 5 or more → 90% | |
Human leukocyte antigen associations matter for prescribing: HLA-B*15:02 with carbamazepine, HLA-B*58:01 with allopurinol. Survivors need lifelong avoidance of the drug class, a medical alert bracelet, and first-degree relatives counseled about shared genetic risk.
Also tested
- Staphylococcal scalded skin syndrome. It spares the mucosa and is toxin-mediated, which separates it from Stevens-Johnson syndrome on the differential.
- Stevens-Johnson syndrome versus toxic epidermal necrolysis. They lie on one spectrum separated by body surface area involved: Stevens-Johnson syndrome has less than 10 percent detachment, toxic epidermal necrolysis more than 30 percent.
- Stevens-Johnson syndrome first step. Immediate withdrawal of the causative drug is the first step; earlier withdrawal is strongly associated with improved survival, and each day of delay worsens prognosis. Allopurinol is the most common trigger worldwide.
- Systemic complications of toxic epidermal necrolysis. Sepsis, acute respiratory distress syndrome, acute kidney injury, electrolyte imbalance, hypovolemia and gastrointestinal hemorrhage; survivors also face sicca syndrome, lung disease and psychological trauma.
- Level of care in Stevens-Johnson syndrome. Patients should be under intensive care or a burn unit, with dermatology involved. Nasogastric feeding is often needed because mucosal involvement prevents eating.
- First action in Stevens-Johnson syndrome. Discontinue the suspected drug and every other non-essential medication; earlier withdrawal is strongly associated with improved survival, and each day of delay worsens it.
- Pathognomonic test for Stevens-Johnson syndrome. Punch biopsy showing full-thickness epidermal necrosis with junctional separation is the pathognomonic finding.
- SCORTEN of 5 in toxic epidermal necrolysis. A score of five or above carries a predicted mortality near 90%, and palliative care is referred for an early goals-of-care discussion.
- SCORTEN in toxic epidermal necrolysis. Age, malignancy, heart rate, detachment, urea and bicarbonate each score; a SCORTEN of 6 indicates a predicted mortality of about 90%.
- Toxic epidermal necrolysis mortality. Mortality is up to 30 to 35%, predicted by the SCORTEN score calculated within 24 hours and repeated on day three.
3.4 · Objective a — Photoreactions and photodermatology
| Phototoxicity | Photoallergy | |
|---|---|---|
| Mechanism | Non-immunologic, dose-dependent | Immunologic type IV, dose-independent |
| First exposure | Reacts on it | Sensitizes; reaction on re-exposure |
| Timing | Within hours | Delayed |
| Appearance | Exaggerated sunburn, confined to exposed skin | Eczematous and itchy, extending beyond exposed skin |
| Drugs | Tetracyclines (doxycycline), fluoroquinolones, amiodarone, thiazides, furosemide, voriconazole | Sunscreen chemicals (oxybenzone), sulfonamides, topical antihistamines, phenothiazines |
| Test | Minimal erythema dose testing | Photopatch testing — the gold standard |
What these look like
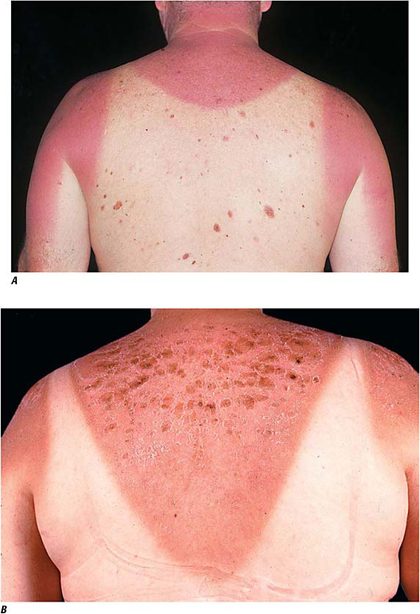
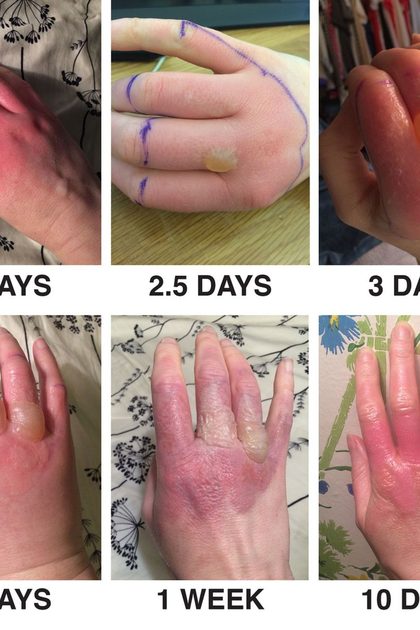
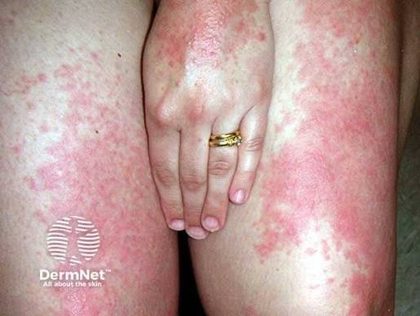
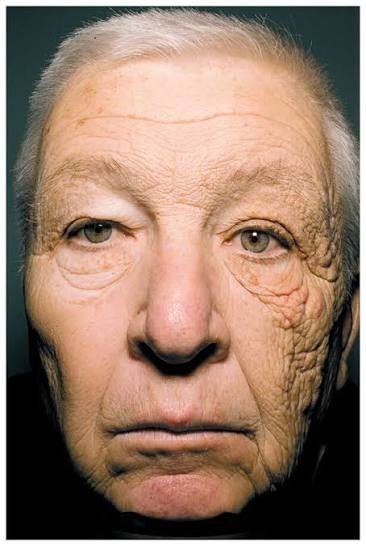

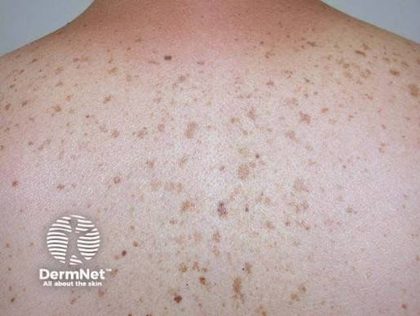
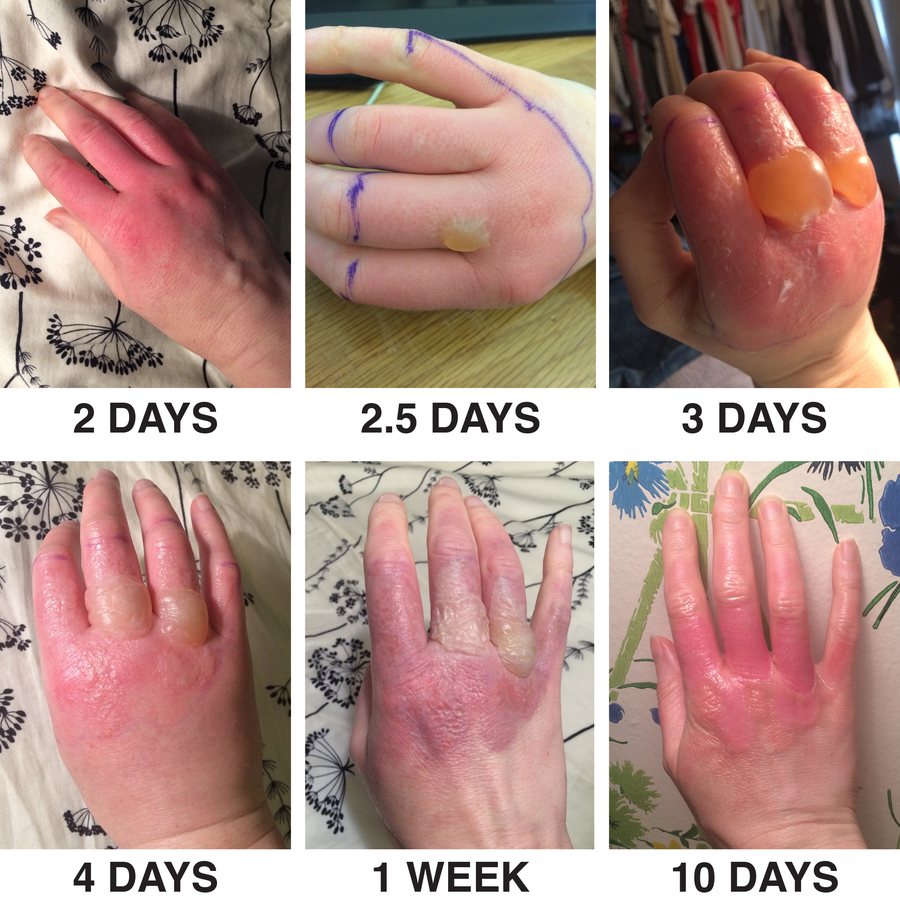
Photopatch reading: a reaction on the irradiated patch only is photoallergy; a reaction on both patches is ordinary contact allergy.
| Condition | The hook |
|---|---|
| Sunburn | Ultraviolet B at 290 to 320 nm, direct DNA damage, onset 3 to 5 hours, peak at 12 to 24 hours |
| Phytophotodermatitis | Furanocoumarins from limes, celery, parsley, fig plus ultraviolet A → streaked hyperpigmentation |
| Polymorphous light eruption | Commonest idiopathic photodermatosis; spring onset, spares chronically exposed skin, hardens by late summer |
| Solar lentigo | Uniform pigment, moth-eaten border on dermoscopy; lentigo maligna is the lesion to exclude |
| Actinic keratosis | Sandpaper texture; TP53 mutation; field cancerization, so field-directed therapy for confluent disease |
| Dermatoheliosis | Solar elastosis is the histological hallmark; tretinoin is the only agent approved for photoaging |
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Erythema multiforme | Supportive — analgesia, antihistamines, wound care. Discontinue the offending drug immediately. Topical corticosteroids for localized lesions. Oral aciclovir or valaciclovir if herpes-triggered. |
| Dermatitis herpetiformis | Dapsone for rapid symptom control. Cornerstone: a strict lifelong gluten-free diet, which is what allows dapsone to be reduced or stopped over one to two years. |
| Acanthosis nigricans | Treat the underlying cause — insulin resistance. 5 to 10% weight loss improves it. Metformin. |
| Epidermolysis bullosa | Supportive. Wound care, nutrition, infection control, pain management. |
| Urticaria | Second-generation antihistamine — cetirizine, loratadine, fexofenadine. Short oral prednisone 40–60 mg for 5 days in severe acute disease. Intramuscular epinephrine 0.3 mg immediately for anaphylaxis. |
| Erythema nodosum | Rest, leg elevation, compression stockings, a nonsteroidal anti-inflammatory drug. |
| Granuloma annulare | Localized: benign and self-limiting — treat for cosmesis or discomfort. Intralesional or topical corticosteroid. Generalized: phototherapy or systemic therapy via dermatology. |
| Pyoderma gangrenosum | Wound care (critical): avoid debridement — pathergy worsens the ulcer. Moist dressings, non-adherent contact layers. Topical tacrolimus or clobetasol to the wound edges for pain. Systemic: prednisone 0.5–1 mg/kg/day for acute rapid progression, or ciclosporin 3–5 mg/kg/day. |
| Acne rosacea | Topical metronidazole. Alternative: azelaic acid — effective but more drying, and these patients already have an impaired barrier. Ivermectin 1% cream is superior where there is a Demodex burden. Brimonidine for erythema. Sub-antimicrobial doxycycline; isotretinoin for refractory disease. |
| Hyperhidrosis | Aluminum chloride topically at night. |
| Stevens-Johnson syndrome | Most important: withdraw the causative drug immediately — earlier withdrawal is strongly associated with improved survival. Burn unit or intensive care. Aggressive fluids, temperature control, non-adhesive dressings, nasogastric nutrition, infection surveillance. Avoid silver sulfadiazine (sulfonamide cross-reaction). Antibiotic prophylaxis is NOT recommended. |
| Toxic epidermal necrolysis | Burn unit or intensive care admission is mandatory. Immediate withdrawal of all suspect drugs. Fluid resuscitation as for major burns. Non-adhesive biological dressings. Early enteral feeding. Drug: ciclosporin 3–5 mg/kg/day — strongest current evidence, early initiation preferred. |
| Sunburn | Cool compresses and cool (not cold) water immersion. Nonsteroidal anti-inflammatory drugs started early reduce prostaglandin-mediated pain. Oral hydration; intravenous fluids if severe. |
| Drug-induced photosensitivity | Identify and discontinue or substitute the offending agent where feasible. Strict photoprotection — SPF 50+ broad-spectrum, physical blockers (zinc oxide, titanium dioxide). |
| Photodermatitis (phytophotodermatitis) | Avoid the contactant and ultraviolet exposure concurrently. Acute blistering — cool compresses, wound care, mid-potency topical corticosteroid. |
| Polymorphous light eruption | Acute: avoid further ultraviolet exposure, cool compresses, moderate-potency topical corticosteroid, oral antihistamine. Short prednisolone 0.5 mg/kg/day ×4–5 days for severe episodes. Preventive: prophylactic narrowband ultraviolet B, 3×/week for 5 weeks in spring — induces tolerance and is the most effective preventive strategy. |
| Solar lentigo also Lecture 8 | Treatment is not necessary. Cosmetic removal by preference: Cryotherapy (5–10 second freeze), or quality-switched Nd:YAG, intense pulsed light or fractional laser. |
| Actinic keratosis | Lesion-directed: cryotherapy, 2–3 freeze-thaw cycles — standard of care for isolated lesions. Shave excision or curettage with electrodessication. Field-directed, for multiple or confluent: 5-fluorouracil 5% for 2–4 weeks; imiquimod 3.75% or 5% twice weekly ×16 weeks; photodynamic therapy; tirbanibulin 1%; diclofenac 3% gel for mild disease. |
| Dermatoheliosis (photoaging) | Tretinoin 0.025–0.1% — the only agent approved by the Food and Drug Administration for photoaging. Start low, titrate; expect initial retinoid dermatitis; minimum 6–12 months for visible results. |
Also tested
- Polymorphous light eruption presentation. Papules appear thirty minutes to hours after exposure on the décolletage, forearms and dorsal hands, sparing chronically exposed skin, resolving in seven to ten days without scarring and recurring each spring.
- Hardening in polymorphous light eruption. This is improvement through the summer as tolerance develops after repeated exposure; prophylactic narrowband ultraviolet B in spring is the most effective preventive strategy.
- Sunburn management. Do not pop blisters, because intact blisters are protective; use cool rather than cold water.
- Polymorphous light eruption workup. An antinuclear antibody panel including anti-Ro and anti-La is described as mandatory before the diagnosis is accepted, because lupus can present identically and must be excluded.
- Demodex-associated papulopustular rosacea. Ivermectin 1 percent cream is described as superior to metronidazole, reflecting the contribution of Demodex folliculorum mite overgrowth to the pathogenesis.
- Tender pretibial nodules. A deep incisional biopsy, needed because the pathology lies in subcutaneous fat, shows septal panniculitis without vasculitis and Miescher's granulomas.
- Sunscreen use. Broad-spectrum sun protection factor 30 or above is advised for daily use and 50 or above for prolonged outdoor exposure, applied 15 minutes before sun exposure and reapplied every 2 hours.
- Blisters in second-degree sunburn. Do not pop them, because intact blisters are protective. Use cool compresses and early nonsteroidal anti-inflammatory drugs for pain.
- Antinuclear antibody in unclear facial erythema. It helps rule autoimmune disease out; a positive result only means more testing is needed, because many things make it positive and it cannot rule a condition in.
- Tanning beds. They are not safer at all than natural sun and are classified as Group 1 carcinogens; there is no safe level of tanning.
- Chronic urticaria escalation. If symptoms persist on a standard dose of a non-sedating antihistamine, increase up to four times the standard dose and consider adding an H2 blocker; omalizumab and ciclosporin follow if that fails.
- Photodermatitis versus seborrheic dermatitis. Photodermatitis spares the nasolabial folds, which seborrheic dermatitis involves, because shadowed areas are protected from light.
- Fitzpatrick types IV to VI. These patients are not immune to ultraviolet damage or skin cancer, and melanoma is frequently diagnosed at advanced stages; delayed diagnosis is common because of a lower index of suspicion.
- Sunscreen in photoaging. Daily broad-spectrum sunscreen of SPF 30 or higher, applied as the last skincare step, is the single most evidence-supported intervention; use about one teaspoon for face and neck.
- Severe blistering sunburn. Severe blistering above 20% of the body surface with systemic symptoms warrants hospitalization, with intravenous fluids and wound care given the systemic toxicity.
- Post-phytophotodermatitis pigmentation. It fades over months, and daily sunscreen prevents it darkening further. Reassurance is first line, with hydroquinone or azelaic acid if it persists.
- Initial workup of erythema nodosum without bowel or respiratory symptoms or drug exposure. Order antistreptolysin O titer, throat culture, chest radiograph and inflammatory markers, with tuberculin or interferon gamma testing and a pregnancy test where relevant.
- Drug therapy in toxic epidermal necrolysis. Cyclosporine at 3 to 5 mg/kg daily, started early, has the strongest current evidence of the available options; early initiation is preferred.
- Photoaging. Tretinoin is the only approved topical agent; expect initial irritation (retinoid dermatitis) over 6 to 12 months. It stimulates collagen synthesis, inhibits matrix metalloproteinase activity, and reduces fine lines and dyspigmentation.
- Photoallergy diagnosis. Photopatch testing with duplicate sets, one of which is irradiated, is the gold standard; a reaction only on the irradiated set confirms it.
- Photopatch test. The suspected photohaptens are applied in duplicate and one set is irradiated with ultraviolet A. A reaction only on the irradiated patch indicates photoallergy; a reaction on both indicates contact allergy.
- Löfgren syndrome. Erythema nodosum, bilateral ankle arthritis and hilar lymphadenopathy on chest radiograph indicate sarcoidosis presenting as Löfgren syndrome, which has the best prognosis of all sarcoidosis presentations, with over 90% spontaneous remission.
- Biologic for refractory chronic urticaria. Omalizumab, an anti-immunoglobulin E antibody given every four weeks, is approved for refractory chronic urticaria.
- Toxic epidermal necrolysis disposition. Admission to a burn unit or intensive care unit is mandatory for all cases, together with immediate discontinuation of all suspect drugs, fluid resuscitation estimated as for major burns, and non-adhesive biological dressings.
- Topical azelaic acid in rosacea. At 15 to 20%, it is anti-inflammatory and anti-keratinizing, and is effective for both papulopustular and erythematotelangiectatic rosacea.
- Classic causes of phototoxicity. Tetracyclines, fluoroquinolones, amiodarone and thiazides, alongside furosemide, voriconazole, some nonsteroidal anti-inflammatory drugs and psoralens.
4 · Cutaneous Bacterial Infections
Instructional Objectives
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following cutaneous bacterial infections:
- Acne vulgaris
- Impetigo
- Cellulitis
- Erysipelas
- Erythrasma
- Folliculitis
- Furuncles
- Carbuncles
- Abscess
- Paronychia/felon
- Hidradenitis suppurativa
- Necrotizing fasciitis
- Discuss unique considerations of methicillin-resistant staphylococcus aureus (MRSA) skin infections, including risk factors, presentation, and treatment.
- Differentiate primary from secondary bacterial infection of the skin.
- Identify medical care strategies for cutaneous bacterial infections in the lecture topic list for the following populations
- infant
- child
- adolsecent
- adult
- elderly
4.1 · Objective a — Acne vulgaris
Four factors, temporal sequence not fully understood: follicular hyperkeratinization, increased sebum, Cutibacterium acnes (an anaerobic Gram-positive rod, formerly Propionibacterium acnes) and inflammation from the immune response to it. The hallmark lesion is the comedone; its absence is what rules acne out and rosacea in.
| Severity | 2016 American Academy of Dermatology recommendation |
|---|---|
| Comedonal | Topical retinoid; switch to azelaic or salicylic acid if not tolerated |
| Mild papulopustular and mixed | Topical antimicrobial plus topical retinoid, or benzoyl peroxide plus a topical antibiotic |
| Moderate papulopustular and mixed | Topical retinoid and oral antibiotic and topical benzoyl peroxide |
| Severe (nodular) | The same triple combination, or oral isotretinoin as monotherapy |
What these look like
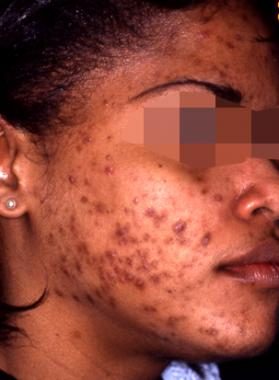
73 minutes of audio. One heuristic, one slide flagged out loud, and several prescribing details that are not on any slide.
Standing rule: where the audio and the slide disagree on a fact, THE SLIDE WINS. Every factual claim below was checked against the deck before being recorded here — the microbiology, the antibiotics and the demographics all hold. What the recording is authoritative for is emphasis, and for the prescribing detail that never reaches a slide at all.
| She said | What it means for you |
|---|---|
| “Staph aureus also for this is most common. If you guys know, this is the theme. The staph aureus, it causes a lot of these conditions. You don’t know the answer, guess staph aureus.” [1:04:05] | Exam-taking advice from the person teaching the exam. Across this whole lecture — folliculitis, furuncle, carbuncle, abscess, impetigo, cellulitis — Staphylococcus aureus is the recurring answer. Know the exceptions properly (erysipelas and ecthyma lean streptococcal, hot tub folliculitis is Pseudomonas), and let staph be the default everywhere else. |
| “These are really important slides right here. Okay, 32 and 33, make sure you know this.” [15:40] | The acne treatment ladder. She named these two slides specifically, which is as direct a flag as this lecture gives. Mild comedonal → topical retinoid, or azelaic acid if not tolerated. Mild mixed with pustules → topical antimicrobial (benzoyl peroxide) plus a topical retinoid, or benzoyl peroxide plus a topical antibiotic. Moderate → topical retinoid + oral antibiotic + benzoyl peroxide. Severe → the same three, or oral isotretinoin. |
| “Bactroban, something you should know this antibiotic, just because it’s something that you’re going to prescribe quite a bit… it has to be the ointment, don’t write the cream, because the cream for some reason is like a hundred times the price… it’s never covered.” [21:52] | Mupirocin is the prescription version of what patients buy over the counter. Write the ointment, not the cream — the ointment is covered by insurance and the cream is not. A prescribing detail that appears on no slide and will save a patient a phone call. |
| “Keflex, that’s like the most common medication that we use, and MRSA suspected you will add on Bactrim… cephalexin plus Bactrim double strength is what we’ll do if it’s MRSA.” [23:16] | Her simplified default. Cephalexin as the standard oral agent; add trimethoprim-sulfamethoxazole double strength when methicillin-resistant Staphylococcus aureus is suspected, because the combination is broad enough to cover before susceptibilities return. Susceptibility testing then confirms. |
| Nasal mupirocin twice a day for five days “will kill the colonization within their nose” [22:56] | For recurrent folliculitis, check whether the patient is a Staphylococcus aureus carrier and decolonize the nares. She notes the pre-filled swabs were discontinued, so it is applied manually now. |
| “I ask them to come back 24 to 48 hours and make sure it’s effective, because this spreads so fast.” [1:01:43] | On cellulitis. Non-purulent cellulitis over a small surface area is treated with outpatient oral antibiotics — but with a mandatory 24-to-48-hour review. That interval is the safety net, and it is the kind of thing a management question turns on. |
| “Have you guys ever heard of flesh-eating bacteria? … That’s what this is.” [1:10:07] | Necrotizing fasciitis. She then gives the microbiology plainly: polymicrobial, aerobic or anaerobic from mixed flora, or group A Streptococcus. |
| “You don’t want to apply the topical tretinoin and benzoyl peroxide together… tretinoin is usually always done at night, benzoyl peroxide you can do during the day.” [16:30] | Acne patient education, none of it on a slide: separate the two because of irritation; do not wash the face more than twice a day; gentle cleanser with warm, not hot water because hot strips the barrier; avoid oil-based make-up; four to six weeks to improve; and do not pick, because picking is what scars. |
| “Pseudofolliculitis… most commonly occurs on black and brown males, or has curlier facial or body hair. This is what this normally — you will see this, very very common.” [26:14] | She was explicit about who gets it and why — hair curvature, not hygiene — and about how often you will see it. |
| “Shaving — that’s where I see this by far most common… particularly the groin area… usually it’s abrupt eruption, hot tubs too.” [17:37] | On folliculitis. Her clinical experience puts the groin and shaving first, and hot tubs second — and hot tub folliculitis is the one that is Pseudomonas rather than staph. |
Quoted from the 19 August 2026 lecture recording, with timestamps. Where the recording and a slide disagree on a fact, the slide wins; where the recording adds a prescribing detail the slide does not carry, it is recorded here as hers.
Benzoyl peroxide goes with every antibiotic, topical or oral, to reduce resistance. Oral tetracyclines are kept to three to four months for the same reason.
Patient education: separate tretinoin and benzoyl peroxide by at least three hours; wash no more than twice daily with a gentle cleanser and warm water; use non-comedogenic products; expect four to six weeks for improvement and three to four months on the back and chest. Scarring out of proportion to lesion count suggests the patient is picking.
Also tested
- Acne pointing to polycystic ovarian syndrome. In a woman with persistent acne, hirsutism together with irregular or absent menses points toward polycystic ovarian syndrome, indicating androgen hypersecretion.
- Acne mechanica. Pressure on the skin occludes the pilosebaceous follicle; shoulder pads, orthopedic casts and helmets are the named examples.
- Acne vulgaris hallmark. The comedone, either open (blackhead) or closed (whitehead), defines acne, although acne is polymorphic.
- Acne scarring out of proportion. Suspect patient manipulation of the lesions through picking or squeezing; patients and families are educated about that risk.
- Tretinoin with benzoyl peroxide. Separate the two by at least three hours, because applying them together irritates the skin.
- Acne with inadequate response. After six to eight weeks of inadequate response, add an oral tetracycline, keeping benzoyl peroxide to limit resistance.
- Isotretinoin requirements. iPledge enrollment of the prescriber is required, with a one-month supply at a time; a pregnancy test is not needed for a man.
- Acne response time. Improvement takes four to six weeks, and the back and chest may take three to four months; clinical improvement is judged by new lesion count at six to eight weeks.
- First-line topical acne therapy. Topical retinoids (adapalene, tazarotene, tretinoin) are typical first line for comedonal and inflammatory acne; they are comedolytic, normalize hyperkeratinization and are generally the most effective for mild disease.
- Combination acne products against antibiotic resistance. BenzaClin (clindamycin with benzoyl peroxide) and Benzamycin (erythromycin with benzoyl peroxide); both pair a topical antibiotic with benzoyl peroxide.
4.2 · Objective a — Follicular and glandular infections
| Condition | What it is | Key discriminator |
|---|---|---|
| Folliculitis | Inflammation of the follicle wall and ostia — a follicular pustule | Pustule pierced by a central hair; Staphylococcus aureus commonest |
| Pseudomonas folliculitis | Pseudomonas aeruginosa from inadequately chlorinated water | 8 hours to 5 days after a hot tub; spares face, neck, palms, soles; self-limiting in 2 to 10 days |
| Pseudofolliculitis barbae | Foreign body reaction to a cut hair re-entering the skin | Not an infection. Change the shaving, do not just treat the papules |
| Furuncle | Deep abscess of a follicle and adjacent subcutaneous tissue | Single opening; no antibiotic if afebrile with one lesion under 5 mm |
| Carbuncle | Two or more confluent furuncles with separate heads | Sieve-like openings, systemic symptoms, and incision and drainage is the mainstay |
| Hidradenitis suppurativa | Inflammation of apocrine glands | Three criteria: typical lesions, axilla and groin distribution, recurrence more than twice in six months |
| Erythrasma | Corynebacterium minutissimum in the upper stratum corneum | Coral-red fluorescence under a Wood's lamp |
What these look like
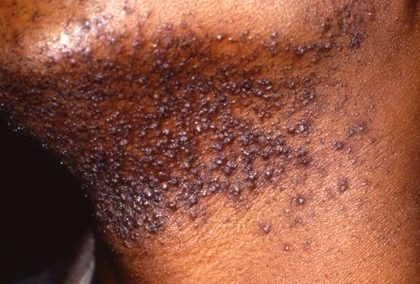
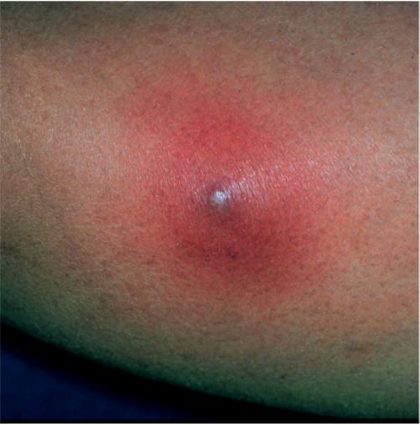
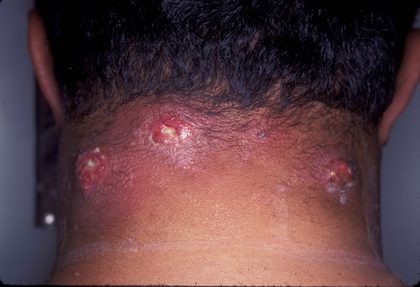
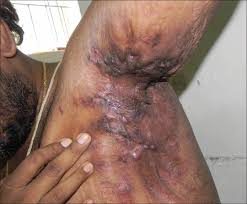
Recurrent folliculitis or furunculosis means looking for nasal carriage of Staphylococcus aureus — mupirocin ointment in the nasal vestibule twice daily for five days — alongside obesity and diabetes.
Hidradenitis suppurativa is the one with a real treatment ladder: prevention (smoking cessation is essential, weight loss, avoid heat and friction), topical steroid with topical antibiotic, intralesional triamcinolone, oral retinoid, spironolactone or combined oral contraceptive, infliximab for severe disease, and wide excision for the best chance of cure.
Also tested
- Preventing hot tub folliculitis. Maintain continuous water filtration, monitor disinfectant levels and change the water often; showering after contact does not prevent the infection.
- Hot tub folliculitis course. It is usually self-limiting, clearing in two to ten days; ciprofloxacin is reserved for widespread or resistant cases.
- Hot tub folliculitis management. Reassure, since most cases clear in two to ten days, and use dilute acetic acid compresses: 3 tablespoons of 5% vinegar in a pint of water, for 20 minutes, two to four times daily.
- Recurrent folliculitis. Recurrent or recalcitrant folliculitis raises the Staphylococcus aureus carrier state, treated with mupirocin ointment to the nares. Nasal swabs of the patient and family members evaluate carriage.
- Pseudomonas folliculitis. It is usually self-limiting, and most cases resolve without specific treatment in 2 to 10 days. A wet dressing of 5 percent acetic acid for 20 minutes, 2 to 4 times daily, may relieve symptoms.
- Erythrasma sites. Most common on the inner thighs, crural region, scrotum, and between the fourth and fifth toes; less common in the axilla, under the breasts and intergluteal folds. It is usually asymptomatic and may be pruritic.
- Wood's lamp. A handheld diagnostic device emitting long-wave ultraviolet light to highlight subtle changes in skin, scalp and hair; it evaluates pigment changes in selected fungal or bacterial infections.
- Folliculitis sites. Small papules or pustules pierced by a central hair, commonly on the scalp, thighs, trunk, axilla and inguinal area.
- Hot tub folliculitis timing and distribution. Onset is eight hours to five days after exposure, on the trunk, extremities and buttocks, usually sparing the face, neck, soles and palms.
- Pseudofolliculitis barbae. This foreign-body reaction to hair in shaved areas is most common in Black males with tightly curled hair and keratin gene variations, and in anyone who shaves and has curlier hair.
- Carbuncle versus furuncle. A carbuncle is extremely painful and more often produces systemic symptoms: malaise, chills and fever.
- Hidradenitis suppurativa diagnosis. No test is required: it is a clinical diagnosis resting on lesions, distribution and recurrence. Biopsy is not usually required, though it shows follicular occlusion and apocrine gland destruction.
- Hidradenitis suppurativa steroids. Intralesional triamcinolone acetonide decreases the size of draining sinuses. Oral prednisone reduces inflammation and prevents future lesions.
- Endocarditis prophylaxis. Endocarditis prophylaxis before the procedure is named for at-risk patients in both furuncle and carbuncle management.
- Extensive hidradenitis suppurativa. When medical therapy has failed, wide excision of the affected areas gives the best chance of permanent cure. Large fluctuant cysts are meanwhile incised and drained.
- Recurrent folliculitis. Swab the nose for Staphylococcus aureus carriage and treat with mupirocin if positive; nasal mupirocin twice daily for five days addresses the carrier state.
- Spironolactone in hidradenitis suppurativa. It is an aldosterone antagonist that lowers androgens by inhibiting ovarian and adrenal androgen production; combination birth control pills are used similarly.
- Carbuncle. A deeper infection made of interconnecting furuncles in several follicles, with several loculated abscesses, superficial pustules, necrotic plugs and sieve-like draining openings.
- Hot tub folliculitis. Caused by Pseudomonas aeruginosa, a Gram-negative organism, from inadequately chlorinated water; named sources are whirlpools, hot tubs, water slides and physiotherapy pools.
- Folliculitis. Defined by inflammatory cells within the wall and ostia of the hair follicle, forming a follicular pustule; causes include infection, physical injury and chemical irritation.
- Furuncle. A deep-seated abscess of a hair follicle and the adjacent subcutaneous tissue; Staphylococcus aureus is the commonest organism.
4.3 · Objective a — Impetigo, erysipelas, cellulitis and abscess
| Impetigo | Erysipelas | Cellulitis | |
|---|---|---|---|
| Depth | Superficial epidermis | Upper dermis and superficial lymphatics | Deeper dermis and subcutaneous tissue |
| Organism | Staphylococcus aureus or Streptococcus pyogenes | Group A streptococcus | Group A streptococcus or Staphylococcus aureus |
| Border | Crusted erosion | Raised, sharply demarcated | Not raised, not demarcated |
| Treatment | Mupirocin topically; cephalexin orally, the drug of choice in children | Penicillin V; clindamycin if penicillin allergic | Dicloxacillin or cephalexin; cover MRSA if purulent |
What these look like
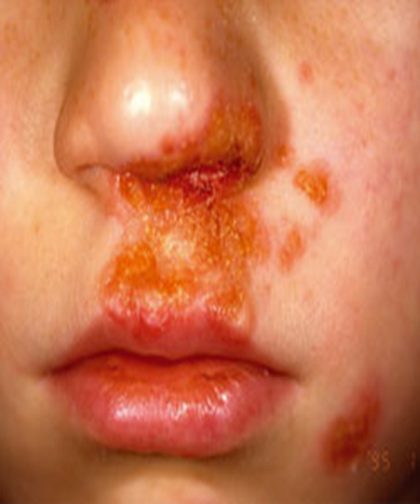
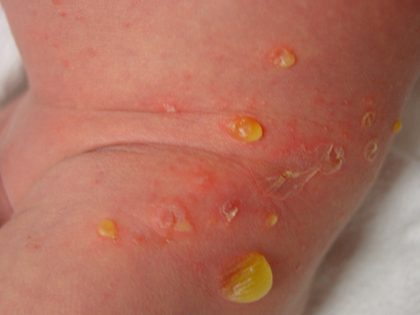
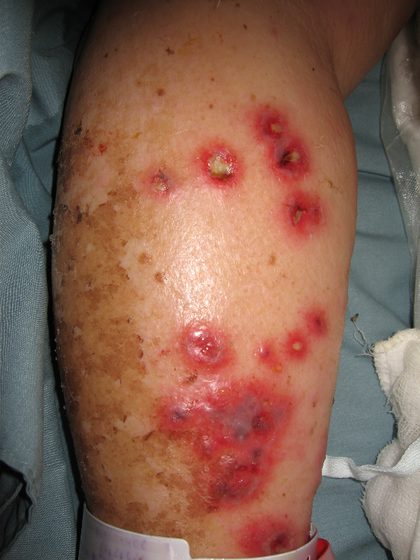
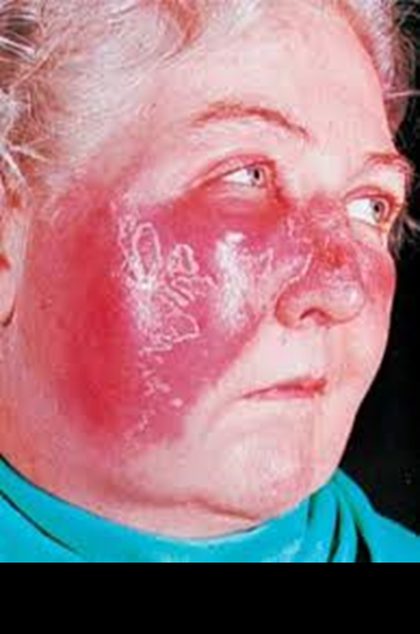
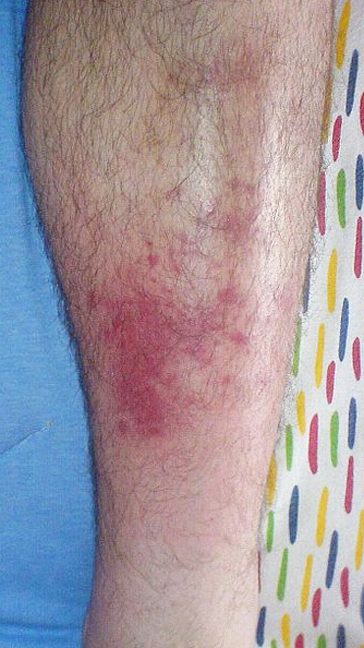
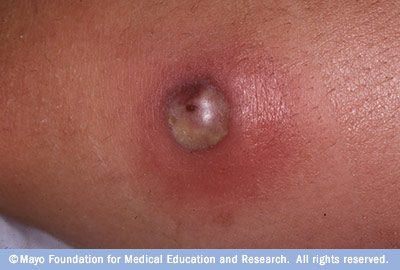
Impetigo comes in three forms: non-bullous (commonest, honey-colored adherent crust, lymphadenopathy common), bullous (exclusively Staphylococcus aureus through epidermolytic toxins, tense bullae leaving collarettes, lymphadenopathy uncommon) and ecthyma (ulcerates into the dermis, thick gray-yellow crust, heals slowly with a scar).
An abscess follows traumatic inoculation, whereas a furuncle arises from an infected follicle. If it does not drain spontaneously, incise and drain it.
The cellulitis pitfall: tense, cyanotic, bronzed or blanched tissue is devitalized. It is not perfused, so antibiotics never reach it, and it needs surgical debridement. Expect the leg to look worse on day one, fever gone by 24 hours, inflammation settling over one to two weeks. Fever beyond 48 hours means change the antibiotic, guided by culture.
Also tested
- Cultures in impetigo. Obtain cultures when the patient is at high risk for methicillin-resistant Staphylococcus aureus (for example a health-care worker or teacher) or when post-streptococcal glomerulonephritis is present.
- Erysipelas work-up. In a classic presentation it is a clinical diagnosis. Leukocytosis and raised erythrocyte sedimentation rate and C-reactive protein are common, but blood and tissue cultures are not cost effective (extremely low yield) and imaging is not indicated.
- Cellulitis examination. All four cardinal signs of inflammation are present, most often on one lower leg, with borders neither raised nor demarcated. Bilateral disease almost never occurs.
- Non-bullous impetigo. A macule evolves into a vesicle or pustule that ruptures, leaving a honey-colored adherent crust, typically on the face and extremities, with regional lymphadenopathy common.
- Cellulitis portals of entry. Named portals are tinea pedis, open lesion, trauma, surgical wound, insect bite, fissure and radiation therapy. These are distinct from the risk factors, which include diabetes and lymphedema.
- Erysipelas laboratory findings. Leukocytosis with raised erythrocyte sedimentation rate and C-reactive protein are common but not diagnostic; the diagnosis remains clinical in a classic presentation.
- Tinea pedis and erysipelas. Tinea pedis is a named risk factor for erysipelas, serving as the portal of entry and predicting recurrence, so treat it.
- Cellulitis treatment failure. Fever persisting beyond forty-eight hours of antibiotics is the stated trigger to change the antimicrobial therapy, guided by the culture results.
- Abscess versus furuncle. An abscess arises from traumatic inoculation of bacteria into the skin, whereas a furuncle arises from an infected hair follicle.
- Erysipelas risk factor. Impaired lymphatic drainage, such as after axillary node clearance, is the first risk factor named for erysipelas and explains recurrence.
- Cellulitis. It involves the deeper dermis and subcutaneous tissue, from Group A streptococci or Staphylococcus aureus; it may be purulent or non-purulent, which changes the antibiotic choice.
- Non-purulent cellulitis on oral antibiotics. Fever that persists beyond 48 hours should prompt a change in antimicrobial therapy guided by culture results; with antibiotics fever usually resolves in 24 hours.
- Culture in impetigo. Obtain a culture rather than relying on appearance alone if the patient is at high risk for methicillin-resistant Staphylococcus aureus infection, such as a healthcare worker or teacher, or if acute post-streptococcal glomerulonephritis is present.
- Devitalized tissue in cellulitis. Tense, cyanotic, necrotic, bronzed, blanched tissue is devitalized and will not be perfused, so antibiotics cannot reach it; surgical debridement is required.
- Cellulitis course on antibiotics. It may look worse on day one, fever usually resolves within twenty-four hours, and inflammation clears over one to two weeks; fever beyond forty-eight hours prompts a change guided by culture.
- Cellulitis. Warm, tender erythema whose border fades out rather than stopping; the infection is deeper.
4.4 · Objective a — Paronychia and necrotizing fasciitis
| Acute paronychia | Chronic paronychia | |
|---|---|---|
| Cause | Bacterial, Staphylococcus aureus or Streptococcus pyogenes | Inflammatory reaction to irritants; Candida albicans commonest |
| Trigger | Manicure, ingrown nail, hangnail, nail biting | Repeated water immersion — cleaners, cooks, bartenders, dishwashers, swimmers |
| Timing | 2 to 5 days after trauma | At least 6 weeks |
| Treatment | Warm soaks; incision and drainage if purulent. Clindamycin if nail biting, for oral flora | Keep hands dry; topical antifungal; oral fluconazole if severe |
What these look like
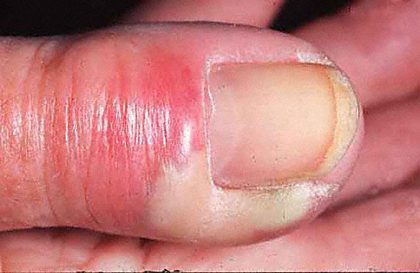
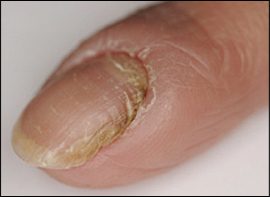
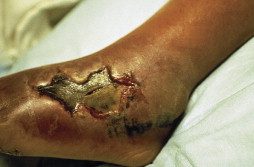
Also tested
- Laboratory studies in necrotizing fasciitis. Send complete blood count with differential, chemistry, arterial blood gas, urinalysis, and blood and tissue cultures, but they must not delay surgical intervention, because it is a surgical emergency with high mortality.
- Testing in acute paronychia. It is usually a clinical diagnosis, so testing is directed rather than routine: Gram stain and culture for the bacterial cause, potassium hydroxide for candida, and Tzanck smear for herpetic whitlow.
- Testing in classic erysipelas. No laboratory or imaging studies are routine; the diagnosis is clinical and blood and tissue cultures have very low yield. Leukocytosis and raised inflammatory markers are common but not diagnostic.
- Necrotizing fasciitis microbiology. It is polymicrobial, with aerobic, anaerobic or mixed flora, and group A streptococci (Streptococcus pyogenes) are common.
- Nail fold vesicles. A Tzanck smear rules out herpetic whitlow. Potassium hydroxide rules out candida and Gram stain identifies bacteria.
- Necrotizing fasciitis admission. Admit to a surgical intensive care unit, ideally a burn or trauma center; a team approach with consultations is required, not optional.
- Chronic paronychia. An inflammatory reaction of the proximal nail fold to irritants and allergens, with Candida albicans commonest; at risk are diabetics, laundry workers, cleaners, cooks, bartenders, dishwashers and swimmers.
- Chronic paronychia treatment. Keep the hands dry and use a broad-spectrum topical antifungal, with oral fluconazole in severe cases, treating the underlying inflammation and infection together.
- Necrotizing fasciitis care. Requires aggressive surgical debridement, broad antibiotic cover of aerobic Gram-positive and Gram-negative organisms and anaerobes, and surgical intensive care admission with a team approach.
- Acute paronychia. A red, swollen, acutely tender nail fold, with the nail plate itself still normal.
4.5 · Objectives b, c & d — MRSA, primary versus secondary infection, and care across the age range
Methicillin-resistant Staphylococcus aureus. Three oral agents recur across this entire lecture: trimethoprim-sulfamethoxazole, clindamycin and doxycycline, with linezolid and ciprofloxacin in particular settings. The methicillin-sensitive agents are dicloxacillin and cephalexin. Culture the material from any drained lesion. Risk groups named include health-care workers and teachers, and nasal carriage sustains recurrence.
Primary versus secondary infection. A primary infection arises in previously normal skin — impetigo through a minor cut, cellulitis through tinea pedis. A secondary infection arises in skin already damaged by another condition — bullous impetigo invading eczema, or acne lesions becoming fluctuant and purulent.
| Population | What changes |
|---|---|
| Infant and child | Impetigo predominates; cephalexin is the drug of choice; doxycycline only over eight years; isolate 24 to 48 hours after starting treatment |
| Adolescent | Acne vulgaris is more common and more severe in males; pseudofolliculitis barbae begins with shaving |
| Adult | Post-adolescent acne is more common in women over 25; hidradenitis suppurativa presents here |
| Elderly | Cellulitis and necrotizing fasciitis carry higher risk; comorbidity and immunosuppression lower the threshold for workup and admission |
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Acne vulgaris | Comedonal: topical retinoid (adapalene, tazarotene, tretinoin); azelaic or salicylic acid if not tolerated. Mild papulopustular: topical antimicrobial + retinoid, or benzoyl peroxide + topical antibiotic. Moderate: topical retinoid + oral antibiotic (doxycycline, minocycline; sarecycline; erythromycin if tetracycline contraindicated) + benzoyl peroxide. Severe nodular: the same triple, or oral isotretinoin monotherapy, 16–20 weeks. Hormonal: combined oral contraceptive for hyperandrogenism or unresponsive disease. |
| Folliculitis | Moist heat, antibacterial soaps, good glycemic control, good skin hygiene, loose clean clothing. Mild infection — topical mupirocin, clindamycin or erythromycin. Recurrent (carrier state): mupirocin ointment in the nasal vestibule twice daily ×5 days. Extensive: oral cephalexin or dicloxacillin. If MRSA: trimethoprim-sulfamethoxazole, clindamycin, doxycycline or linezolid (the slide also lists ciprofloxacin, but fluoroquinolones are not reliable against MRSA). |
| Pseudomonas (“hot tub”) folliculitis | Most cases resolve without specific treatment, clearing in 2–10 days. Dilute acetic acid 5% wet dressing — 3 tablespoons in a pint of water, 20 minutes, 2–4× daily. |
| Pseudofolliculitis barbae | Stop shaving if possible; clean razors; avoid “lift-and-cut” razor systems; mild razor angles, single or at most double blades. Alternatives: chemical depilatories; laser-assisted permanent hair removal. |
| Furuncle | Warm compresses are usually sufficient for small furuncles. No antibiotics if afebrile with a single lesion under 5 mm. Oral antibiotics if: a lesion under 5 mm fails drainage, a single lesion is over 5 mm, expanding cellulitis, immunocompromise, or endocarditis risk. Empiric: dicloxacillin or cephalexin. If MRSA: trimethoprim-sulfamethoxazole, clindamycin or doxycycline. Incise and drain large furuncles and culture the material. |
| Carbuncle | Incision and drainage is the mainstay of therapy. Endocarditis prophylaxis for at-risk patients. Oral antibiotics: dicloxacillin or cephalexin. If MRSA: trimethoprim-sulfamethoxazole, doxycycline or clindamycin. |
| Hidradenitis suppurativa | Prevention: avoid heat, daily antibacterial soap / chlorhexidine / benzoyl peroxide wash, weight loss, avoid constrictive clothing and friction, smoking cessation is essential, laser hair removal. Mild topical steroid with topical antibiotic (clindamycin, erythromycin). |
| Erythrasma | Localized: topical erythromycin or clindamycin. Widespread: oral erythromycin or clarithromycin. If yeast also present: add an antifungal cream (miconazole). |
| Impetigo — non-bullous | Topical, limited non-bullous: mupirocin ointment — adequate for most cases, as effective as oral with fewer side effects. Remove crusts before applying. Retapamulin is licensed but far more expensive. Oral: dicloxacillin, amoxicillin-clavulanate, cephalexin — drug of choice in children, clindamycin if penicillin allergic. If MRSA: clindamycin, trimethoprim-sulfamethoxazole, doxycycline (over 8 years old). |
| Impetigo — bullous | As for non-bullous impetigo. Coverage must include staphylococci and streptococci. |
| Ecthyma | As for impetigo, covering staphylococci and streptococci. |
| Erysipelas | Prompt treatment matters — progression can be rapid. Penicillin V. If penicillin allergic: clindamycin. Supportive: symptomatic treatment of aches and fever, hydration, cold compresses, elevation of the affected limb. |
| Cellulitis | Non-purulent: dicloxacillin or cephalexin; clindamycin if penicillin allergic. Purulent — consider MRSA: trimethoprim-sulfamethoxazole, doxycycline, clindamycin or linezolid. Oral versus intravenous depends on presentation. Devitalized tissue — tense, cyanotic, necrotic, bronzed or blanched — is not perfused, so antibiotics never reach it. It needs surgical debridement. |
| Abscess | If it drains spontaneously: warm soaks; broad-spectrum antibiotics considering MRSA, then narrow to the culture result. If it does not drain: surgical incision and drainage. |
| Acute paronychia | Mild: warm water compresses or soaks, 20 minutes 3× daily. Severe: incise and drain; obtain cultures to rule out MRSA. Oral antibiotics — amoxicillin-clavulanate, cephalexin, or clindamycin if exposed to oral flora from nail biting. |
| Chronic paronychia | Treat the underlying inflammation and infection; keep the hands as dry as possible; broad-spectrum topical antifungal (miconazole). |
| Necrotizing fasciitis | Aggressive surgical debridement of necrotic tissue. Admit to a surgical intensive care unit (burn or trauma center). Team approach with consultations. Antibiotics: broad-based, covering aerobic Gram-positive and Gram-negative organisms and anaerobes. |
Also tested
- Preventing erythrasma recurrence. Keep the area clean and dry, avoid excessive heat and moisture, and maintain a healthy body weight, alongside good general hygiene.
- Specimens in serious cellulitis. Take blood cultures and a skin punch biopsy, alongside a complete blood count and creatine phosphokinase, with imaging considered for underlying fasciitis or osteomyelitis.
- Cellulitis without diagnostic workup. It can be managed this way when involvement is limited, pain is minimal, there are no systemic signs and no risk factor for serious illness; serious infections warrant blood cultures, punch biopsy, blood count and creatine phosphokinase.
- Cellulitis work-up. Cellulitis is usually a clinical diagnosis; no work-up is needed with a limited area of involvement, minimal pain, no systemic signs, and no risk factor for serious illness such as extremes of age or immunocompromise.
- Erysipelas organism and drug. Group A streptococcus (Streptococcus pyogenes) is the most common organism, involving the upper dermis and superficial lymphatics. Penicillin V is the drug, with clindamycin if penicillin allergic; tinea pedis is a risk factor.
- Topical therapy for impetigo. For a single or limited number of non-bullous lesions, mupirocin ointment is adequate for most cases and as effective as oral therapy with fewer side effects. Remove crusts before applying it.
- Resistant folliculitis testing. A potassium hydroxide wet mount of a plucked hair rules out fungal (dermatophyte) folliculitis. Culture and Gram stain from an unroofed pustule are also performed.
- Bullous impetigo differential. It includes thermal burn, allergic contact dermatitis, and herpes simplex or zoster; non-bullous impetigo has a different differential list.
- Impetigo portal of entry. The primary portal is minor superficial breaks in the skin such as cuts and bug bites, though no predisposing lesion is identified in most patients.
- Impetigo isolation. A child may return once treatment has been underway for twenty-four to forty-eight hours. Towels, clothing, bath water, washcloths and razors must not be shared.
- Folliculitis not clearing on topical treatment. This is now a resistant case: unroof a pustule for Gram stain and culture. Culture, potassium hydroxide mount, nasal swab and biopsy are all available.
- Excluding fungal folliculitis. A potassium hydroxide wet mount using a plucked hair is the specific test named for dermatophyte folliculitis.
- Topical tretinoin in pseudofolliculitis barbae. It relieves the hyperkeratosis, removing the epidermis the emerging hair embeds in. Mild corticosteroids reduce inflammation and topical antibiotics reduce colonization.
- Impetigo in high-risk occupations. Teachers and health-care workers are at high risk for methicillin-resistant Staphylococcus aureus, so their impetigo is cultured rather than diagnosed on appearance alone.
- Diagnosis of classic erysipelas. No routine testing is needed, since blood and tissue cultures have extremely low yield. Leukocytosis and raised inflammatory markers are common but not diagnostic.
- Early acute paronychia. With erythema and tenderness but no fluctuance, treat with warm water soaks for twenty minutes three times daily; incision and drainage is reserved for severe cases with purulent collection.
- Oral agents for methicillin-resistant Staphylococcus aureus skin infection. Trimethoprim-sulfamethoxazole, clindamycin and doxycycline recur as the core options, with linezolid added in particular settings; fluoroquinolones such as ciprofloxacin are not reliable against it.
- Shaving with pseudofolliculitis barbae. Avoid lift-and-cut razors and use a single blade (at most double) at a mild angle, because lift-and-cut systems cut the hair below the skin surface where it can re-enter the follicular wall.
- Spontaneously draining abscess. Give warm soaks and broad-spectrum antibiotic cover that considers methicillin-resistant Staphylococcus aureus, then adjust to the culture result.
- Acute paronychia treatment. Warm soaks for twenty minutes three times daily in mild cases; incision and drainage in severe cases, with oral antibiotics and cultures to rule out resistant organisms where appropriate.
- Pseudofolliculitis barbae shaving advice. Use a single or double blade at a mild angle, avoid lift-and-cut systems, and keep razors clean; chemical depilatories and laser hair removal are alternatives.
- Secondary bacterial infection. A secondary bacterial infection can develop within skin already affected by acne, arising in skin damaged by an existing condition.
- Impetigo. A superficial epidermal infection, most often Staphylococcus aureus or Streptococcus pyogenes; it is very contagious and autoinoculable, and common in infants and children.
5 · Dermatological Infestations
Instructional Objectives
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following dermatological infestations:
- Scabies (Sarcoptes scabei)
- Lice (Pediculus humanus capitis)
- Bedbugs (Cimex pilosellus)
- Fleas
- Mites
- Cutanea larvae migrans
- Fire ants
- Spider bites
- Ticks
- Caterpillar
- Bee stings
- Cercarial dermatitis
- Differentiate primary from secondary skin lesions
- Identify medical care strategies for common dermatological infestations in the lecture topic list for the following populations.
- infant
- child
- adolescent
- adult
- elderly
5.1 · Objective a — Scabies and lice
Scabies is caused by Sarcoptes scabiei variety hominis, transmitted by close physical contact for 15 to 20 minutes or through bedding and underclothing. The pathognomonic lesion is a thin thread-like linear or J-shaped burrow, 1 to 10 mm long, best seen in the interdigital webs and wrists.
| First infestation | Reinfestation | |
|---|---|---|
| Pruritus appears | 4 to 6 weeks — many not for 3 months | 2 to 3 days |
What these look like
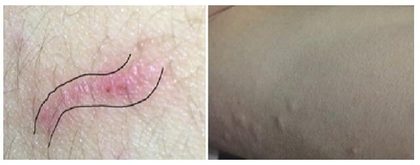
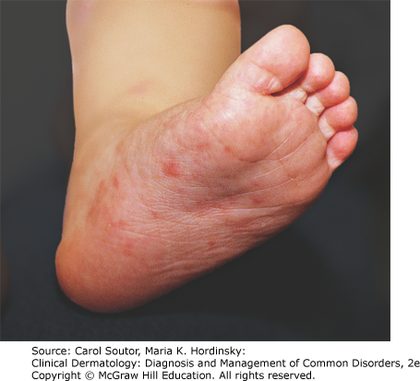

105 minutes with Professor Shah. Every factual claim here was checked against her deck before being written down, and they all hold; the one item that is not on a slide is labeled as such below rather than passed off as deck content.
| She said | What it means for you |
|---|---|
| “You will see surrounding scratch marks… but it leaves the flakes, no skin breakdown. So that’s classic, and that’s one way you’re going to differentiate it. And you can’t ask that history question. That’ll be something you see on your exam.” [1:14:37] | The clearest exam flag in the lecture. On the ground she would ask about travel and barefoot exposure; on paper you cannot, so the exam has to give you the picture instead. For cutaneous larva migrans that means the serpiginous, advancing track with scratch marks that flake but do not break the skin. Recognize it from the description, because the history will not be there to help. |
| “For this, it will be based on clinical findings… that serpiginous rash that I showed you, that is what you will see. That is a classic presentation… the other thing you can do is look at it under a light, but that would be a little bit more invasive than it needs to be.” [1:14:49] | Cutaneous larva migrans is a clinical diagnosis. She explicitly deprecates reaching for anything further once the serpiginous track is visible. |
| “Albendazole, albendazole, albendazole, or you can do ivermectin… ivermectin has a lot of follow-up management… you have to draw labs, make sure that the liver is fine.” [1:15:14] | She said the drug name three times. Slide 54 gives the regimens: albendazole 400 mg by mouth daily for three days, or ivermectin 200 micrograms per kilogram daily for one or two days. Her addition is the monitoring burden that makes albendazole the easier choice. |
| “You’ll see this delta wing jet… it means that there’s a heavy area of mites and eggs in this region.” [31:02] | The dermoscopic sign in scabies, and it is on the slide as the classic finding: a dense scabies head, body, eggs and burrow. She notes you will practice with a dermatoscope in Physical Diagnosis lab. |
| “You would apply blue-black ink to the lesion… and the lesion would be non-excoriated, one they haven’t gone in and scratched.” [31:25] | The burrow ink test, with the condition that makes it work. Excoriated lesions take up ink everywhere and tell you nothing. The three diagnostic routes on the slide are skin scraping, dermoscopy and the burrow ink test. |
| “This is part of your counseling… they need to know these steps. Otherwise… they’re going to come back in X amount of days with the same symptoms, even if they’re using the medications, because they’re going to get re-infected. Whoever they’re living with, you should treat them all.” [33:36] | Why treatment failure is usually not treatment failure. Slide 18 backs the specifics: bedding and clothing washed at 60 degrees Celsius, or bagged in a warm place for 14 days, and treat every infected person in the family or group. A patient returning with the same symptoms has usually been re-infected, not under-treated. |
| “You have your blue in the middle. You have your white around it. And then you have your red around that… that’s like a hallmark sign… you have to be the one describing it, so make sure you’re aware of what the words are for it.” [1:19:25] | The brown recluse bite, and the slide agrees: hallmark — red, white and blue sign. Her point about needing the words is worth taking literally: blue center (ischemia), white ring (vasoconstriction), red outer (inflammation). Then the progression she gives — necrosis → eschar → ulceration, and systemic symptoms such as nausea and vomiting mean escalation. |
| “Hobo spider is an aggressive spider. We’ve talked about three so far; two of them have not been aggressive. This one is aggressive.” [1:21:41] | Confirmed on the slide: Tegenaria agrestis, aka the aggressive house spider, often mistaken for a brown recluse, and the predominant cause of necrotic arachnidism in the Pacific Northwest. Black widow and brown recluse are the two non-aggressive ones. Bites July to September during mating; webs in basements, wood piles and bushes. |
| “Why do we need to know if they have seen the spider?… it can guide our treatment and we’re not trying to guess what it is… It just means we fix our face and then we take care of our patient.” [1:21:53] | If a patient brings the spider in, that is useful rather than alarming — identification directs management instead of leaving you to infer it from the wound. |
| “Neck is the most common place.” [40:04] | Her clinical addition, not a slide fact. Said answering a question about where to look for head lice. The deck gives the diagnostic method rather than the site — nits found by nit combing and wet combing, distinguished from dandruff because nits cannot be removed from the hair shaft, viable eggs tan to brown and hatched remains clear or white. Take the neck as a place to look first, not as something the deck will test. |
Quoted from the 20 August 2026 lecture recording, with timestamps. Where the audio and a slide disagree on a fact, the slide wins; every factual claim above was checked and holds.
Distribution favors interdigital webs, sides of fingers, volar wrists, elbows, axillae, scrotum, penis, labia and areolae, with head and neck spared in healthy adults. In infants, the elderly and the immunocompromised, head and neck may be involved, and infants also get indurated crusted nodules on the trunk and intertriginous areas.
Diagnosis is by microscopic identification of the organism, ova or feces: skin scraping of an unexcoriated burrow with a number 15 blade and mineral oil, dermoscopy showing the delta-wing jet sign, or the burrow ink test (a zigzag line running away from the lesion).
Treatment is topical permethrin overnight to the entire skin surface with attention to creases, and a second application one week later. Wash bedding and clothing at 60 degrees Celsius or bag it for 14 days, and treat all infested contacts. Ivermectin every two weeks for two to three doses is added for hyperkeratotic or immunosuppressed cases. Rash and itch may last four weeks after cure. Complications: staphylococcal superinfection, persistent post-scabietic papules, and psychological effects.
| Head lice | Body lice | Pubic lice | |
|---|---|---|---|
| Organism | Pediculus humanus capitis | Pediculus humanus humanus | Phthirus pubis |
| Who | Children 3 to 12 | Homeless, refugees, crowded conditions | All social levels; often a concurrent sexually transmitted infection |
| Signs | Nits fixed to the hair shaft; excoriations, scaling | Linear excoriations on back, neck, shoulders, waist | Maculae caerulae — slate-gray macules about 1 cm; periumbilical papular urticaria |
| Diagnosis | Wet combing for live lice | Examine clothing seams; shake over white paper | Nits at the base of hairs; microscopy of a plucked hair |
Nits cannot be pulled off the hair shaft — that is what separates them from dandruff. A no-nit school policy is not recommended by the American Academy of Pediatrics, because nits persist for months after cure and exclusion costs school days. Fumigation is not recommended; bag or dry clothing and bedding and vacuum.
Also tested
- Counseling during scabies treatment. Excessive washing with harsh soap can worsen skin irritation and should be stopped; the permethrin course itself is what treats the infestation.
- Facility-associated scabies. It is a particular concern because residents are elderly and immunosuppressed, and a hospital epidemic can follow their admission; it is difficult to eradicate once healthcare workers are infested.
- Body louse risk settings. Homelessness, displacement by war or disaster, and crowded conditions with poor hygiene predispose to infestation; the inability to wash or change clothes allows it to persist.
- Scabies in pregnancy. Pregnant patients are treated only where the diagnosis is documented; otherwise all infested persons in a family or group are treated.
- Cutaneous larva migrans, procedures to avoid. Surgical excision and cryotherapy are specifically not recommended. Topical therapy is also described as less effective than oral.
- Hookworm folliculitis. It may need repeated treatments, so repeat the course if pustules persist; the folliculitic form is specifically noted to be more resistant.
- Persistent post-scabietic papules. They are a recognized complication and are treated with a mid to high potency topical corticosteroid, or intralesional triamcinolone acetonide.
- Scabies contacts in pregnancy. Pregnant patients are treated only where scabies is documented, so an asymptomatic pregnant contact with no lesions has treatment withheld.
- Recurrent head lice. Use a multimodal approach combining physical methods with adjuvant chemical therapy, because of increasing resistance.
- Head lice and school. After treatment a child can return to school now; a no-nit policy is not recommended because of the school absence it causes, a position from the American Academy of Pediatrics.
- Body louse infestation. Typically found in homeless people, refugees, war victims and those in crowded conditions, persisting via unwashed clothing; transmission is through contaminated clothing and bedding.
- Scabies recovery. Most patients feel relief in about three days, though rash and itch may last up to four weeks; triamcinolone can be used for the residual itch.
- Pubic lice. Screen for concurrent sexually transmitted infection, since pubic lice often coexist with one. Slate-gray to bluish macules are maculae caerulae, representing hemorrhage at feeding sites.
- Head lice. Most affect children between three and twelve years, spread primarily by direct head-to-head contact; indirect spread through combs, brushes, bedding and headgear is less common.
- Multimodal head lice treatment. It is warranted because resistance is rising; the World Health Organization recommends that pediculicidal testing be read 24 hours after application.
- Nits versus dandruff. Nits cannot be removed from the hair shaft. Live lice indicate active infestation while nits indicate past or present infestation; viable eggs are tan to brown and hatched remains are clear, white or light.
- Physical methods for head lice. Head shaving, or combing nits out after two minutes of hair moisturizer every few days; effective but slow and painful. They need adjuvant therapy alongside them.
- Multimodal approach to pediculosis. Recommended because of increasing resistance. Pediculicidal effect is read twenty-four hours after application, the World Health Organization recommendation.
- Differential of scabies. Atopic dermatitis, body and pubic lice, other arthropod bites, dermatitis herpetiformis, fungal infection and psoriasis; all can produce an intensely itchy eruption.
- Lice causing pediculosis. Pediculus humanus capitis affects the scalp, Pediculus humanus humanus the trunk, and Phthirus pubis pubic skin; the body louse is about 30% larger than the head louse.
- Scabies transmission and itch timing. Transmission is by close contact for 15 to 20 minutes, and also from the bedding or underclothing of an infested individual; itch appears 4 to 6 weeks after infestation, and many patients have no symptoms for up to 3 months.
- Burrow ink test for scabies. When scraping is difficult, blue or black ink is applied to a suspected lesion, looking for a zigzag line running across and away from the lesion.
- Scabies not cleared by individual therapy. The regimen is ivermectin every two weeks for two to three doses, with topical permethrin every three days to weekly, the same regimen used for hyperkeratotic or immunosuppressed disease.
5.2 · Objective a — Bedbugs, fleas, stings and caterpillars
| Exposure | Presentation | Management |
|---|---|---|
| Bedbugs (Cimex) | Painless bites in a linear row of three — “breakfast, lunch and dinner”; blood flecks on linen | Symptomatic; a professional exterminator is necessary. They survive a year without a meal |
| Tungiasis (Tungidae) | Papules enlarging to a firm yellow translucent nodule on the feet, after barefoot beach exposure in endemic areas | Dermoscopy shows ovoid eggs; excision or cryotherapy, tetanus prophylaxis, systemic antibiotics |
| Fleas (Pulicidae) | Clustered urticarial papules on the lower legs | Symptomatic. Rat fleas carry bubonic plague; cat fleas carry plague and endemic typhus |
| Hymenoptera | Burning and local urticaria; severe local reaction lasts a week; systemic reaction in 0.4 to 3% | Scrape a honeybee stinger off with a card edge. Epinephrine for anaphylaxis; auto-injector and desensitization afterwards |
| Caterpillars | Gypsy moth → papules in linear streaks. Asp or puss caterpillar (most poisonous) → intense pain, train-track purpura | Strip the hairs off with adhesive tape; antihistamines, steroids, narcotic analgesia, antivenom for some |
What these look like
Also tested
- Bedbug bites. The usual reaction is wheals and papules with a hemorrhagic punctum; a bullous reaction occurs particularly in sensitized patients.
- Hymenoptera sting anaphylaxis. Treat with subcutaneous or intramuscular epinephrine, emergency department transfer and supportive measures.
- Removing a honeybee sting. Scrape it off as fast as possible with a card edge or dull knife held parallel to the skin, because the barbed ovipositor stays impaled and continues to pump venom.
- Fire ants. The venom induces mast cell degranulation, and the ants usually attack in groups. Flushing, pruritus, hives, abdominal pain, nausea, vomiting and diarrhea can follow.
- Caterpillar skin disease. Mechanisms are mechanical irritation by pointed hairs, toxin injection through hollow hairs, and hypersensitivity to hairs; the aggregate of these effects is called lepidopterism.
- Bedbug infestation. Diagnosis is by physical examination. Management is symptomatic, with a professional exterminator required: topical antiseptic or antibiotic for secondary infection, and steroids or antihistamines for itch.
- Tungiasis complication. A severe local complication is autoamputation of toes, alongside pain and pruritus at the affected sites.
- How bedbugs spread. They spread in the clothing and baggage of travelers and visitors, and in second-hand mattresses and laundry; infestation is not a marker of poor hygiene.
- Anaphylactic reaction to a sting. Give epinephrine intramuscularly or subcutaneously, with emergency transfer and supportive measures; this is an anaphylactic reaction rather than a severe local one.
- Avoiding tungiasis. Do not walk barefoot or in sandals on beaches, and do not sit directly on the sand. Nigeria, the Caribbean, India and Brazil are the named endemic settings.
- Severe asp caterpillar sting pain. Options are oral or parenteral narcotic analgesia, with antivenom for certain categories, alongside antihistamines, menthol or camphor, and corticosteroids.
- After sting-induced anaphylaxis. Carry an epinephrine auto-injector, and be referred for desensitization therapy where the skin test is positive; immunotherapy is specified for fire ant hypersensitivity.
- Tungiasis management. Surgical excision or cryotherapy and topical agents, with tetanus prophylaxis and systemic antibiotics; prevention centers on avoiding walking barefoot in endemic areas.
- Most poisonous caterpillar. The asp or puss caterpillar produces an intensely painful sting and train-track purpura. The gypsy moth caterpillar causes erucism and processionary caterpillars cause anaphylaxis.
- Bedbugs. A professional exterminator is necessary; treatment of the bites themselves is symptomatic. Use topical antiseptic or antibiotic for secondary infection, and steroids or antihistamines for itch.
- Mild local reaction to a bee sting. Treat with cleaning, ice, and possibly injection of local anesthetic for pain control; management is graded to the severity of the reaction.
5.3 · Objective a — Cutaneous larva migrans and cercarial dermatitis
| Cutaneous larva migrans | Cercarial dermatitis | |
|---|---|---|
| Organism | Animal hookworm larvae, mostly dog and cat | Cercarial form of parasitic flatworms, via snails |
| Exposure | Sand or soil with animal feces, tropical and subtropical | Fresh water — Great Lakes, rice paddies |
| Lesion | Raised serpentine trail advancing 2 to 3 cm a day, lasting 2 to 8 weeks | Prickling 30 minutes, itch at 10 to 12 hours, papules by 24 hours, peak at 48 to 72 hours |
| Treatment | Albendazole 400 mg daily for 3 days, or ivermectin. No excision, no cryotherapy | Symptomatic — antihistamines, oatmeal baths, aspirin, glucocorticoids |
What these look like
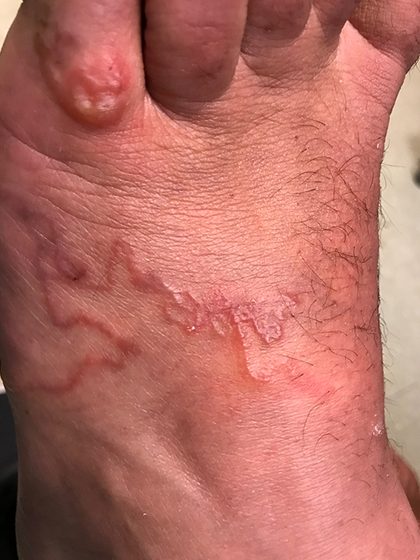
Also tested
- Cercarial dermatitis systemic features. Headaches, fever and lymphangitis can accompany it; pain and swelling peak at forty-eight to seventy-two hours.
- Cercarial dermatitis treatment. Treat symptomatically with antihistamines, oatmeal baths, antipruritic lotions, aspirin for pain and topical or oral glucocorticoids; proper washing and hygiene are also advised.
- Pathology of cutaneous larva migrans. Larvae are trapped within the follicular canal, stratum corneum or dermis with an eosinophilic infiltrate; light microscopy with mineral oil shows live and dead larvae in the folliculitic form.
- Diagnosing cutaneous larva migrans. It is diagnosed clinically on the presence of the serpentine rash; if biopsy is done, histology shows larvae with an eosinophilic infiltrate.
- Testing uncertain larva migrans. When the diagnosis is uncertain and follicular pustules are present, light microscopy with mineral oil shows live and dead larvae in folliculitis; the serpentine rash alone is enough for a clinical diagnosis.
- Preventing swimmer's itch. Wash and dry the skin properly after leaving the water. When the eruption occurs, treatment is symptomatic.
- Cercarial dermatitis epidemiology. Particularly affects the Great Lakes region, and paddy workers and rice farmers of the Far East; all share exposure to cercaria-infested water.
- Cercarial dermatitis. Also called swimmer's itch or clam digger's itch, it results from skin penetration by cercarial forms of parasitic flatworms; snails complete the cycle after eggs passed by host animals such as waterfowl and muskrats hatch and infect them.
- Cutaneous larva migrans lesion. An erythematous, raised, vesicular, linear or serpentine trail advancing 2 to 3 cm each day. It is intensely pruritic and painful, lasting two to eight weeks, with rare systemic symptoms.
5.4 · Objective a — Spider bites
| Black widow | Brown recluse | Hobo | |
|---|---|---|---|
| Identification | Red hourglass under the abdomen | Dark fiddle on the cephalothorax | Gray herringbone on the abdomen |
| Range | All but the far north | Midwest and Southeast | Pacific Northwest |
| Bite | Painful; sweating and piloerection within 30 minutes, then cramping abdominal pain and spasm | Red, white and blue sign; necrosis at 2 to 3 days, eschar at 5 to 7 | Painless; induration and paresthesia within 30 minutes, vesicles by 36 hours |
| Venom | Alpha-latrotoxin, a neurotoxin | Local cytotoxic effect | Local, with systemic symptoms |
| Treatment | Calcium gluconate, narcotics, muscle relaxants, benzodiazepines; check tetanus | Pain control, warm compresses; delay surgery until the wound is stable | Supportive; heals over weeks, headache up to a week |
What these look like

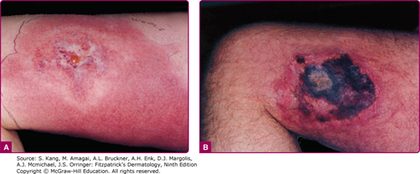

Tarantulas shed urticating hairs that embed in skin and eyes — topical corticosteroid for the skin, ophthalmology for the eye.
Also tested
- Tarantula hair in the eye. It needs urgent ophthalmology referral, since embedded hairs can cause corneal granuloma; topical corticosteroid addresses only the cutaneous reaction.
- Black widow bite. The very old, the very young and those with cardiovascular disease are at increased risk and are hospitalized. Treat with calcium gluconate, narcotic analgesia, muscle relaxants and benzodiazepines; tetanus vaccination must be up to date.
- Tarantula disease. Shed hairs embed in skin or eyes, causing pruritus, granulomas or conjunctivitis. Symptoms are generally mild and local; treat with topical steroid and refer eye involvement to ophthalmology.
- Hobo spider bite. Headaches may persist for about a week and symptoms are managed supportively; death from severe systemic effects, including aplastic anemia, is rare.
- Hobo spider bite prognosis. Wounds heal within several weeks and headaches may last a week; treatment is supportive. Death from severe systemic effects, including aplastic anemia, is rare.
- Black widow bite, first thirty minutes. Localized erythema, piloerection and sweating around the bite, then crampy abdominal pain and muscle spasm. Headache, paresthesia, nausea, vomiting, hypertension and seizures may follow.
- Brown recluse spider. Identified by a dark fiddle or violin marking on the cephalothorax; abundant in the American Midwest and Southeast. It is non-aggressive and shelters in closets, attics and stored bedding.
- Hobo spider bite presentation. A painless bite with induration and paresthesia within thirty minutes, a large red area, and vesicles within thirty-six hours. Eschar may follow; systemic symptoms include headache, nausea and memory impairment.
- Brown recluse bite timeline. Systemic symptoms develop one to two days after the bite and necrosis at two to three days. Eschar forms between days five and seven, then deep ulcers.
- Southern black widow spider. It is identified by a red hourglass on the underside of the abdomen, and its venom contains the neurotoxin alpha-latrotoxin. Latrodectus mactans is found in all but the most northern part of the country.
- Hobo spider. It is found in the Pacific Northwest, where it is the predominant cause of necrotic arachnidism and is mistaken for the brown recluse; it is brown with a gray herringbone pattern and bites from July to September.
- Hobo spider. Also called the aggressive house spider, it is the predominant cause of necrotic arachnidism in the Pacific Northwest. The bite is painless, with induration and paresthesia within 30 minutes, a large erythematous area, and vesicles during the first 36 hours.
5.5 · Objective a — Tick-borne illness
| Lyme disease | Rocky Mountain spotted fever | |
|---|---|---|
| Organism | Borrelia burgdorferi, a spirochete | Rickettsia rickettsii |
| Geography | Northeast and upper Midwest | Southeastern and south central states, spring and early summer |
| Rash | Erythema migrans — over 5 cm, central clearing, about a week after the bite | Starts ankles and wrists, spreads centripetally over 6 to 18 hours, involves palms and soles, spares the face |
| Diagnosis | Clinical if erythema migrans present. Otherwise enzyme-linked immunosorbent assay, C6 peptide, Western blot | Indirect immunofluorescence assay is the gold standard but rarely diagnostic before day 7 |
| Treatment | Doxycycline first line; amoxicillin in children and pregnancy; macrolide second line; 10 to 14 days | Doxycycline for everyone, including pregnancy and children, with desensitization where contraindicated; 5 to 10 days |
What these look like
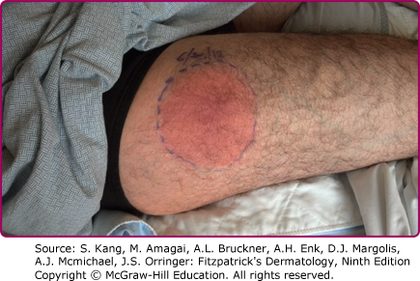
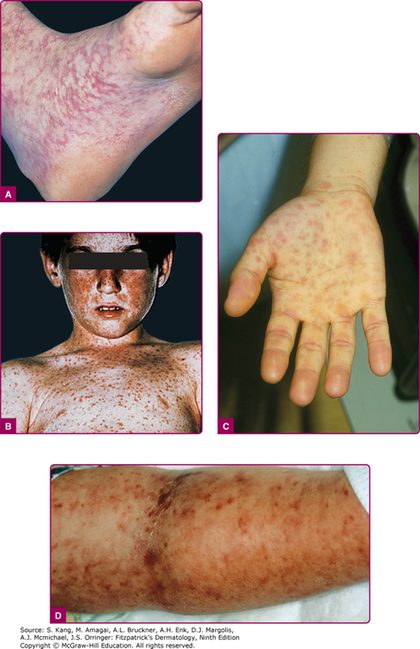
Lyme stages: 1 early localized (erythema migrans, about a week); 2 early disseminated (days to weeks — cranial nerve palsies, meningitis, radiculopathy, arthralgia); 3 late persistent (months to years — monoarticular arthritis of a weight-bearing joint, subacute encephalopathy, acrodermatitis chronica atrophicans). Intravenous ceftriaxone, cefotaxime or penicillin G for arthritis and acrodermatitis. There is no human vaccine; there is one for dogs. Repellents: DEET, PMD, picaridin, reapplied about every two hours, plus pyrethrins on clothing. Prophylactic antibiotics after a tick bite are not recommended for Rocky Mountain spotted fever.
Also tested
- Rocky Mountain spotted fever. Rickettsia rickettsii, carried by dog ticks, wood ticks and rodents, causes it; risk is higher in males, adults 40 to 64, children under 10 and rural dwellers. It is prevalent in southeastern and south central states in spring and early summer.
- Rocky Mountain spotted fever laboratory findings. Thrombocytopenia with a normal white count is characteristic, and indirect immunofluorescence assay is the gold standard test. Cerebrospinal fluid may show leukocytosis, moderately elevated protein and normal glucose.
- Erythema migrans. Stage 1, early localized infection: a lesion greater than 5 cm that expands with central clearing and often a darker punctate center (bull's-eye). Diagnose and treat on that basis; testing helps most in non-endemic regions with non-diagnostic symptoms.
- Rocky Mountain spotted fever triad. Fever above 39.5 degrees Celsius, headache and rash, present in only about 60 percent of patients. Fever presents in the first 3 days, with rash following 2 to 4 days after fever onset.
- Stage 2, early disseminated Lyme disease. It occurs days to weeks later and involves skin, central nervous system, heart, musculoskeletal system and eyes, with cranial nerve palsies, meningitis, radiculopathies, arthralgias and stiff neck.
- Serologic testing for Lyme disease. It is most useful in patients who do not live in an endemic region and present with signs possibly consistent with it; a patient with erythema migrans is diagnosed and treated clinically.
- Laboratory findings in Rocky Mountain spotted fever. Cerebrospinal fluid shows leukocytosis with moderately raised protein and normal glucose; blood shows thrombocytopenia, anemia, mild hyponatremia and mild transaminitis with a normal white count and increased bands.
- Tick bite and Rocky Mountain spotted fever prevention. Prophylactic antibiotic therapy is not recommended; prevention rests on avoidance, clothing, tick checks and DEET. Patients should return if fever or headache develop.
- Rocky Mountain spotted fever in children. Treat with doxycycline at 2.2 mg per kilogram by mouth twice daily for five to ten days. It is used in children and pregnancy, with desensitization where contraindicated.
- Doxycycline for Rocky Mountain spotted fever in young children. It is still used, with a desensitization protocol available where it is contraindicated, because the risk of untreated disease outweighs the concern about tooth staining.
- Erythema migrans. A patient with the classic lesion is diagnosed and treated on clinical grounds without waiting for serology; testing is most useful outside endemic regions.
- Lyme testing outside endemic regions. Testing is most helpful in patients outside an endemic region with possibly consistent symptoms: enzyme-linked immunosorbent assay first, with Western blot more specific.
- Rocky Mountain spotted fever treatment. Doxycycline is used for adults, pregnant patients and children, with desensitization where it is contraindicated.
- Suspected Rocky Mountain spotted fever. Start doxycycline now without waiting for serology, since treatment should begin by day 5 and the indirect immunofluorescence assay is rarely diagnostic before day 7.
- Rocky Mountain spotted fever rash. It starts on the ankles and wrists and spreads centripetally over six to eighteen hours, involving palms and soles but sparing the face. Blanching macules or papules may become petechial and purpuric.
- Intravenous antibiotics in Lyme disease. Used for some cutaneous manifestations, acrodermatitis chronica atrophicans and arthritis. Ceftriaxone, cefotaxime or penicillin G are the agents named.
- Stage 3 (late persistent) Lyme disease. The classic manifestation is monoarticular or oligoarticular arthritis affecting the knee or weight-bearing joints. Subacute encephalopathy and acrodermatitis chronica atrophicans also occur.
- Oral antibiotics for Lyme disease. Doxycycline is first line, with amoxicillin as the alternative first line for early erythema migrans; macrolides such as azithromycin are second line.
- Attached tick. Remove the tick immediately, then watch for the rash and constitutional symptoms; antibiotics are indicated once the disease is diagnosed, at all stages.
- Rocky Mountain spotted fever without rash. It can present without a rash in about 20% of patients; the full triad is present in only about 60%, and the rash follows the fever.
- Preventing tick-borne illness. Avoid tick habitat, use DEET, PMD or picaridin reapplied about every two hours, and treat clothing with pyrethrins; there is no human vaccine, though one exists for dogs.
5.6 · Objectives b & c — Primary versus secondary lesions, and care across the age range
Primary lesions affect the epidermis and superficial dermis; secondary lesions infiltrate the dermis or subcutaneous tissue. Their combination determines the diagnostic category, also called the reaction pattern. Crusting or scaling tells you the epidermis has been affected. Once the reaction pattern is recognized, color, shape, configuration and distribution narrow the differential further.
| Population | What changes |
|---|---|
| Infant | Scabies involves head and neck and produces trunk nodules; permethrin remains the treatment |
| Child | Head lice peak between 3 and 12 years; Lyme disease gets amoxicillin; the no-nit policy is not recommended |
| Adolescent | Outdoor and water exposure drives hot tub folliculitis, cercarial dermatitis and tick bites |
| Adult | Travel history opens tungiasis and cutaneous larva migrans; occupation opens body lice and cercarial dermatitis |
| Elderly | Crusted scabies in long-term care; higher complication risk from black widow envenomation |
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Scabies | Topical permethrin overnight to the ENTIRE skin surface with attention to creases, and a SECOND APPLICATION ONE WEEK LATER. Non-pharmacologic: wash bedding and clothing at 60°C or bag for 14 days in a warm area; treat all infected persons in the family or group. Hyperkeratotic or immunosuppressed: ivermectin every 2 weeks for 2–3 doses + topical permethrin every 3 days to weekly. Pregnancy: treat only if documented. |
| Crusted (hyperkeratotic) scabies | Ivermectin every 2 weeks for 2–3 doses plus topical permethrin every 3 days to weekly. |
| Pediculosis capitis (head lice) | A multimodal approach is warranted because of increasing resistance. Pediculicidal effect read 24 hours after application (World Health Organization). Physical methods: shaving the head; combing nits after 2 minutes of hair moisturizer, then drying — repeated every few days. These work but are time-consuming, painful and difficult, and need adjuvant therapy. |
| Pediculosis corporis (body lice) | As for head lice — multimodal, with attention to clothing. |
| Pediculosis pubis (crabs) | As for the other forms. |
| Bedbugs | Symptomatic treatment and local wound care. Secondary infection: topical antiseptic lotion or antibiotic cream. Pruritus: topical corticosteroids or oral antihistamines. Eradication: a professional exterminator is necessary. |
| Tungiasis (fleas) | Surgical excision, or cryotherapy / topical agents. Plus: tetanus prophylaxis and systemic antibiotics. |
| Caterpillars (lepidopterism) | Symptomatic: systemic antihistamines; topical menthol or camphor; moderate to high potency topical corticosteroids; systemic corticosteroids; oral or parenteral narcotic analgesics for severe pain. Specific: remove the hairs by “stripping” with adhesive tape. Antivenom for certain categories. |
| Cutaneous larva migrans | Albendazole 400 mg by mouth daily for 3 days, or ivermectin 200 micrograms/kg daily for 1–2 days. Hookworm folliculitis may need repeated treatments. Topical therapy is less effective. Surgical excision and cryotherapy are NOT recommended. |
| Black widow spider | Local wound care versus hospitalization depending on symptoms. Envenomation: calcium gluconate 10%; narcotic analgesics; muscle relaxants; benzodiazepines. Ensure tetanus vaccination is up to date. |
| Brown recluse spider | Pain control, warm compresses, avoid strenuous exercise. Antibiotics for secondary bacterial infection. Necrotic wounds heal very slowly and may need surgical intervention or reconstruction to close the defect — surgery is DELAYED until the wound is stable. |
| Hobo spider | Supportive measures. |
| Lyme disease | Remove the tick immediately. Antibiotics are indicated at all stages. Oral: doxycycline. Children and pregnant women: amoxicillin (alternative first line for early erythema migrans). |
| Rocky Mountain spotted fever | Adults: doxycycline 100 mg by mouth every 12 hours for 5–10 days — the same in pregnancy. Children: doxycycline 2.2 mg/kg by mouth every 12 hours for 5–10 days. Second line (allergy or contraindication): doxycycline via desensitization — small initial doses increased every 15–60 minutes until the therapeutic dose is reached — including in pregnancy and children under 8, where teeth staining and hepatotoxicity are the usual contraindications. |
| Cercarial dermatitis (swimmer's itch) | Symptomatic: antihistamines, oatmeal baths, antipruritic lotions. Aspirin for pain control. Topical or oral glucocorticoids. |
Also tested
- Ulceration versus erosion. Ulceration is full-thickness loss extending to the dermis or deeper, whereas an erosion loses only the epidermis; depth is the discriminator and determines whether the lesion can scar.
- Scaling. It is accumulation of loose or adherent cornified fragments of the epidermis, typically gray or white; lichenification is thickening and hardening of the skin.
- Household measures after head lice. Put clothing and bedding from the past week in the dryer or bag it for two weeks, wash combs and vacuum; fumigation is specifically not recommended.
- Ulceration versus erosion. Ulceration is full-thickness skin loss extending to the dermis or deeper, whereas erosion is partial loss of only the epidermis. Depth is the entire distinction.
- Bedbug behavior. Warmth and carbon dioxide draw them out to feed; by day they hide in cracks and crevices of headboards and picture frames, behind loose wallpaper and in other dark places.
6 · Cutaneous Viral and Fungal Infections
Instructional Objectives
- Interpret a potassium hydroxide (KOH) wet mount preparation
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following cutaneous viral and fungal infections:
- Mycoses
- Dermatophyte infections (tinea)
- Intertrigo
- Id reaction
- Pityriasis versicolor (tinea versicolor)
- Candidiasis
- Verrucae (including plantar warts)
- Varicella and herpes zoster
- Molluscum contagiosum
- Herpes simplex lesions, including.
- Herpetic Whitlow
- Onychomycosis
- Mycoses
- Identify medical care strategies for cutaneous viral and fungal infections in the lecture topic list for the following populations.
- infant
- child
- adolescent
- adult
- elderly
Where the lecture audio and a slide disagree on a fact, THE SLIDE WINS. Every fact in this section, in the four Lecture 6 quizzes and in the Lecture 6 cram sheet entries comes from the PowerPoint. Nothing here was taken from the recording without being checked against a slide first.
104 minutes across two segments. Both transcripts were read and diffed — a local transcription and Notability’s — and every factual claim below was checked against the deck before being written down. Where the audio and a slide disagree on a fact, THE SLIDE WINS.
Three topics were NOT covered in the live lecture. She ran out of time at the herpes simplex slides and said: “I only have two topics left… we have herpetic whitlow and then warts left… so what I’ll do is I’ll do a little recording for those last two topics for you guys. I’ll upload them, just watch them at your convenience.” [1:33:24]
Molluscum contagiosum was not covered either — nine separate descriptors (umbilicated, pearly, poxvirus, molluscum, dimple, cheesy, curettage, cantharidin) return zero hits across both transcripts. So herpetic whitlow, molluscum contagiosum and warts are deck-only so far. Sections 6.6 and 6.7 above cover all three in full from the slides, and they are in the quizzes, the cram sheet and the comparison chart. Watch for her supplementary recording.
| She said | What it means for you |
|---|---|
| “Hutchinson sign is where there is a lesion across the nose because of the way the dermatome works in the face, that facial nerve. That facial nerve, the one that innervates the eyes… anybody who has involvement of the V1, ophthalmic V1 cranial nerve, facial nerve…” [1:16:03] | THE SLIDE DISAGREES, and this one matters. Slide 103: herpes zoster ophthalmicus “involves the ophthalmic division (V1) of cranial nerve V” — the trigeminal nerve. The facial nerve is cranial nerve VII, and that is what Ramsay Hunt involves — which she describes correctly two minutes later as “peripheral facial paralysis with painful vesicles in the ear.” She names V1 correctly and then attaches the wrong nerve to it. Both transcripts record the phrase three times, so it is not a transcription artifact. Hold the contrast the deck draws: zoster ophthalmicus = V1 of the trigeminal (CN V); Ramsay Hunt = facial (CN VII). Conflating them is exactly the discrimination an exam question would test. |
| “Every single medication we’re gonna talk
about today, antifungal, anything that treats fungus, you have to monitor liver enzymes.
That’s the biggest thing with those, and that’s every single one of them.”
[7:07] …then 40 seconds later: “Before you ever start anybody oral antifungal agents, you have to make sure they don’t have liver disease. And if I’m starting anyone on oral antifungal for a longer term period, like more than like a week, I will make sure that I’m doing baseline liver function tests.” [7:42] |
The opening sentence overstates; her own qualification is the one that matches the deck. Slide 15 says obtain baseline liver tests “when indicated by the selected systemic agent, label, and patient risk”, and slide 52 “per labeling and patient risk”. That is systemic agents, conditionally — topical antifungals are not implicated at all, and it is a baseline test rather than ongoing monitoring. A student who hears only the first sentence will over-order labs on a patient using a cream. Her elaboration — oral, longer course, baseline — is right. |
| “Once therapy has begun, they can go back to school. They don’t need to be out of school the entire time… so usually within like 24 to 48 hours after therapy, they can go back to school and they will not be contagious to their classmates.” [9:24] | The framing matches the deck; the number is hers. Slide 17 says only “school exclusion is generally unnecessary once effective therapy has begun; follow local policy.” No 24-to-48-hour figure appears anywhere in the deck. Take it as her clinical practice and a good answer to a parent, not as something the exam will key on. |
| “There is a ketoconazole oral tablet but I never prescribe that because liver toxicity is really, really high with that.” [7:23] | Corroborates the deck. Slide 82: do not use oral ketoconazole for superficial infection because serious hepatic and adrenal toxicity outweigh benefit. Useful framing: the objection to oral ketoconazole is a safety one, not an efficacy one. |
| “Topical or systemic corticosteroids do not prevent post-herpetic neuralgia and should never be used in replacement of antiviral therapy. That’s really important to know.” [1:20:57] | She flagged it out loud, and it is verbatim from slide 107. This is the sentence to be able to state cold. Section 6.5 above carries it as its own line for that reason. |
| “It’s a linear rash of grouped vesicles that does not cross midline… it’s going to stop right in the middle.” [1:13:19] | Confirms slide 100. She calls the back “the most classic” presentation, consistent with thoracic 55%. |
| “You do want to avoid aspirin in children and use caution with NSAIDs. So give them Tylenol for any type of fever, because fever is very common with that.” [1:04:06] | Confirms slide 87. The acetaminophen preference is her addition and a sensible one. |
| “Erythematous patches of varying sizes with satellite lesions — and that is your buzzword.” [51:44] | She used the word “buzzword” explicitly. Satellite papules or pustules = Candida, from slide 68. It is the finding that separates candidal intertrigo from tinea cruris, which spares the scrotum. |
| “Someone comes in with otitis media and they’re older… make sure to evaluate the ear canal very thoroughly. I had a colleague… they missed this diagnosis because the vesicles are actually inside the ear canal. They hadn’t developed vesicles yet outside.” [1:17:46] | Her clinical addition, not a slide fact — and a good one. Ramsay Hunt can be missed because the vesicles are not yet visible externally. Pair it with the deck’s reason for urgency: hearing loss, tinnitus or vertigo, and protect the cornea if eyelid closure is impaired. |
| “Even if you don’t see lesions in the eye, still send them to an ophthalmologist… I don’t have the proper equipment in my office to be able to see that.” [1:16:23] | The practical version of slide 103’s “its absence does not exclude eye involvement”. A normal-looking eye at the bedside is not reassurance. |
| “It inhibits growth and replication of the fungus. I will not test you on that. You will be tested on that pharmacology.” [0:22] | A DE-EMPHASIS. The ergosterol mechanism belongs to Pharmacology, not this exam. Know which class an agent belongs to — allylamine (“-fine”) versus azole (“-azole”) — and what that means for spectrum and choice, rather than the biochemistry. |
| “You must learn the generic names because that’s what will be on your exam.… I know in the PowerPoint we have generic on there, but I’ll put both.” [1:36:12] | An explicit exam instruction. Learn generic names; brand names may appear alongside them but the generic is what is keyed. Everything in this guide, the quizzes and the cram sheet is written generic-first for that reason, with brands in brackets where the deck gives one (Zelsuvmi, Ycanth, Lamisil, Gris-PEG). |
| “Anything that was presented in the lecture is fine.” [1:34:06] “I promise you I am not a professor who’s trying to trick you on the exam… I’m not gonna give you nummular eczema and tinea corporis without giving you a lot of other background information.” |
On scope and on style. Scope is what the lecture presented. Style is multi-clue stems rather than one-line gotchas — a vignette will give you the supporting history and examination, not just the single discriminating word. The vignette sets are written that way. |
Quoted from the 20 August 2026 lecture recording, 104 minutes across two segments, with timestamps. Both transcripts read and diffed. Where the audio and a slide disagree on a fact, the slide wins — the two disagreements found are marked above.
6.1 · Objective a — Reading a potassium hydroxide preparation
The whole point of the preparation is that potassium hydroxide dissolves keratin and leaves fungus behind, so what remains under the coverslip is the organism. What you are looking for depends on which organism you are chasing:
| Organism | What you see | Where to take the sample from |
|---|---|---|
| Dermatophyte (tinea) | Branching hyphae | The ACTIVE BORDER of the lesion — not the cleared center |
| Malassezia (pityriasis versicolor) | Short hyphae with clusters of yeast — “spaghetti and meatballs” | Fine scale, revealed by scraping or stretching the lesion |
| Candida | Budding yeast and pseudohyphae | The affected fold, including a satellite lesion |
| Onychomycosis | Fungal elements in nail material | The most PROXIMAL accessible diseased nail bed or subungual debris, after trimming the onycholytic nail |
Three sampling rules carry most of the exam value here. Take dermatophyte samples from the advancing edge, because that is where the organism is and the center is where it has already gone. Take nail samples proximally, not from the crumbling free edge. And in a suspected id reaction, sample both sites — the diagnosis is made by the pattern: positive at the primary infection, negative at the reaction.
Two adjuncts, each with a limitation worth memorizing. The Wood lamp may rapidly support Microsporum in tinea capitis, but Trichophyton tonsurans — the commonest species in the United States — usually does not fluoresce, so a negative lamp excludes nothing. In pityriasis versicolor it may show yellow-gold fluorescence, but sensitivity is limited. Neither test is a substitute for the preparation.
Also tested
- Negative potassium hydroxide preparation. High clinical suspicion of tinea corporis with a negative preparation is an indication for fungal culture, as are refractory cases.
- Scaly patch of alopecia. Before a prolonged systemic antifungal course, confirm with potassium hydroxide microscopy and fungal culture when feasible.
- Testing round, scaly plaques. The initial test is a potassium hydroxide preparation, because tinea corporis is the main differential and is excluded by it; absent central clearing already argues against tinea corporis.
- Diaper rash with fold involvement. Fold involvement and satellite lesions suggest Candida; the test is a potassium hydroxide preparation, where budding yeast or pseudohyphae supports it.
6.2 · Objective b — The dermatophytes, by body site
Dermatophytes infect and survive only on DEAD KERATIN — the stratum corneum, hair and nails. They cannot survive on mucous membranes, which is the single fact that separates them from Candida. Three genera account for the majority: Microsporum, Trichophyton and Epidermophyton. The disease is then classified by body location, not by organism.
| Site | Name | The discriminating feature |
|---|---|---|
| Scalp | Tinea capitis | Preadolescent children; broken hairs, black dots, lymphadenopathy. Oral therapy required. |
| Beard | Tinea barbae | Hairs are loose and easily removed — unlike bacterial folliculitis. Oral therapy required. |
| Body | Tinea corporis | Central clearing giving the annular “ringworm” outline |
| Groin | Tinea cruris | The scrotum is typically SPARED |
| Feet | Tinea pedis | Commonest dermatophyte infection in adults; three variants |
| Hand | Tinea manuum | Two feet–one hand: the hand used to scratch the foot |
Why the scalp and beard are different. Both involve the hair shaft and follicle, and topical agents do not penetrate there. That is the entire reason those two sites demand oral therapy while a body or groin lesion does not. Pair the organism with the drug: terbinafine for Trichophyton, griseofulvin for Microsporum.
Tinea capitis is also a public-health problem, not just a scalp problem. Fungal particles stay viable for months, asymptomatic carriers exist, and transmission runs through people, pets, fallen hairs, clothing, combs, hats and furniture. Antifungal shampoo reduces spore shedding but never replaces the oral course. School exclusion is generally unnecessary once effective therapy has begun.
The three tinea pedis variants are worth separating, because the treatment differs for one of them:
| Variant | Appearance | Treatment note |
|---|---|---|
| Interdigital (most common) | Maceration and erosion, especially 3rd and 4th interspaces, with fissures | Topical terbinafine, butenafine or an azole |
| Hyperkeratotic | Plantar thickening in a shoe distribution — soles plus medial and lateral surfaces | Add a KERATOLYTIC to the antifungal |
| Vesiculobullous | The moist acute form — pruritic and painful, vesicles or bullae on erythema | Topical antifungal |
Two traps in treatment. First, never use a corticosteroid–antifungal combination product: the steroid masks and worsens the dermatophytosis, producing tinea incognito. Second, treat tinea corporis 1 to 2 cm beyond the visible border, because the advancing edge is where the organism is.
What these look like
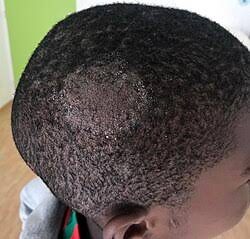
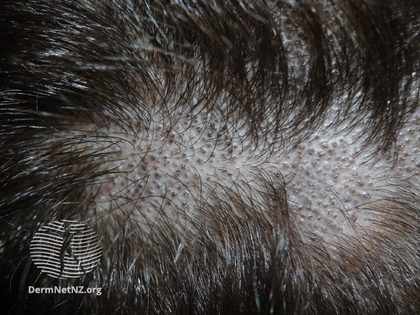
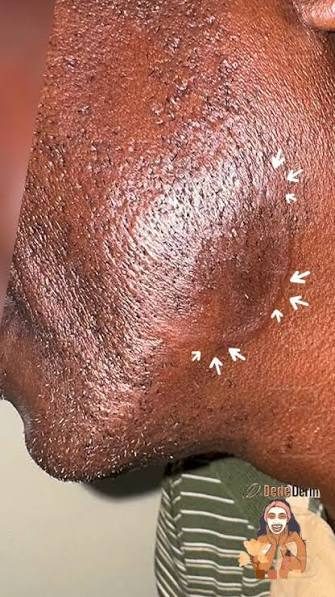
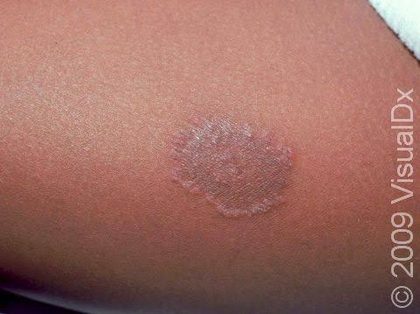
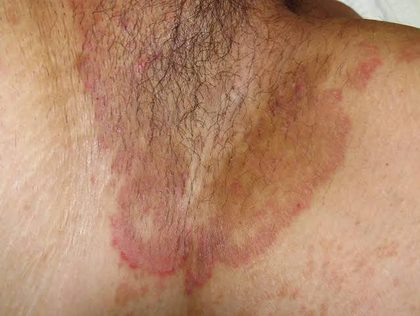
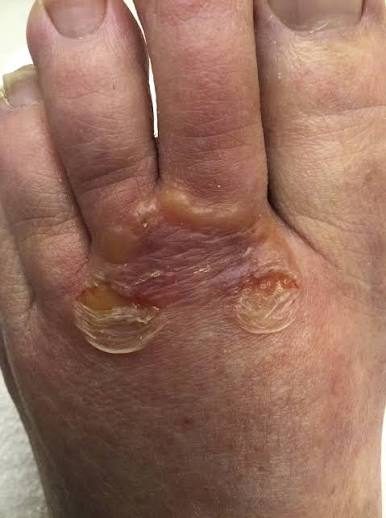
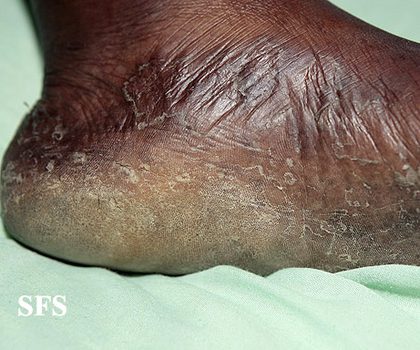
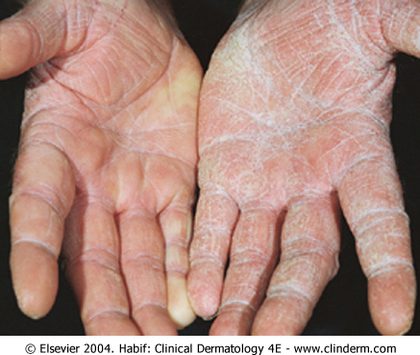
Also tested
- Imidazole antifungals. They block ergosterol synthesis, as clotrimazole and ketoconazole do; ergosterol is a vital component of the fungal cell membrane, so blocking it halts growth and replication.
- Pustular beard eruption with firmly anchored hairs. Bacterial culture helps separate it from tinea barbae by ruling out bacterial folliculitis.
- Safety steps before systemic antifungals for tinea capitis. Review drug interactions and hepatic disease, and obtain baseline liver tests when indicated by the agent, its labeling, and patient risk; baseline testing is indication-driven, not automatic.
- Allylamine antifungals. They destroy the fungal cell membrane, which prevents growth and ultimately kills the fungus. Names end in -fine, such as terbinafine and naftifine.
- Tinea capitis and school. School exclusion is generally unnecessary once effective treatment has started. Avoid sharing personal hair items and clean clippers, combs, brushes, bedding and hats; household contacts may use a sporicidal shampoo.
- Allylamine class. Terbinafine is an allylamine, a class that destroys fungal cell membranes; members end in -fine (terbinafine, naftifine). Imidazoles instead block synthesis of ergosterol, a vital component of the fungal cell membrane.
- Tinea cruris. Commonly called jock itch, it is more common in men and often coexists with tinea pedis, which is why the coexisting foot infection must be treated too.
- Topical antifungal in tinea corporis. Localized disease is treated with topical terbinafine, butenafine or an azole applied to the lesion and 1 to 2 centimeters beyond its border, which covers the advancing edge.
- Vesiculobullous tinea pedis. It presents as a moist, acute, pruritic and painful vesicular or bullous eruption on underlying erythema, and is caused by Trichophyton species like the other two forms.
- Tinea pedis patient education. Drying between the toes after bathing is essential. Also advise antifungal foot powder for shoes, open-toed sandals when possible, sandals in community showers, and changing socks frequently.
- Tinea capitis and shared items. Fungal particles remain viable for months, so hair-care items must not be shared and should be cleaned.
- Tinea barbae management. Use oral antifungal therapy with griseofulvin or terbinafine, plus shaving or hair removal and warm compresses to remove crusts, because topicals do not penetrate the follicle.
- Tinea capitis treatment. It requires oral therapy, because topical agents alone do not penetrate the infected hair shaft; antifungal shampoo reduces viable spore shedding but does not replace oral treatment.
- Tinea corporis (ringworm). Progressive central clearing produces the annular outline. The lesion is a circular, sharply circumscribed, slightly erythematous, dry scaly patch or plaque.
- Recurrent tinea pedis with thickened discolored toenails. Consider oral therapy, treat the coexisting onychomycosis, and reinforce moisture control. An untreated nail reservoir drives recurrence.
- Tinea of the hand with foot scaling. A thickened, dry, scaly palm with interdigital foot scaling is two feet–one hand syndrome, in which the hand used to scratch the foot becomes affected. Patients often blame dry skin or manual labor.
- Tinea manuum. On the dorsum of the hand it shows an annular plaque like tinea corporis; the palm is hyperkeratotic like tinea pedis (thickened, dry and scaly), and palms and soles can be infected at once.
- Variations of tinea pedis. Interdigital, hyperkeratotic and vesiculobullous; all three are caused by Trichophyton species, and the interdigital form is the most common.
6.3 · Objective b — Nails, distant reactions, and steroid-altered tinea
Onychomycosis: confirm before you commit. The single most important sentence in this part of the deck is that many dystrophic nails are not fungal — the deck gives a whole slide of them — so confirm fungus before oral therapy. Confirmation can be potassium hydroxide microscopy, periodic acid–Schiff stain of clippings, culture, or polymerase chain reaction.
Oral terbinafine is first-line for most dermatophyte nail disease: usually 6 weeks for fingernails, 12 weeks for toenails. Itraconazole is the alternative; fluconazole is off label in the United States. Limited disease can use topical efinaconazole, tavaborole or ciclopirox, at lower cure rates. Two counseling points follow directly: improvement requires nail growth, so appearance lags well behind treatment, and coexisting tinea pedis must be treated or the nail simply gets reinfected.
The id (dermatophytid) reaction is a dermatitis at a site distant from the infection — commonly the fingers, with tinea pedis as the primary. It appears 1 to 2 weeks after the primary infection and is extremely pruritic. The mechanism is unknown, possibly delayed-type hypersensitivity. Three criteria establish it:
| 1 | A dermatophyte infection on another part of the body |
| 2 | Absence of fungal elements from the id reaction site |
| 3 | Resolution of the id reaction when the primary infection is treated |
So the treatment is to treat the primary infection — and the examination point is to look for an asymptomatic fissure or maceration in the toe webs that the patient does not know about.
Tinea incognito is tinea whose appearance has been altered by inappropriate treatment, usually topical steroids. The cycle is recognizable: the steroid settles it, stopping the steroid flares it, and more steroid follows. Management is to stop the corticosteroid or calcineurin inhibitor, take potassium hydroxide and culture from an active edge, and warn that inflammation may rebound after withdrawal so the patient does not read the rebound as failure.
What these look like
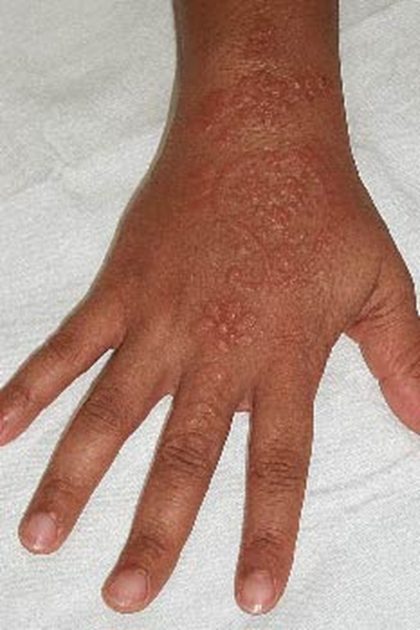
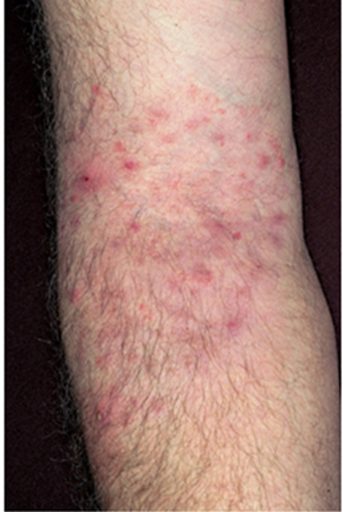
Also tested
- Confirming thickened discolored toenails. Use potassium hydroxide microscopy, periodic acid-Schiff stain of clippings, culture, or amplification testing; sample subungual debris after trimming the onycholytic nail, from the most proximal accessible diseased nail bed.
- Id reaction criteria. A dermatophyte infection is present elsewhere, none is found at the id site, and the eruption resolves. The primary site is potassium hydroxide positive, the id site negative, and onset is 1 to 2 weeks after the primary infection.
- Essential tinea pedis self-care. Dry between the toes after bathing.
- Onychomycosis. Trichophyton rubrum causes most cases (dermatophytes cause most, though yeasts and molds also occur); distal lateral disease produces debris, onycholysis, thickening and crumbling, with discoloration.
6.4 · Objective b — The yeasts: candidal intertrigo and pityriasis versicolor
Yeasts are unicellular fungi that reproduce by budding, and both entities here behave quite differently from a dermatophyte.
Intertrigo is, first of all, not an infection: it is an inflammatory rash from friction, moisture and heat trapped in a body fold, which Candida may then secondarily infect. That ordering matters, because it is why the first line of treatment is environmental — dry the folds gently, reduce friction and occlusion, use moisture-wicking or absorbent material, address incontinence or hyperhidrosis — and the antifungal comes second.
Then the drug distinction the exam will want: topical nystatin treats Candida ONLY; topical azoles treat Candida AND many dermatophytes. A low-potency corticosteroid may be added briefly for marked inflammation, and only alongside adequate antifungal treatment.
Reading a fold rash: satellite papules or pustules support Candida; malodor, erosions or drainage raise concern for bacterial coinfection. And in the groin specifically, scrotal involvement points away from tinea cruris, which typically spares it, and towards candidal intertrigo.
Pityriasis versicolor is an overgrowth of lipid-dependent Malassezia that normally lives on the skin — which is why it is NOT considered contagious, a counseling point patients need. It favors heat, humidity, oily skin, sweating, immunosuppression and corticosteroid exposure, and it recurs, especially in warm climates.
The pigment point. Lesions may be lighter, darker or pink. Hypopigmentation reflects altered melanocyte function and reduced tanning, and recovery can lag months behind clearance of the yeast. So color change alone does not prove treatment failure — look for scale, or confirm with microscopy, before re-treating.
Treatment is topical first-line — ketoconazole, selenium sulfide, zinc pyrithione, ciclopirox or topical terbinafine; one common selenium sulfide approach is daily for 7 days with a 10-minute contact time. Systemic therapy is reserved for extensive, recurrent or refractory disease. Two drug facts are easy marks:
| Oral terbinafine is INEFFECTIVE | Adequate levels are not achieved in sweat. Topical terbinafine does work. |
| Oral ketoconazole must NOT be used | Serious hepatic and adrenal toxicity outweighs the benefit in a superficial infection. |
What these look like
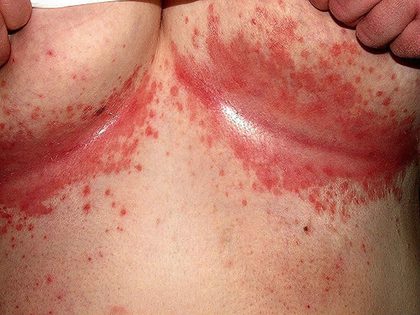
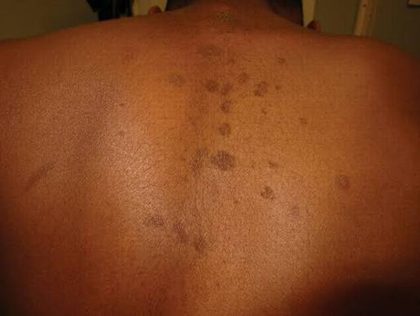
Also tested
- Cutaneous candidiasis appearance. It is beefy red in the depth of the fold, with satellite papules scattered beyond the edge.
- Recurrent candidal intertrigo. Recurrent or extensive disease prompts evaluation for diabetes and immunosuppression.
- Vitiligo versus pityriasis versicolor. Vitiligo is completely white (depigmented) and autoimmune, whereas pityriasis versicolor is hypopigmented rather than depigmented, and it scales.
- Candidal intertrigo. It produces well-demarcated erythematous patches in warm moist folds, with satellite papules and pustules beyond the main area; pruritus with burning pain is typical.
- Pityriasis versicolor distribution and appearance. Lesions favor the trunk, neck and proximal arms as finely scaling macules and patches that are hypopigmented, hyperpigmented or pink and velvety, from 4 to 5 millimeters up to large confluent areas.
- Risk factors for intertrigo and cutaneous candidiasis. Obesity, diabetes, incontinence, occlusion, immobility, antibiotics and immunosuppression. Common sites are inframammary, axillary, abdominal, inguinal, perineal and interdigital folds.
- First step in candidal intertrigo. Correct the environment first: gently dry the folds, reduce friction and occlusion, use moisture-wicking fabric or absorbent material, and address incontinence or hyperhidrosis.
- Sites to inspect for candidal skin disease. The inframammary, axillary, abdominal, inguinal, perineal and interdigital folds are the six named common sites.
- Pityriasis versicolor pallor. Pigment recovery lags months behind clearance, because hypopigmentation reflects altered melanocyte function and reduced tanning; persistent pallor does not indicate treatment failure.
- Extensive or recurrent pityriasis versicolor. Oral terbinafine is not appropriate because adequate drug levels are not achieved in sweat, although topical terbinafine can be effective. The route matters for this organism.
- Candidal intertrigo treatment. Well-demarcated erythematous patches with satellite papules and pustules are treated with a topical azole, which covers both Candida and dermatophytes, whereas topical nystatin treats Candida only.
6.5 · Objective b — Varicella and herpes zoster
Varicella is the primary infection. Its defining feature is lesions in multiple stages at once — macules, papules, vesicles and crusts present simultaneously — concentrated on the trunk, scalp and face. Management is supportive, and the drug rule is avoid aspirin in children, with caution around non-steroidal anti-inflammatories.
Three prevention facts travel together. Contagiousness runs from 1 to 2 days BEFORE the rash until all lesions crust — and in breakthrough disease without crusts, until no new lesions for 24 hours. In healthcare settings use standard, airborne AND contact precautions. Primary prevention is two-dose varicella vaccination.
Herpes zoster is reactivation of virus that stayed latent in cranial-nerve or dorsal-root ganglia, traveling along a sensory nerve to the skin as cell-mediated immunity wanes. The eruption is confined to one or two adjacent dermatomes and STOPS ABRUPTLY AT THE MIDLINE. Distribution: thoracic 55%, cranial 20%, lumbar 15%, sacral 5%.
| Phase | What happens |
|---|---|
| Pre-eruptive | Dysesthesia or pain within the dermatome; lesions by 48–72 hours. May have malaise, myalgia, headache, photophobia, rarely fever. |
| Acute eruptive | Macules and papules, then grouped herpetiform vesicles on an erythematous base (the classic finding). New lesions over 3–5 days. Infectious until lesions have dried. Resolves over 10–15 days; complete healing may take a month. Some have pain without eruption — zoster sine herpete. |
| Chronic | Postherpetic neuralgia — see below. |
The transmission point that gets missed: a susceptible contact does not “catch shingles”. Exposure to vesicular fluid, or airborne virus from disseminated disease, causes varicella. So cover the lesions and avoid susceptible pregnant people, premature infants and immunocompromised people until crusted.
Antiviral timing. Valacyclovir, famciclovir or acyclovir, started as soon as possible, ideally within 72 hours. But treat after 72 hours when new lesions are forming, or there is ophthalmic, neurologic, disseminated, severe or immunocompromised disease. Severe disseminated, visceral, central nervous system or sight-threatening disease gets intravenous acyclovir and specialist management.
Postherpetic neuralgia is the most common complication, defined as pain persisting 90 days or more after rash onset: burning, aching, stabbing, electric shock-like, or evoked by light touch (allodynia). Risk rises with age, severe acute pain, severe rash, ophthalmic involvement and immunocompromise. First line is gabapentin or pregabalin, an appropriate tricyclic antidepressant, or topical lidocaine; a capsaicin patch may help; avoid routine long-term opioids.
Learn this one as a sentence: topical and systemic corticosteroids do NOT prevent postherpetic neuralgia, and must never replace antiviral therapy.
Two complications carry their own urgency:
| Herpes zoster ophthalmicus | Ramsay Hunt syndrome | |
|---|---|---|
| What | Ophthalmic division (V1) of cranial nerve V | Peripheral facial palsy with painful vesicles of the ear canal, auricle or oropharynx; hearing loss, tinnitus or vertigo may occur |
| The sign | Hutchinson sign — lesions on the tip or side of the nose — raises ocular risk, but its ABSENCE does NOT exclude eye involvement | — |
| Do | Start systemic antiviral immediately; same-day ophthalmology for eye pain, visual symptoms, red eye, photophobia, Hutchinson sign, or eyelid/ocular involvement | Antiviral PLUS systemic corticosteroid early when not contraindicated; urgent ear, nose and throat or neurology; protect the cornea if eyelid closure is impaired |
Prevention with Shingrix: two doses of recombinant zoster vaccine for immunocompetent adults 50 and over, and two doses for adults 19 and over who are or will be immunodeficient or immunosuppressed. Standard interval 2 to 6 months; for immunocompromised patients the second dose may be given 1 to 2 months after the first when faster completion helps.
What these look like
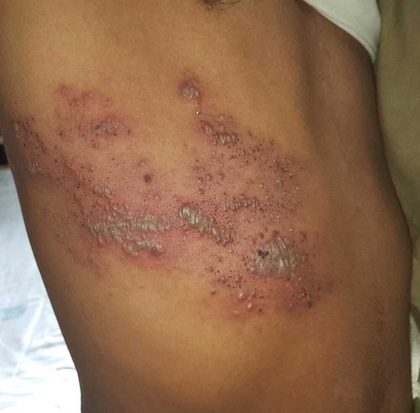
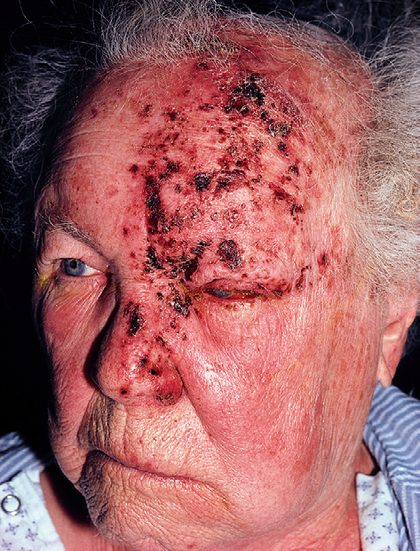
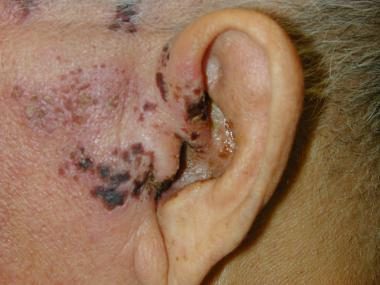
Also tested
- Herpes zoster scarring. It scars when deeper epidermal or dermal layers are compromised by excoriation or secondary infection; otherwise it typically heals without visible sequelae.
- Polymerase chain reaction in herpes zoster. Use it for atypical, disseminated, vaccine-modified or immunocompromised presentations, on vesicle fluid, scab, or cells from the lesion base; typical unilateral dermatomal vesicles are diagnosed clinically.
- Antiviral timing. For a dermatomal vesicular eruption, start antivirals as soon as possible, ideally within 72 hours of rash onset. Treatment is still given after 72 hours when new lesions are forming or there is ophthalmic involvement.
- Varicella complication risk. Adults, pregnancy, newborn age and immunocompromise carry an increased risk of complications.
- Varicella and prompt consultation. Pregnancy, neonatal exposure, immunocompromise or severe complications are the four situations that warrant prompt consultation.
- Testing atypical or immunocompromised varicella-type eruptions. Polymerase chain reaction is preferred, using vesicle fluid, a scab, or cells from the lesion base.
- Hutchinson sign. Herpes zoster lesions on the tip or side of the nose increase ocular risk, but its absence does not exclude eye involvement; systemic antiviral therapy should be started immediately.
- Herpes simplex virus type and site. Either type causes either site: either virus type can cause oral or genital infection, lesion location does not reliably determine type, and typing requires a type-specific test.
- Primary varicella-zoster infection. Its most characteristic feature is lesions in multiple stages of healing appearing simultaneously: macules progress to papules, vesicles, and crusts.
- Herpes zoster pre-eruptive phase. Dysesthesia or pain within the affected dermatome, with lesions appearing by 48 to 72 hours. Malaise, myalgia, headache and photophobia may occur, and rarely fever.
- Zoster over the forehead, upper eyelid and nose tip with eye pain and photophobia. Start systemic antiviral therapy immediately and arrange same-day ophthalmology evaluation. Do not delay the antiviral while awaiting the eye review.
- Severe disseminated zoster with visceral involvement. Manage with intravenous acyclovir with specialist or hospital management, as also for central nervous system or sight-threatening disease.
- Cause of herpes zoster. It results from reactivation of latent varicella-zoster virus, which stays latent in cranial-nerve or dorsal-root ganglia; risk rises with age and impaired cell-mediated immunity.
- Phases of a dermatomal grouped-vesicle eruption. Pre-eruptive (dysesthesia or pain in the dermatome, lesions by 48 to 72 hours), acute eruptive (grouped herpetiform vesicles on erythematous base, new lesions over 3 to 5 days), and postherpetic neuralgia (chronic).
- Varicella contagious period. The child is contagious from 1 to 2 days before the rash until all lesions have crusted; contagiousness begins before the rash is visible.
6.6 · Objective b — Herpes simplex and herpetic whitlow
Start with the fact that undoes the usual assumption: either type can cause oral or genital infection, so lesion location does NOT reliably determine type. What does differ is behavior over time — HSV-1 genital infection generally recurs and sheds less often than HSV-2 genital infection.
Transmission occurs through contact with infected oral or genital secretions or lesions, and can occur during asymptomatic shedding. It is a double-stranded DNA Herpesviridae virus, neurovirulent, producing latent but lifelong infection.
First episodes are more prominent and longer; recurrences are milder and shorter. A prodrome of tenderness, pain, paresthesias or burning precedes the lesions — with localized pain, tender lymphadenopathy, headache, generalized aching and fever characteristic — though some patients have no prodrome. On examination: grouped vesicles on an erythematous base breaking down into a shallow painful ulcer, lasting about two weeks and healing without scarring. Reactivation triggers are stress, illness, menstruation and ultraviolet light.
Testing has four rules, and two of them are prohibitions.
| Do | Swab a fresh vesicle, ulcer base or crust for type-specific amplification testing — the preferred test |
| Know | Culture is less sensitive, especially in healing or recurrent lesions, and a negative result does not exclude. A negative older-lesion swab does not exclude either, because shedding is intermittent. |
| Do NOT | Use HSV immunoglobulin M. Confirm a low-positive HSV-2 serology with a second method. |
| Do NOT | Routinely screen asymptomatic adults serologically. |
And evaluate a genital ulcer for other causes including syphilis, by risk. The differential is worth holding as a contrast: chancroid (Haemophilus ducreyi, painful necrotizing ulcers, inguinal lymphadenopathy) against syphilis (solitary raised papules that erode, usually painless), plus trauma and candidiasis.
Treat every first clinical episode with oral acyclovir, valacyclovir or famciclovir. For recurrent genital disease, choose between patient-initiated episodic and daily suppressive therapy. Topical antivirals provide minimal benefit.
Counseling is where the honest wording matters: suppressive valacyclovir LOWERS HSV-2 transmission, and condoms REDUCE but do not eliminate risk — neither abolishes it. Avoid sexual or direct lesion contact during the prodrome as well as while lesions are active.
Herpetic whitlow is HSV of the distal finger, often inoculated through broken skin: prodromal burning or tingling, then grouped vesicles on an erythematous, swollen digit, sometimes with fever or lymphangitis. It mimics bacterial felon or paronychia, contact dermatitis, and blistering dactylitis, which sets up the one instruction to carry out of this topic: DO NOT incise and drain — it does not treat HSV and can delay healing. Cover the lesions, use hand hygiene, avoid contact with mucosa or broken skin until healed, and treat bacterial superinfection only when it is present.
What these look like
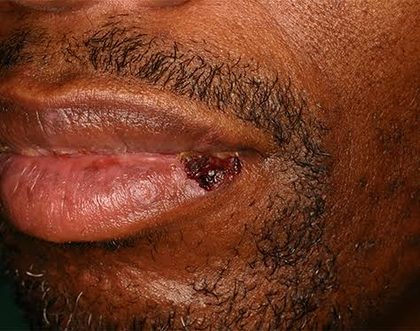
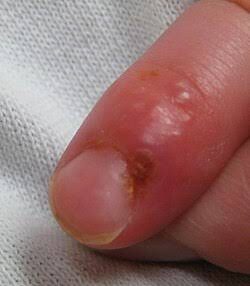
Also tested
- Dermatitis herpetiformis immunology. Immunoglobulin A antibodies against epidermal transglutaminase form complexes that deposit in the dermal papillae; complement and neutrophils are then activated, producing subepidermal blisters.
- Herpes simplex virus. It is a double-stranded DNA virus of the Herpesviridae family that produces latent but lifelong infection; latency for life is its defining feature.
- Genetics of dermatitis herpetiformis. HLA-DQ2 and HLA-DQ8 are strongly associated, and nearly all patients have underlying gluten-sensitive enteropathy even when gastrointestinally asymptomatic.
- Recurrent herpes-associated erythema multiforme. Chronic suppressive antiviral therapy, such as aciclovir 400 mg twice daily, is appropriate, because preventing the herpes recurrence prevents the eruption.
- Recurrent erythema multiforme after oral herpes. Recurrent disease is strongly associated with recurrent herpes simplex, and long-term suppression is suppressive acyclovir 400 mg twice daily or valacyclovir 500 mg daily.
- Low-positive herpes simplex type 2 serology. Confirm it with a second method when one is available, because low-positive results may be false positives.
- Herpetic whitlow. Do not incise; cover it and give antivirals. Incision and drainage does not treat herpes simplex virus and can delay healing; early oral acyclovir, valacyclovir, or famciclovir may shorten the episode.
- Herpes simplex virus. A tight group of vesicles and erosion at the vermilion border, recurring in the same place.
- Herpes simplex virus infection. A first episode gives painful grouped vesicles on an erythematous base, for example on the vulva, that become shallow painful ulcers, with a systemic prodrome of fever, headache and tender inguinal nodes.
6.7 · Objective b — Molluscum contagiosum and warts
Molluscum contagiosum is a benign poxvirus infection producing smooth, dome-shaped, centrally umbilicated papules — discrete, firm, flesh-colored and pearly, averaging 3 to 5 mm, with central umbilication characteristic. It spreads by direct skin contact, shared contaminated objects and autoinoculation.
Most immunocompetent patients clear spontaneously, though it may take months to several years — and that slow timeline is exactly why observation is appropriate for many patients: procedures may blister, pigment or scar. When treatment is chosen:
| Agent | Applied by | From age |
|---|---|---|
| Berdazimer 10.3% gel (Zelsuvmi), once daily | At home | 1 year |
| Cantharidin 0.7% (Ycanth) | A clinician | 2 years |
| Curettage or cryotherapy | A clinician | — |
| Topical retinoids | Off label | |
Three higher-risk presentations change what you do. Genital lesions in adolescents or adults may be sexually transmitted; assess for other infections as appropriate. Genital lesions in a child require context-sensitive assessment — location alone does NOT prove abuse. And extensive or giant facial lesions warrant evaluation for immunosuppression, including HIV where appropriate.
Warts are benign proliferations caused by human papillomavirus infecting keratinocytes, transmitted by skin-to-skin contact, autoinoculation and contaminated surfaces. The anatomy is a favorite point: a wart is confined to the EPIDERMIS, but it expands and displaces the dermis, giving the impression that it extends deeper. Turn one over and the underside is round and smooth — there are NO ROOTS.
| Type | Appearance | Where |
|---|---|---|
| Verruca vulgaris | Under 1 cm, elevated round papules, rough grayish surface. Tiny red or black dots are thrombosed dilated capillaries; trimming the surface makes them more prominent. | Hands, favoring fingers and palms. Periungual, lip and tongue in nail biters. Ages 5–20. |
| Verruca plana (flat) | Multiple smooth, slightly elevated, flat-topped, skin-colored to light-brown papules | Face, forehead, dorsal hands, shins. Shaving spreads them by autoinoculation. |
| Verruca plantaris | On the weight-bearing surface; clustering produces a mosaic wart | Soles. Therapy only if PAINFUL. Salicylic acid 40% or cryotherapy. |
Diagnosis is clinical; biopsy is generally unnecessary but may suit immunocompromised patients or lesions of uncertain etiology — that is, ruling out squamous cell carcinoma, which sits in the differential alongside molluscum contagiosum and seborrheic keratosis.
The treatment principle to state plainly to a patient: no therapy eradicates human papillomavirus with certainty, and recurrence can occur. Choose treatment by location, symptoms, age, pregnancy status, immune status, and risk of scarring or dyspigmentation. Avoid excessive freezing or destructive therapy for benign lesions likely to resolve spontaneously — cryotherapy every 2 to 3 weeks may cause pain, blistering and pigment change. Biopsy or refer atypical, bleeding, ulcerated, growing or refractory lesions, and refer periungual, facial, extensive, recalcitrant, diagnostically uncertain or immunocompromised cases.
What these look like
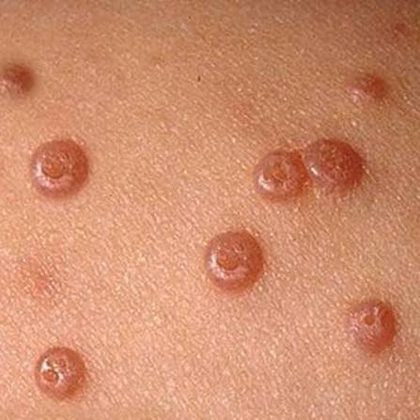
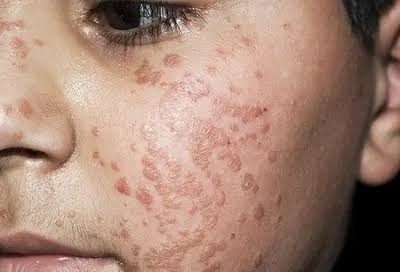
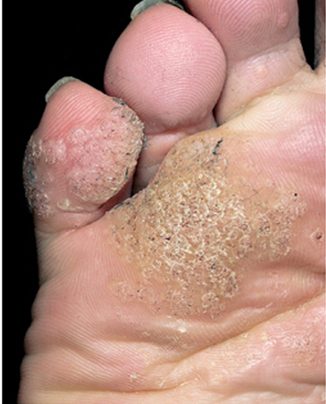
Also tested
- Treating cutaneous warts. No therapy eradicates human papillomavirus with certainty, and recurrence can occur. Choose treatment by location, symptoms, age, pregnancy status, immune status, and risk of scarring or dyspigmentation, avoiding excessive freezing or destruction.
- Plantar warts. They occur on weight-bearing surfaces, and clustered together they form a mosaic wart.
- Red or black dots in a wart. Tiny dots are thrombosed capillaries, made more prominent by trimming the surface, and distinguish a wart from a callus, which lacks them.
- Molluscum contagiosum natural history. In immunocompetent patients most clear spontaneously, although resolution may take months to several years. Clearance is spontaneous but often slow.
- Warts. Caused by human papillomavirus, which infects keratinocytes and remains confined to the epidermis, producing a benign proliferation.
- Variations of verruca. Five variants are recognized: verruca vulgaris, verruca plana, verruca plantaris, mosaic warts, and genital warts.
- Verruca vulgaris. It occurs most often between 5 and 20 years, with spontaneous resolution; common warts usually resolve on their own.
6.8 · Objective c — Care strategies by age
Objective c asks you to apply all of the above across infant, child, adolescent, adult and elderly populations. The deck's age-specific content clusters as follows:
| Population | What changes |
|---|---|
| Infant | Newborn age increases varicella complication risk, and neonatal exposure warrants prompt consultation. Molluscum: berdazimer is approved from age 1. Intertrigo in the diaper area and folds. |
| Child | Tinea capitis is predominantly a disease of preadolescent children and the commonest fungal infection in children — oral therapy, adjunctive shampoo, contact and pet evaluation, and generally no school exclusion once treated. Avoid aspirin in varicella. Molluscum is common and usually self-limiting; cantharidin from age 2. Genital molluscum requires context-sensitive assessment. Common warts peak at 5–20. |
| Adolescent | After puberty, sebum fatty acid changes inhibit scalp dermatophyte growth, so tinea capitis falls away. Tinea cruris and tinea pedis rise with sport, occlusive footwear and communal showers. Genital molluscum may be sexually transmitted — assess accordingly. Flat warts spread by shaving. Zoster vaccine from 19 if immunosuppressed or about to be. |
| Adult | Tinea pedis is the commonest dermatophyte infection in adults; tinea cruris is commoner in men. Adults and pregnancy increase varicella complication risk. Herpes simplex counseling and suppressive therapy. Shingrix two doses from 50 in the immunocompetent. Check pregnancy status before choosing a wart treatment. |
| Elderly | Zoster risk rises with age, and so does postherpetic neuralgia risk. Individualize neuropathic agents for kidney function, falls, anticholinergic burden and interactions. Onychomycosis risk rises with age, diabetes and vascular disease; check hepatic disease and interactions before oral terbinafine. Intertrigo risk rises with immobility and incontinence. |
Immunocompromise cuts across every age and changes the answer in the same direction each time: more extensive disease, a lower threshold for systemic therapy, amplification testing rather than clinical diagnosis, and referral. It raises complication risk in varicella, drives atypical and disseminated zoster, produces more numerous or giant molluscum lesions, and moves warts and dermatophytosis towards oral therapy and specialist input.
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Tinea capitis (scalp) | Oral therapy is required — topical agents do not penetrate the infected hair shaft. Terbinafine generally favored for Trichophyton; griseofulvin often favored for Microsporum. Review interactions and hepatic disease; baseline liver tests when indicated by the agent and patient risk. Adjunct: selenium sulfide 1–2.5% or ketoconazole 2% shampoo, 2–3 times weekly — reduces spore shedding but does not replace oral therapy. |
| Black dot tinea capitis | As for tinea capitis: oral antifungal therapy. |
| Tinea barbae — inflammatory | Oral antifungal therapy is required — topicals do not penetrate the hair follicle. Griseofulvin or terbinafine. Shave or remove hair; warm compresses to remove crusts and debris. |
| Tinea barbae — noninflammatory | As for the inflammatory form — oral antifungal therapy. |
| Tinea corporis (body) — “ringworm” | Localized: topical terbinafine, butenafine or an azole, applied to the lesion and 1–2 cm beyond its border, for the product-specific duration and continued past visible improvement. Systemic: consider oral therapy for extensive, follicular, immunocompromised, refractory or recurrent disease — terbinafine commonly, or itraconazole or fluconazole by organism and interactions. |
| Tinea cruris (groin) — “jock itch” | Localized: topical allylamine (terbinafine) or azole (ketoconazole). Reserve oral therapy for extensive or refractory disease. |
| Tinea pedis — interdigital | Topical terbinafine or butenafine, or an azole. Consider oral therapy for extensive, recurrent, refractory or immunocompromised disease. Treat coexisting onychomycosis and reinforce moisture control. |
| Tinea pedis — hyperkeratotic | Antifungal plus a KERATOLYTIC for the thickening. Oral therapy for extensive, recurrent, refractory or immunocompromised disease. |
| Tinea pedis — vesiculobullous | Topical antifungal; oral therapy for extensive or refractory disease. |
| Onychomycosis (tinea unguium) | Oral terbinafine is first-line for most dermatophyte disease: usually 6 weeks for fingernails, 12 weeks for toenails. Review hepatic disease and interactions; baseline liver tests per labeling and risk. Itraconazole is an alternative; fluconazole is off label in the United States. Limited disease: topical efinaconazole, tavaborole or ciclopirox — lower cure rates. |
| Tinea manuum (hand) | Same as tinea pedis — topical for localized disease; oral for extensive, recurrent, refractory or immunocompromised disease. Treat coexisting onychomycosis; reinforce moisture control. |
| Id (dermatophytid) reaction | Treat the primary dermatophyte infection — the id reaction resolves with it. |
| Tinea incognito | Topical antifungal for localized disease; systemic for extensive, follicular or refractory infection. |
| Cutaneous candidiasis and intertrigo | Correct the environment first: gently dry the folds, reduce friction and occlusion, use moisture-wicking or absorbent material, address incontinence or hyperhidrosis. Topical nystatin treats Candida ONLY; topical azoles treat Candida AND many dermatophytes. Consider a low-potency corticosteroid briefly for marked inflammation, and only alongside adequate antifungal treatment. |
| Pityriasis versicolor (tinea versicolor) | Topical therapy is first-line: ketoconazole shampoo or cream, selenium sulfide, zinc pyrithione, ciclopirox, or topical terbinafine. One common selenium sulfide approach is daily for 7 days with a 10-minute contact time. Systemic for extensive, recurrent or refractory disease: oral fluconazole or itraconazole. Oral terbinafine is INEFFECTIVE — adequate levels are not achieved in sweat (topical terbinafine does work). Do NOT use oral ketoconazole — hepatic and adrenal toxicity outweigh benefit in a superficial infection. |
| Varicella (chickenpox) | Supportive care; AVOID ASPIRIN in children and use caution with non-steroidal anti-inflammatories. Consider early oral antivirals for higher-risk patients; intravenous acyclovir for severe or disseminated disease. |
| Herpes zoster (shingles) | Preferred oral agents: valacyclovir, famciclovir or acyclovir; adjust for renal function. Start as soon as possible — ideally within 72 hours of rash onset. Treat AFTER 72 hours when new lesions are forming, or there is ophthalmic, neurologic, disseminated, severe or immunocompromised disease. Intravenous acyclovir and specialist or hospital management for severe disseminated, visceral, central nervous system or sight-threatening disease. Acetaminophen or a non-steroidal for mild pain; cool compresses, calamine, loose clothing, lesion coverage. |
| Postherpetic neuralgia | First line: gabapentin or pregabalin, an appropriate tricyclic antidepressant, or topical lidocaine. A capsaicin patch may help. Individualize for kidney function, falls, anticholinergic burden and interactions. Avoid routine long-term opioids; refer severe, persistent or disabling pain. |
| Herpes zoster ophthalmicus | Start systemic antiviral therapy IMMEDIATELY. Same-day ophthalmology evaluation for eye pain, visual symptoms, red eye, photophobia, Hutchinson sign, or eyelid or ocular involvement. |
| Ramsay Hunt syndrome (herpes zoster oticus) | Antiviral therapy PLUS a systemic corticosteroid, started early when not contraindicated — one of the few places a steroid is added. Urgent ear, nose and throat or neurology evaluation. |
| Herpes simplex virus (HSV-1 and HSV-2) | Treat EVERY first clinical episode with oral acyclovir, valacyclovir or famciclovir. Recurrent genital HSV: patient-initiated episodic or daily suppressive therapy. Topical antivirals provide minimal benefit for genital herpes. |
| Herpetic whitlow | DO NOT INCISE AND DRAIN — it does not treat HSV and can delay healing. Early oral acyclovir, valacyclovir or famciclovir may shorten symptoms; consider suppression for frequent recurrence. Treat bacterial superinfection only when it is present. |
| Molluscum contagiosum | Observation is appropriate for many patients — procedures may blister, pigment or scar. Berdazimer 10.3% gel (Zelsuvmi), once daily at home, age 1 and over. Cantharidin 0.7% (Ycanth), applied by a clinician, age 2 and over. Others: curettage or cryotherapy; topical retinoids are off label. Treat associated dermatitis. |
| Verruca vulgaris (common warts) | Observation is reasonable — many resolve spontaneously. Salicylic acid. Cryotherapy every 2–3 weeks — may cause pain, blistering and pigment change. Biopsy or refer atypical, bleeding, ulcerated, growing or refractory lesions. |
| Verruca plana (flat warts) | Observation is reasonable because spontaneous resolution is common. Options include carefully selected salicylic acid, topical retinoids, or cryotherapy. |
| Verruca plantaris (plantar warts) | Plantar warts do not require therapy unless they are PAINFUL. Salicylic acid 40% Cryotherapy |
Also tested
- Tinea pedis prevention. Drying between the toes after bathing is essential, alongside antifungal foot powder for shoes, open-toed sandals when possible, sandals in community showers, and frequent sock changes.
7 · Benign Skin Lesions
Instructional Objectives
Lecture 7 — Professor Hugh E. Griffenkranz, MPAS, PA-C
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis for the following benign skin lesions:
- Clavus and callous
- Scars (hypertrophic, keloid)
- Cutaneous horn
- Skin tags (acrochordon, polyps)
- Pressure injury
- Pilonidal cyst
- Dermatofibroma
- Keratoacanthoma
- Epidermal cyst
- Syringoma
- Vascular lesions (nevi, hemangiomata, telangiectasia)
- Pyogenic granuloma
- Neurofibroma
- Xanthelasma
- Lipoma
- Mucous cyst
- Sebaceous hyperplasias
- Identify medical strategies for common benign skin lesions in infants, adolescent, adult, and elderly
107 minutes with Professor Griffenkranz, across two segments. Both transcripts were read and diffed and every factual claim below was checked against the deck. No factual errors were found in this lecture — what it carries instead is unusually direct exam intelligence: he says outright what he will not ask, and in one place describes the shape of a question he intends to set. The one loose characterization and the one non-deck aside are both marked below.
| He said | What it means for you |
|---|---|
| “We all know the layers of the epidermis? Yes, of course you do. Am I going to ask you that? No. Do you need to know where things are? Yes.” [2:58] | A DE-EMPHASIS, corroborated word-for-word in both transcripts. Do not spend time memorizing the strata of the epidermis. Do know where a lesion sits — which layer it involves and how deep it goes. That distinction is doing real work across this whole block: it is what separates a wart (epidermis only) from a corn, and what the entire pressure injury staging system is built on. |
| “What is the take-home point? Know the four phases of wound healing. At least be able to recognize them. If you’re given a group of four, better know which one is one of the four phases of wound healing and which three are not.” [20:17] | He described the QUESTION, not just the topic. Expect four options where one is a real phase and three are not, and be able to pick it cold: hemostasis → inflammation → proliferation → remodeling. He tied it straight to the pathology as well — “if there’s a disruption in any one of those phases, you will have abnormal wound healing” — which is the link to keloid and hypertrophic scar in 7.2. |
| “Look at the stages, one, two, three, four…
You need to know these stages.” [48:44] “The unstageable and deep tissue are just more complications of a stage four. I’m not so worried about you knowing that, but I do want you to know the four stages of a pressure sore.” [49:47] |
The clearest steer in the lecture: learn 1–4 cold. His own summary is a good
revision target — stage 1 non-blanchable erythema of intact skin, stage 2 partial thickness,
stage 3 “goes down to the fat”, stage 4 “full thickness down to the
muscles, tendons, and bones”. But the slide does not support “complications of a stage four”. On the staging tables, unstageable and deep tissue injury are their own categories, not a worse stage 4: unstageable is full-thickness loss whose extent cannot be determined because slough or eschar obscures it, and deep tissue injury is persistent non-blanchable deep red or purple discoloration, with skin either intact or not. Follow his steer on where to spend your effort, but do not carry away the definition — a question could reasonably ask you to tell those two apart. |
| “And then this is key. When everybody talks about a sign that’s unique to a lesion, you’ve got to remember it. It’s the dimple sign… lateral pressure around the lesion, the center of the lesion invaginates or creates a dimple.” [1:02:21] | Dermatofibroma, and it matches the slide exactly. He also gave the rest of the picture: a 0.5 to 1 cm nodule, hyperpigmented, with a halo, and “mostly on the legs”, sometimes the arms. His general rule is worth taking literally — a named sign attached to one lesion is exam material by construction. |
| “Neurofibromatosis. Also known as von Recklinghausen disease. You need to know that.… comes in three types, type 1, type 2, and then type 3. Sometimes they’re referred to as Schwannomatosis.” [1:34:19] | Verbatim from slide 97, including the three types: NF1 (NF1 gene,
chromosome 17), NF2 (NF2 gene, chromosome 22), schwannomatosis, sometimes
called NF3 (SMARCB1 and LZTR1, chromosome 22). Section 7.7 carries all three with their
genes. His “Elephant Man” aside is not deck content, and the association is disputed — Joseph Merrick is now generally thought to have had Proteus syndrome rather than neurofibromatosis. Keep it as a memory hook if it helps; do not carry it as a fact. |
| “Who would be at risk for developing pressure ulcers? Bedbound patients… elderly… diabetics… and people that are in a negative nitrogen balance… we want to be healing, we want to have all our proteins.” [48:10] | His clinical addition, not a slide fact. The deck’s prevention slide asks for a nutrition assessment but never mentions nitrogen balance or malnutrition. The reasoning is sound and worth holding — a catabolic, protein-depleted patient cannot build granulation tissue — but it is his framing rather than something to quote back. |
| “Keloids are very prominent in dark-skinned races, very common in African-Americans and Latinos. Caucasians are not immune from keloids.” [20:40] | The deck associates keloid with darker skin; his caveat is the useful nuance. Note also his timing: “sometimes it may happen weeks to months after the initial trauma”, which is exactly the discriminator against a hypertrophic scar (within four weeks, and confined to the wound). |
| “Most common on the trunk… small, about five millimeters, smooth, firm, deep red… that blanch with pressure.” [1:29:07] | Cherry angioma, and correct — slide 86 says “blanch with pressure (if fibrotic, may not blanch completely)”. Worth flagging because a blanching vascular papule is counter-intuitive if you have learned that vascular lesions do not blanch; the slide carries the caveat, so learn both halves. He also gave pyogenic granuloma as head, neck and fingers, painless but bleeds easily, after trauma. |
Quoted from the 20 August 2026 lecture recording, 107 minutes across two segments, with timestamps. Both transcripts read and diffed. Every factual claim was checked against the deck; the two items that are not deck content are marked as such above.
7.1 · Objective a — Corns, calluses, and the wart that mimics them
All three are keratin responses to mechanical stress, and the exam question is which one you are looking at. Two features settle it: whether the skin lines run through the lesion, and which direction of pressure hurts.
| Clavus (corn) | Callus | Verruca vulgaris (wart) | |
|---|---|---|---|
| Cause | Focal pressure, e.g. ill-fitting shoes | Broad-area pressure and friction | Human papillomavirus |
| Structure | Cone-shaped central core of hard keratin pointing in | Diffuse thickening, no core | Cauliflower surface, blackened center |
| Size & shape | Well defined, <1.5 cm | Larger, irregular, poorly defined | Variable |
| Skin lines | Run through | Run through | Interrupted |
| Pain | On direct downward pressure | Usually painless | May hurt on side pressure |
| Pressure areas? | Yes | Yes | Not specific to them |
What these look like
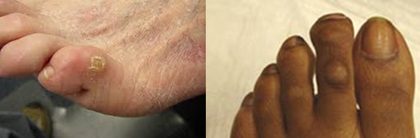
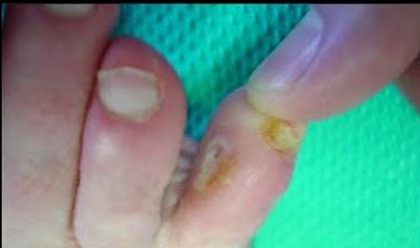
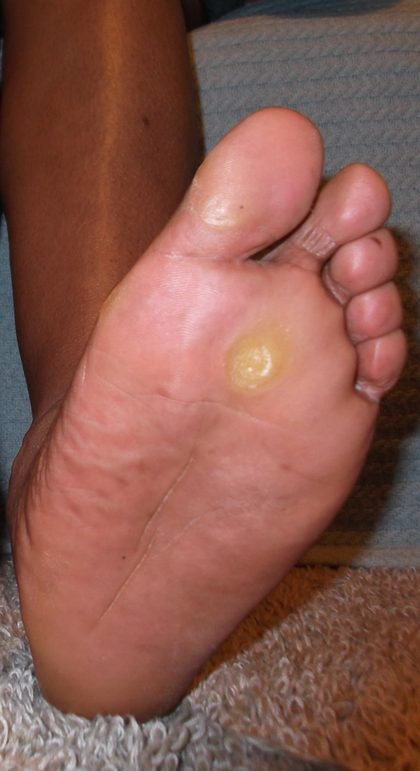
Hard corn (clavus durum) favors the dorsal and lateral fifth toe. Soft corn (clavus mollum) sits in the fourth-to-fifth web space and is soft because moisture between the toes macerates it. A callus that forms acutely and severely produces a blister instead.
Also tested
- Calluses. They typically develop on the palms of the hands or the balls of the feet; if the process is acute and severe, a blister forms.
- Preventing callus recurrence. Well-fitting shoes and socks and pads inside the shoe remove the friction so the lesion stops re-forming; tight shoes, high heels and wearing shoes without socks are named as causes.
- Corn and callus management. Use padding and avoid poorly fitting footwear, with over-the-counter keratolytic products: remove the pressure first, then thin the keratin.
- Clavus (corn). Mechanical trauma such as ill-fitting shoes causes hyperkeratosis with a cone-shaped central core of hard keratin pointing into the skin; the central core separates a corn from a callus.
- Painful corn with diabetes mellitus. A diabetic foot lesion goes to podiatry: refer the patient to podiatry.
- Wart versus corn or callus. A wart interrupts the skin lines, has a blackened center, and is not confined to pressure areas; corns and calluses both let the skin lines run through.
7.2 · Objective a — Abnormal wound healing: keloid and hypertrophic scar
Normal healing runs hemostasis → inflammation → proliferation → remodeling, and the maturing scar gains tensile strength through progressive cross-linking of collagen fibers. Abnormal healing is the loss of the control mechanisms that regulate that balance. Two things go wrong, and telling them apart is the highest-yield contrast in this lecture.
| Hypertrophic scar | Keloid | |
|---|---|---|
| Timing | Develops within four weeks, soon after surgery | Develops slowly, may appear months after the trauma |
| Course | Stable, then regresses and flattens | Enlarges for months to years, rarely improves, tends to recur |
| Margins | Confined to the wound | Extends beyond the wound |
| Where | Where scars cross joints or skin creases at a right angle | Ear lobe, shoulders, sternal notch; rarely across joints |
| Surgery | Improves with appropriate surgery | Often worsened by surgery |
| Incidence | Frequent | Rare |
| Skin color | No association | Associated with dark skin color |
The last four rows come from slide 24, which is an image of a table and appears nowhere in the deck’s text.
| Keloid treatment | Detail worth remembering |
|---|---|
| Silicone gel sheets | 12–24 h/day for up to a year; theory is raised scar temperature increasing collagenase activity |
| Compression | 25 mmHg, 24 h/day, 6–12 months; possibly tissue hypoxia and fibroblast degeneration |
| Intralesional steroid | Reduces collagen production, eventually flattens; may cause tissue atrophy |
| Surgical removal | 50–100% recurrence, often larger — always follow with intralesional steroid |
| Radiation | Only in the first two weeks after excision |
| Cryotherapy | Flattens; causes hypopigmentation |
| Laser | Shrinks collagen or induces microvascular thrombosis; best combined with intralesional steroid |
| Intralesional fluorouracil | Antimetabolite; inhibits fibroblast proliferation |
What these look like
Both are diagnosed clinically, and for both, biopsy only if there is genuine doubt, because it may induce new scarring. Differential for each: the other one, dermatofibroma, and foreign-body granuloma.
Also tested
- Post-surgical advice for keloid-prone patients. Avoid stretching the immature scar, avoid hot baths, keep the wound clean, and avoid body piercings; stretching provokes scar inflammation and overgrowth, and hot baths can aggravate surgery-induced inflammation.
- Radiation for keloids. It may be used during the first two weeks after the keloid has been excised, as an adjunct to surgery rather than a primary treatment.
- Compression therapy for keloids. The regimen is 25 millimeters of mercury, round the clock, for six to twelve months; the mechanism is not understood but possibly induces tissue hypoxia with fibroblast degeneration and subsequent collagen degradation.
- Surgical excision of a keloid alone. Recurrence is fifty to one hundred percent and the recurrent lesion is often larger than the original, so excision is never done alone and steroid injection follows; combination therapy has the best success rates.
- Raised scar confined to the incision. A raised, firm, red scar that stops exactly at the edges of the original incision should stay stable and then flatten with time, which is why observation is reasonable.
- Keloid management. Prevention is the most important treatment. High-risk patients should avoid cosmetic procedures such as ear piercing; post-surgical education includes avoiding stretching of an immature scar and avoiding hot baths.
- Silicone sheets for keloid. They are worn twelve to twenty-four hours a day for up to a year, theorized to raise scar temperature and increase collagenase activity.
- Silicone gel sheets for scars. The theory is that occlusive dressings warm the scar, raising collagenase activity; they are worn 12 to 24 hours a day for up to a year.
- Keloid treated with laser. The best result comes from combining the laser with intralesional steroids; laser works by shrinking collagen or inducing microvascular thrombosis.
- Hypertrophic scar versus keloid timing. Hypertrophic scars develop soon after surgery and usually improve with time; keloids may develop months after the trauma and rarely improve.
- Keloid. Scar tissue that has grown beyond the boundaries of the original wound.
7.3 · Objective a — Cutaneous horn and skin tags
A cutaneous horn is not a diagnosis. It is a hard conical keratin projection that arises from the surface of another lesion — actinic keratosis, wart, seborrheic keratosis, keratoacanthoma, or basal or squamous cell carcinoma. The process at the base is what matters, and often no clinical feature distinguishes benign from malignant. So the answer to “what do you do with a cutaneous horn” is always deep shave biopsy to sample the underlying tissue, and management follows whatever that shows.
Epidemiology: Caucasians over 50, males equal to females, on head, neck and upper extremities — commonly the sun-exposed face, ears and hands.
Acrochordon is a fibroepithelial pedunculated papilloma: a narrow stalk with a broad tip, 1 mm to 10 mm, soft and skin-colored. Increased in females and obese patients, in friction sites — neck, axilla, groin. Present in 60% of people by age 70. Treatment is for cosmesis: scissor excision, cryotherapy or electrodesiccation, and anesthesia is not necessary.
What these look like
Also tested
- Cutaneous horn management. It depends on the underlying etiology, with excision to the standard for the tumor type and location if malignant; treat what is at the base, not the horn.
- Cutaneous horn epidemiology. It is seen in Caucasians over fifty, on the head, neck and upper extremities, such as a lesion on the ear.
- Cutaneous horn. It arises from the surface of another lesion, benign or malignant (actinic keratosis, warts, squamous cell carcinoma). There is often no clinical feature to distinguish them, so the lesion at the base must be diagnosed.
- Skin tags. Increased in females and obese patients, in areas of friction such as the neck, axilla and groin; very common, present in sixty percent of people by age seventy.
7.4 · Objective a — Pressure injury and pilonidal disease
A pressure injury is unrelieved pressure damaging underlying tissue, generally soft tissue compressed between a bony prominence and an external surface for a prolonged time. The staging system below is transcribed from slides 33 and 34, which are images.
| Stage | Definition |
|---|---|
| 1 | Localized area of non-blanchable erythema of intact skin |
| 2 | Partial-thickness skin loss with exposed dermis; wound bed viable, pink or red, may be moist, shiny or dry |
| 3 | Full thickness skin loss; adipose tissue is visible |
| 4 | Full thickness skin and tissue loss; exposed fascia, muscle, tendon, ligament, cartilage or bone |
| Unstageable | Obscured full thickness loss; extent cannot be determined because of slough or eschar |
| Deep tissue | Persistent non-blanchable deep red or purple discoloration; skin can be intact or non-intact |
What these look like
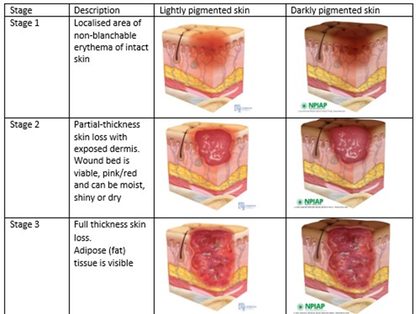
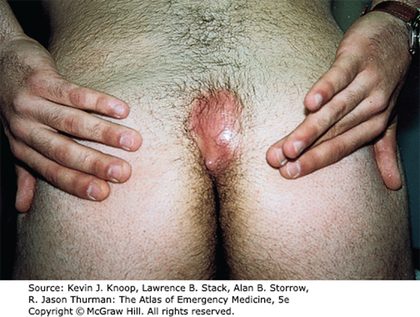
Both slides illustrate every stage in lightly pigmented AND darkly pigmented skin. That is not decoration. Stage 1 is defined by non-blanchable erythema, and erythema is exactly the finding that is hardest to see and easiest to miss on darker skin — which is the same point Professor Jaquith made about recognizing dermatological disease across skin types.
The best measure is prevention: frequent skin assessment, nutrition assessment, moisture control and skin care (clean and dry, manage incontinence, barrier creams), reposition every two hours, manage pain, improve mobility, specialty mattresses. Management otherwise depends on stage: refer to a wound care specialist, control infection risk, silicone and hydrocolloid dressings, and surgical referral for debridement — which removes necrotic tissue, eschar and slough because they promote infection, delay granulation and impede healing — and for wound closure.
Pilonidal disease starts when disruption of the skin over the coccyx leaves a pit that draws in hair and debris, causing follicular plugging; ingrown hairs prevent drainage and promote abscess. Male to female 3:1; once thought congenital, now believed acquired; recurrence is common. Risk factors: obesity, local trauma or irritation, sedentary lifestyle, increased hair density in the natal cleft, family history.
Acute abscess: sudden pain and swelling in the gluteal cleft; warm, tender, erythematous, purulent or bloody drainage, possibly fluctuant — a wave-like fluid shift on palpation indicating the lesion is fluid filled. Chronic: recurrent drainage from one or more sinus tracts, sometimes with a hair protruding.
Also tested
- Pilonidal disease education. Maintain good hygiene, and seek care if an abscess occurs; recurrence is common, so this is ongoing advice.
- Pilonidal disease testing. No diagnostic testing is usually needed; the diagnosis is clinical.
- Pilonidal disease presentation. Acutely, sudden pain and swelling in or along the gluteal cleft; chronically, recurrent drainage and pain from one or more sinus tracts. A hair may occasionally be seen protruding from a sinus opening.
- Pilonidal disease risk factors. Obesity, sedentary life and dense cleft hair; the male to female ratio is 3 to 1.
7.5 · Objective a — The nodules that must be told from a cancer
These four sit opposite a malignancy in their differential, and that is what makes them examinable rather than trivia.
| Lesion | What it is | Key feature | Diagnosis & management |
|---|---|---|---|
| Dermatofibroma | Dermal fibroblasts in dense clusters; 0.5–1 cm; legs then arms; F:M 2:1; may follow trauma, viral infection or insect bite | Dimple sign — retracts beneath the skin on lateral compression. Brown halo, pink hue, raised scaly center. Most common painful skin tumor | Dermoscopy: peripheral pigment network with central white mass. Often no treatment; small lesions take a shave or punch biopsy that is both diagnostic and therapeutic. Differential includes melanoma and basal cell carcinoma |
| Keratoacanthoma | From the pilosebaceous unit. Argued to be a variant of invasive squamous cell carcinoma | Triphasic: rapid growth in 6–8 weeks, stabilization, regression after 3–6 months. Dome with a central keratin-filled crater. Risks: age >40, sun, very fair skin, male, red tattoo ink, skin trauma including lasers, surgery and cryotherapy, human papillomavirus | Biopsy is the only reliable diagnosis. Excise or destroy — standard of care because of possible malignancy. 5 mm margins; Mohs for large, recurrent or cosmetically sensitive lesions. Intralesional methotrexate before excision to shrink it |
| Epidermoid cyst | Epithelium enclosed in the dermis filling with KERATIN. Not a sebaceous cyst, despite the name. M:F 2:1; face, scalp, neck, trunk | Firm, movable, round, with a central pore or punctum; expresses cream-colored pasty material with the odor of rancid cheese | Lab tests usually unnecessary. If inflamed, POSTPONE excision, settle it with intralesional triamcinolone, antibiotics if needed. Standard of care: remove the entire capsule when it is not inflamed; 1–3 cm cysts can be punched and emptied |
| Syringoma | Benign neoplasms of eccrine ducts. Appear at puberty; females > males | Multiple 1–2 mm skin-colored, pink or brown papules on the eyelids and upper cheeks | Usually clinical; biopsy if malignancy is a concern. Cosmesis only — drugs (oral isotretinoin) risk recurrence, procedures risk poor cosmetic results. Differential: milia, xanthelasma, basal cell carcinoma |
What these look like
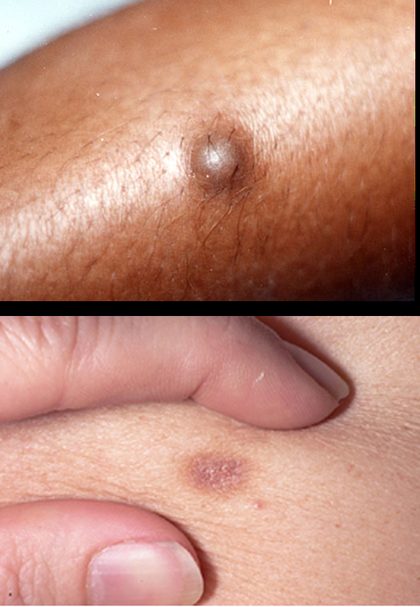
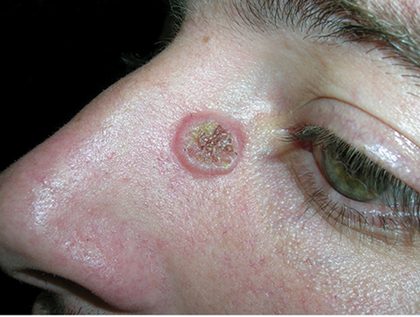
Also tested
- Epidermoid cyst testing. Laboratory testing is usually not required, because the diagnosis is clinical.
- Epidermoid cyst contents. It is often called a sebaceous cyst because the material looks like sebum, but the contents are keratin, not sebum.
- Squamous cell carcinoma risk factors. Besides sun exposure and immunosuppression: chronic wounds, scars or prior radiation fields; certain genetic diseases; and mucosal or genital disease.
- Keratoacanthoma risk factors. Age over forty, sun exposure, very fair skin that always burns and never tans, male sex, tattoos with red ink, skin trauma such as lasers, surgery or cryotherapy, and human papillomavirus infection.
- Dermatofibroma symptoms. Usually asymptomatic, sometimes with a history of insect bite; when symptomatic it may cause slight pruritus or pain, and it is described as the commonest painful skin tumor.
- Epidermoid cyst. Enclosed epithelium filled with keratin within the dermis; it is often called a sebaceous cyst because it appears to contain sebum, which makes that term a misnomer.
- Differential of dermatofibroma. Basal cell carcinoma, hypertrophic scar, cutaneous melanoma and keratoacanthoma; two of the four are malignancies.
7.6 · Objective a — The vascular lesions
Sort them first by congenital or acquired, and within the congenital group by whether the lesion involutes. That single question separates the two the professor tested himself.
| Lesion | Congenital / acquired | Mechanism | Course |
|---|---|---|---|
| Infantile hemangioma | Congenital | Proliferation of endothelial cells | Proliferates then INVOLUTES — 50% by age 5, 70% by 7, 90% by 9 |
| Nevus flammeus | Congenital | Dilation of dermal capillaries, NO proliferation | Never involutes; grows with the child, darkens and thickens |
| Nevus simplex | Congenital | More superficial variant of nevus flammeus | Fades within a year, or persists on the neck |
| Cherry angioma | Acquired | Capillary/venule proliferation | Increases with age; new ones keep coming |
| Telangiectasia | Acquired | Permanently dilated capillary <1 mm | Primary or secondary; associated with numerous diseases |
| Nevus araneus | Acquired | Dilation of preexisting vessels, no proliferation | Estrogen excess — resolves after delivery or stopping the pill; also cirrhosis |
| Pyogenic granuloma | Acquired | Vascular overgrowth after irritation, trauma or hormonal change | Grows fast, bleeds; may resolve over months to years |
What these look like
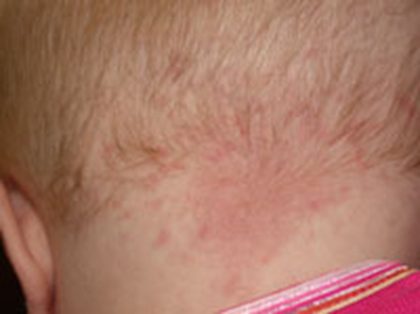
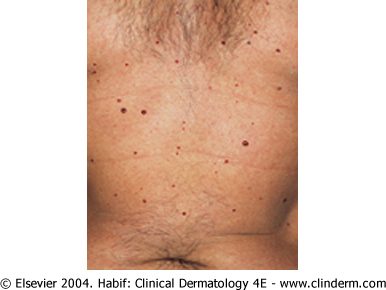
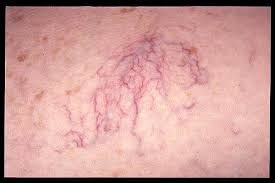
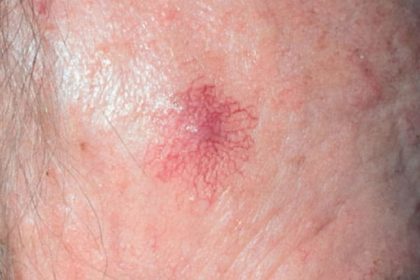
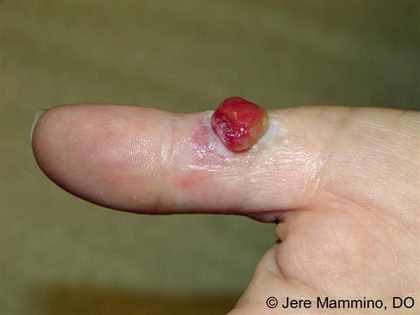
Infantile hemangioma is the most common tumor of infancy: preterm, female 3:1, Caucasian; head and neck 60%, trunk 25%, extremities 15%. Earliest sign is blanching, then fine telangiectasias, then a red or crimson macule. Superficial is commonest (dermal vessels, bright red, once “strawberry”); deep is least common (deep dermis and subcutis, pale, skin-colored, red or blue). Complications are compression of vital structures — vision, feeding, respiration, external auditory canal — plus extracutaneous lesions in liver, gastrointestinal tract, central nervous system and elsewhere.
Treatment indications: cosmetic, functional involvement, deep ulceration, infection. Otherwise serial observation. First line is a beta-blocker — oral propranolol or topical timolol, mechanism not well understood — and corticosteroids, topical, intralesional or oral. Pulsed dye laser reaches about 1.2 mm, so it is a superficial treatment. Refer to an experienced vascular anomalies specialist if the diagnosis is in question.
Pyogenic granuloma is misnamed — neither infectious nor granulomatous. Bright red exophytic papule with a moist surface and an epithelial collarette, average 6.5 mm, common on head, neck and fingers, and common in pregnancy. Differential includes melanoma and squamous cell carcinoma. Surgical excision has the lowest recurrence and the highest rate of scarring, and provides histopathology.
Also tested
- Cherry angiomas. Patients should be told that new lesions will likely develop and there is no way to prevent them; treatment is not necessary unless they bother the patient.
- History in spider angiomas. Cover pregnancies, hormone use, alcohol history, and medications that carry a risk of liver damage, because the lesion can be a marker of estrogen excess or liver disease.
- Nevus flammeus over time. Early, it is a flat blanchable patch, well-circumscribed, pink to red to purple, usually unilateral with fairly sharp midline cutoffs; later the vasculature dilates and it may become a raised, thickened plaque of deeper color.
- Natural course of a raised red plaque in an infant. Most involute on their own over several years: complete involution in fifty percent by age five, seventy percent by seven and ninety percent by nine, so serial observation is often all that is needed.
- History in spider angiomas. Take alcohol use, liver-damaging medication and hormone use, and ask about pregnancies too; spider angiomas track estrogen excess and cirrhosis or liver failure.
- Excision of a bleeding red papule. Surgical excision has the lowest recurrence rate and also provides histopathologic analysis, at the cost of the highest rate of scarring.
- Infantile hemangioma growth. Rapid proliferation is followed by slower involution, with rapid growth in the neonatal period and most growth in the first 4 to 6 months. The earliest sign is blanching, then fine telangiectasias, then a red macule.
- Nevus araneus. A central arteriole with radiating capillaries, caused by dilation of pre-existing vessels with no vascular proliferation. Estrogen excess may be the cause; ask about pregnancies, hormone use, alcohol and medications high-risk for liver damage.
- Pyogenic granuloma education. It is benign and often resolves over months to years; treatment is available if wanted, for cosmetic reasons or to prevent bleeding. If it recurs, early follow-up is appropriate because small lesions are easier to treat than large ones.
- Infantile hemangioma types. Superficial, mixed, and deep, classified by depth of vessel involvement; superficial is commonest, presenting as a bright red papule, plaque, or nodule, and the deep type is the least common.
- Cherry angioma. A benign capillary proliferation (capillary or venule proliferation), very common and increasing with age; treatment is unnecessary unless it bothers the patient, and new lesions will likely develop with no way to prevent them.
- Telangiectasia. A dilated capillary under 1 mm that blanches; these are acquired vascular lesions of permanently dilated capillaries, single or grouped with a central punctum, primary or secondary.
- Pyogenic granuloma. This acquired vascular lesion is a misnomer, being neither infectious nor granulomatous. It is a benign vascular tumor common in children, young adults, and pregnancy, arising in response to injury or hormonal factors, most often on the head, neck, and fingers.
- Differential of pyogenic granuloma. Cherry angioma, malignant melanoma and squamous cell carcinoma; two of these are malignancies.
- Flat blanchable pink-purple patch present since birth. No treatment is required; options are tinted waterproof makeup, or pulsed dye laser, which selectively destroys the superficial target vessels.
- Nevus simplex. Most common on the head and neck and more noticeable with crying; it appears as pink to erythematous blanchable macules or patches, single or multiple.
- Hemangioma complications. Hemangiomas may cause compression of vital structures, block vision, interfere with feeding or respiration, obstruct the external auditory canal, and occur at extracutaneous sites.
7.7 · Objectives a & b — Neurofibromatosis, and the remaining lesions
Neurofibromatosis, also von Recklinghausen disease, is a common neurocutaneous genetic disorder. NF1 — NF1 gene, chromosome 17. NF2 — NF2 gene, chromosome 22. Schwannomatosis (NF3) — SMARCB1 and LZTR1, chromosome 22. The four NF1 skin manifestations:
| Sign | Detail |
|---|---|
| Café au lait spots | Light tan to brown macules, >5 mm prepubertal, >15 mm postpubertal. Often the first manifestation; usually at birth or in the first year; grow in proportion with the child. Six or more are diagnostic — but the macules alone do not establish the diagnosis |
| Cutaneous neurofibromas | Benign nerve sheath tumors from peripheral nerves; sessile or pedunculated; begin at puberty and increase in number and size with age; a few to hundreds |
| Plexiform neurofibromas | Tumor in the tissue covering nerves; anywhere except brain and spinal cord; large, extensive, and may be locally invasive |
| Intertriginous freckling (Crowe’s sign) | Freckles <5 mm, smaller than café au lait spots, grouped, more prominent with sun. Axillary and inguinal — under the breasts is not a diagnostic site |
Management is surveillance: a cutaneous examination at every visit for new or progressing lesions. Education is to point patients at national and regional support groups.
| Lesion | What to know |
|---|---|
| Xanthelasma | Soft yellow cholesterol plaques — lipid-laden macrophages — on the medial eyelids. Screen for hyperlipidemia; may signify increased cardiac risk. Laser or excision; recurrence common |
| Lipoma | The most common soft tissue tumor. Benign overgrowth of subcutaneous fat; soft, painless, rubbery, usually <5 cm. Observe if asymptomatic; excise if deforming or the diagnosis is uncertain. Differential: epidermal cyst, dermatofibroma, abscess |
| Digital mucous cyst | A pseudo-cyst — no cellular lining. Mucin extruded from a joint space compacts the dermal cells into something that only mimics a capsule. Females > males, associated with osteoarthritis, over the distal interphalangeal joint; may groove the nail. Observe, or excise if symptomatic or causing nail dystrophy |
| Sebaceous hyperplasia | Sebocyte turnover slows with age, crowding cells and enlarging the gland. No known potential for malignant transformation; immunosuppression is high risk. Whitish-yellow soft papules 2–9 mm with central umbilication, on the face. Differential is basal cell carcinoma, and dermoscopy can distinguish them. No treatment needed — lesions recur and treatment risks scarring; light electrocautery if wanted |
What these look like
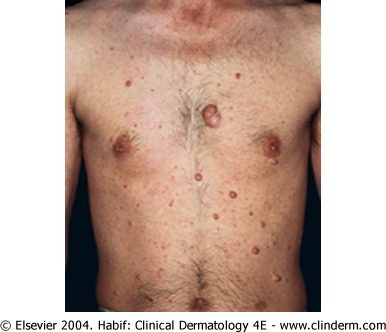
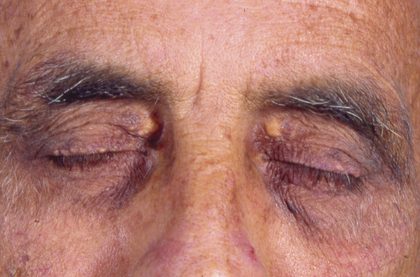
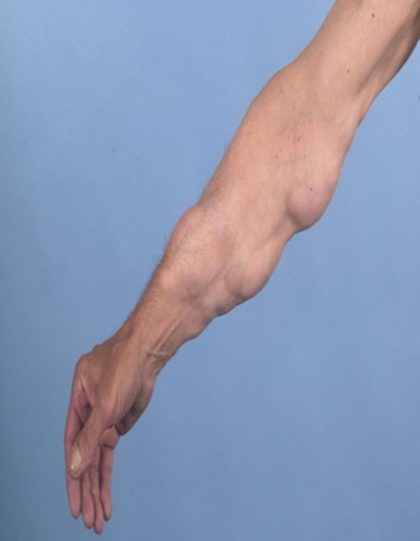
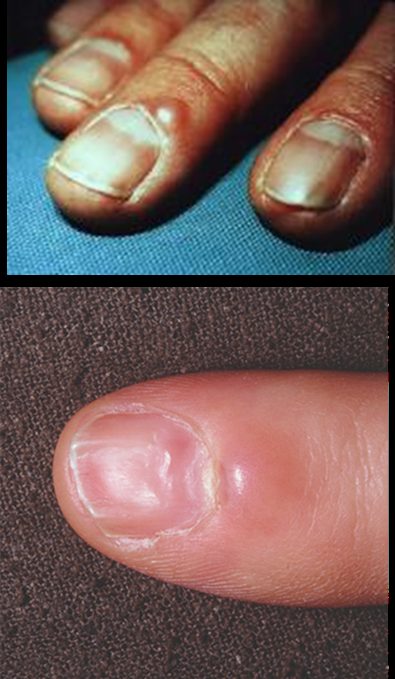
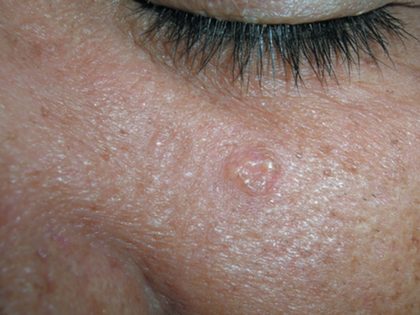
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Clavus (corn) — hard | Remove the pressure — padding, and stop wearing poorly fitting footwear. |
| Clavus (corn) — soft | As for hard corn — padding and footwear change, plus keeping the web space dry. |
| Callus | Padding and better-fitting footwear or gloves. |
| Keloid | Most important treatment is PREVENTION — advise high-risk patients to avoid cosmetic procedures such as ear piercing. No single modality is best; combination therapy has the best success rates. Occlusive silicone gel sheets 12–24 h/day for up to a year. Compression at 25 mmHg, 24 h/day, 6–12 months. Intralesional steroid (flattens; may cause tissue atrophy). Surgical removal — but 50–100% recurrence, often larger, so always follow with intralesional steroid. Radiation in the first two weeks after excision. Cryotherapy (flattens; causes hypopigmentation). Laser, best combined with intralesional steroid. Intralesional fluorouracil — inhibits fibroblast proliferation. |
| Hypertrophic scar | Intralesional injection — corticosteroid or fluorouracil. Compression therapy and silicone sheeting. Surgical excision — unlike keloid, hypertrophic scars improve with appropriate surgery. Pulsed dye laser — reduces erythema by reducing neovascularization. |
| Cutaneous horn | Depends entirely on the underlying etiology. An underlying malignancy frequently requires excision to the standard practice for that tumor type and location. Removing the horn alone treats nothing. |
| Acrochordon (skin tag) | Usually for cosmesis only. Scissor excision, cryotherapy, or electrodesiccation. Anesthesia is not necessary. |
| Pressure injury (pressure ulcer) | Best measure is PREVENTION: frequent skin assessment, nutrition assessment, moisture control and skin care (keep clean and dry, manage incontinence, barrier creams), reposition every two hours, manage pain, improve mobility, specialty mattresses. Management depends on stage. Refer to a wound care specialist. Control infection risk. Silicone and hydrocolloid dressings. Surgical referral for debridement — removes necrotic tissue, eschar and slough, which promote infection, delay granulation and impede healing — and for wound closure. |
| Pilonidal cyst | Keep the area clean and free of debris; shaving or laser hair therapy may help. Acute abscess → incision and drainage. Chronic disease → refer to a surgeon for excision. |
| Dermatofibroma | Often no treatment unless the diagnosis is questioned or symptoms warrant it. Small lesions: shave or punch biopsy — both diagnostic AND therapeutic. Larger lesions: may require surgical excision. |
| Keratoacanthoma | Surgical — standard of care is to excise or destroy the tumor, preferred because of possible malignancy. Elliptical excision with 5 mm margins. Mohs surgery for large or recurrent lesions, or lesions in areas with cosmetic or functional considerations. Intralesional methotrexate may be given before excision to reduce the size — it inhibits deoxyribonucleic acid synthesis in actively dividing cells. |
| Epidermoid (epidermal) cyst | Asymptomatic: no treatment necessary. If inflamed: POSTPONE excision for a few weeks, reduce inflammation with intralesional triamcinolone, add antibiotics if needed. Standard of care is surgical removal of the ENTIRE capsule, performed when the cyst is not inflamed. A small cyst (1–3 cm) can be treated with a punch incision and removal of the cystic contents. |
| Syringoma | For cosmesis only, and every option has a trade-off. Drugs (e.g. oral isotretinoin) — increased risk of recurrence. Removal procedures (curettage and electrodesiccation, laser therapy, cryotherapy, surgical excision) — possible poor cosmetic results. |
| Infantile hemangioma | No treatment may be needed — serial observation, since most involute. Indications to treat: cosmetic, functional involvement, deep ulceration, infection. First line: BETA-BLOCKERS — oral propranolol or topical timolol (mechanism not well understood). Also first line: corticosteroids — topical, intralesional or oral; slow growth and decrease size. Pulsed dye laser for superficial lesions (depth ~1.2 mm). Surgical excision. |
| Nevus flammeus (port-wine stain) | No treatment is required. Cosmetics — tinted waterproof makeup. Pulsed dye laser therapy — causes selective destruction of superficial target blood vessels, inducing intravascular coagulation; the vessel is later absorbed and replaced by collagen. |
| Nevus simplex (stork bite) | No treatment. Fades within one year, or may persist for life on the neck. |
| Cherry angioma | Not necessary unless it bothers the patient. Laser therapy for superficial lesions. Shave excision and electrocauterization for large lesions. |
| Telangiectasia | Treat the underlying cause where there is one. Cosmetic treatment where wanted follows the same options as other superficial vascular lesions — laser being the mainstay. |
| Nevus araneus (spider angioma) | No treatment may be needed — pregnancy- and pill-related lesions resolve on their own. Pulsed dye laser resolves most lesions. |
| Pyogenic granuloma | Spontaneous resolution may occur, but patients often opt for treatment for cosmesis or because of bleeding. Surgical excision — provides histopathologic analysis, lowest recurrence rate, highest rate of scarring. Other modalities: shave excision followed by curettage and electrodesiccation, laser, cryotherapy. |
| Neurofibromatosis type 1 | Surveillance. A cutaneous examination at every visit, assessing for new neurofibromas or progression of existing lesions. Plexiform neurofibromas may be locally invasive; clinical evaluation should be directed at determining the extent of involvement. |
| Xanthelasma | Laser or surgical excision. Recurrence is common. Treating the lipid disorder is the part that matters medically; removing the plaque is cosmetic. |
| Lipoma | Asymptomatic tumors can be observed. Cosmetically deforming enlarged masses, and uncertain diagnosis, can be treated surgically with excision. |
| Digital mucous cyst | Asymptomatic lesions may be observed. Symptomatic cysts, or those causing nail dystrophy, can be excised. |
| Sebaceous hyperplasia | Does not require treatment. Lesions tend to recur and treatment carries a risk of scarring. Light electrocautery can be used if treatment is wanted. |
Also tested
- Uncertain basal cell carcinoma. The next step is dermoscopy, with biopsy if concern remains.
- Xanthelasma. A collection of lipid-laden macrophages forming soft yellow cholesterol plaques, most commonly on the medial eyelids; it is asymptomatic.
- New lesion in a sun-exposed area. It is an opening to counsel on sunscreen, sun avoidance at peak hours and skin checks, as general skin-cancer education.
- Lipoma. Soft, painless, rubbery subcutaneous nodules, usually under five centimeters, that can occur anywhere on the body; asymptomatic unless adjoining structures are invaded.
- New benign lesion in a sun-exposed area. Use the opportunity for counseling on sunscreen and self-examination, including avoiding direct sun during peak hours and performing periodic skin self-examinations.
- Infantile hemangioma first-line treatment. Beta-blockers (propranolol by mouth or timolol topically) and corticosteroids (topical, intralesional or oral, to slow growth and shrink the lesion) are both named first line.
- Xanthelasma. Soft, flat yellow plaques near the inner canthus, prompting a lipid profile.
8 · Pigmented Skin Lesions
Instructional Objectives
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following pigmented skin lesions:
- Ephelides
- Lentigines
- Seborrheic keratoses
- Dermatosis papulosis nigrans
- Nevi
- Vitiligo
- Identify medical care strategies for pigmented skin lesions in the lecture topic list for the following populations.
- adult
- elderly
She teaches this whole topic to one repeating pattern. For lesion after lesion the management is the same three steps — diagnose clinically, observe, and biopsy if it changes in size, color or shape. Partway through she says it out loud: “I hope everyone’s still remembering the pattern here … it’s very similar, very much the same. There’s like two things that it’s not like that for.”
The two exceptions are the two that imitate melanoma, and both need tissue out with margins. Reed naevus (pigmented spindle cell) — confirm by biopsy, then “remove all the margins because of the risk of it turning” malignant; the deck says excision with negative margins. And the one she reaches immediately after, a “dome shape … sometimes it can resemble melanoma” managed by “wide excision, so not just removing part of the lesion … but the entire area surrounding it too”. She almost certainly named it, but the recording was not running. Segment 1 cuts off mid-sentence inside Reed — “because of the risk of it turning”, malignant never said — and segment 2 resumes already mid-description of the dome-shaped lesion. The name falls in the twelve-minute hole between them, which is why the word Spitz is in neither transcript. The identification is the deck's: slide 42 describes exactly this lesion, dome shaped, resembling melanoma, diagnosed by biopsy versus wide excision. If you remember one frame for this lecture, make it “watch them all, cut out the two that look like melanoma”.
The ephelides-versus-lentigines discriminator, in her words. On lentigines: “these do not go away as sun exposure gets less and less” — “that will be one way that you will be able to differentiate lentigines, sunspots, from ephelides, freckles.” Same fact as the cram sheet, but it is the one she chose to spell out.
A counseling point she framed as self-protection. On cryotherapy for a seborrheic keratosis: it can come back, so tell them beforehand — “otherwise they’ll be pretty upset at you”.
What the recording actually misses. Less than it first appears at the front, and more than it appears in the middle. It starts at roughly slide 3 or 4 of 47, so only the title and objectives slides are gone. It stops mid-sentence in the practice cases at the end. And between the two segments there is a twelve-minute hole — 13:44:43 to 13:56:40 — which is where the second exception above was named. If a topic below carries no emphasis note, that is not evidence she passed over it. Everything on the slides is covered in the sections that follow regardless.
8.1 · Objective a — Ephelides, lentigines and solar lentigo
| Ephelides (freckles) | Lentigo simplex | Solar lentigo | |
|---|---|---|---|
| Inheritance or cause | Autosomal dominant; MCR-1 variant | Increased melanocyte density; melanin macroglobules | Chronic ultraviolet exposure; basal melanocyte proliferation |
| Age | Young children, regress later in life | Bimodal — early childhood or later life | 90% of people by age 50 |
| Appearance | Light brown symmetric macules 3 to 5 mm | Uniformly black or brown, well circumscribed, under 5 mm | Irregular borders, coalescing at sunburn sites, under 1 mm to several centimeters |
| Sun behavior | Fade when exposure stops; darker in summer | Do not fade; occur on protected skin too | Do not fade; associated with actinic keratosis and skin cancers |
| Treatment | Sun protection, depigmenting agents, laser. Not cryotherapy — lesions too small | None needed; cryotherapy or quality-switched laser for cosmesis | None needed; retinoids, cryotherapy or laser for cosmesis |
What these look like
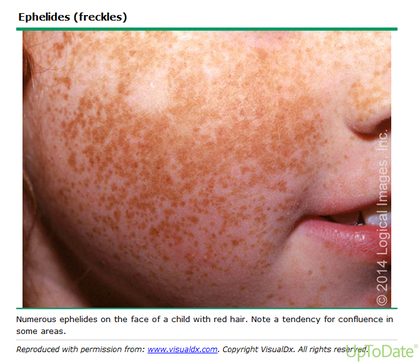
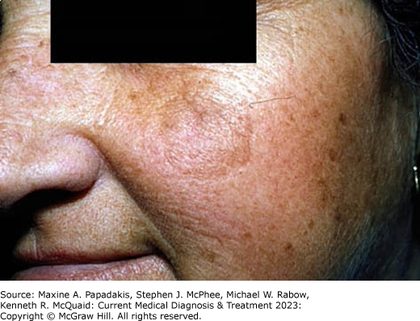
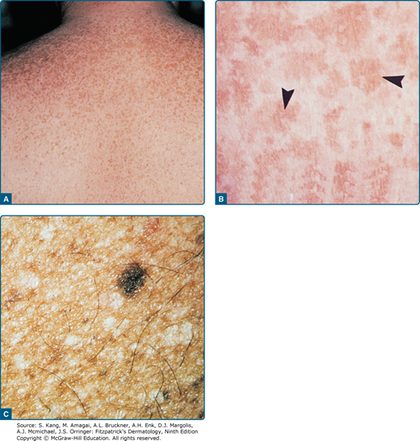
MCR-1 is the receptor for alpha-melanocyte-stimulating hormone, activating melanogenesis through cyclic adenosine monophosphate. Reduced pathway activity promotes pheomelanin, the yellow-red sulfur-containing pigment — which is why the freckling phenotype travels with red hair and fair skin.
Photochemotherapy (PUVA) lentigines relate to the total number of treatments, male sex, fair skin and older age, and appear on sun-protected sites such as buttocks and genitalia as well as exposed skin. A partial or generalized lentigo raises the question of an inherited disorder such as LAMB or myxoma syndrome.
Also tested
- Solar lentigo versus lentigo maligna. Solar lentigo has uniform pigmentation, whereas lentigo maligna is asymmetric with irregular border and color; dermoscopy is essential, and solar lentigo shows finger-like projections and a moth-eaten border.
- Solar lentigines. The lesions themselves are benign, but they mark cumulative sun damage that is also associated with actinic keratosis, squamous cell carcinoma, basal cell carcinoma and melanoma.
- Lentigines. They are well-circumscribed round to oval uniformly black or brown macules under 5 mm, on skin, conjunctiva and mucocutaneous surfaces, occurring on both sun-exposed and sun-protected areas.
- Lentigo maligna. Melanoma in situ that is asymmetric with irregular border and color and darker areas; dermoscopy is essential. A solar lentigo that has diverged from its uniform neighbors requires that evaluation.
- Biopsy of a pigmented facial macule. Atypical or uncertain morphology on dermoscopy is the stated indication for biopsy; an asymmetric macule with an irregular border and two darker areas is biopsied to exclude lentigo maligna.
- Solar lentigo risk factors. They are older age, sun damage, a history of ephelides, tanning, and birth control use. Solar lentigines are common: 90% of people have them by the age of fifty.
- Numerous solar lentigines. Advise daily broad-spectrum sunscreen of SPF 30 or higher, with an annual full-body skin examination. Dermoscopic surveillance is added for atypical lesions.
- Asymptomatic, unchanged flat brown patches on the backs of the hands. No treatment is necessary; cosmetic removal by cryotherapy or quality-switched laser is offered only if the patient wishes. Treatment is elective, not indicated.
- Forms of lentigines. Lentigo simplex, acral lentigo, agminated lentigo and generalized lentigo; they follow a bimodal age distribution.
- Ephelides. Inherited autosomal dominant, most commonly in fair-skinned people with blonde or red hair and possibly Celtic ancestry. Males and females are equally affected.
- Solar lentigines over time. They can progress into lichenoid keratoses. They may also enlarge, darken, stay stable or regress.
- Solar lentigines. Well-defined with irregular borders, coalescing at sites of severe sunburn, from under 1 mm to several centimeters, light to dark brown. Over time they enlarge, darken, stay stable, regress, or progress into lichenoid keratoses.
- Ephelides. They are small light brown symmetric macules 3 to 5 mm across, with lentigines as the main differential; they are asymptomatic and the diagnosis is clinical.
- Solar lentigines. Arise from basal melanocyte proliferation with more melanin production. They are strongly associated with older age (about 90 percent by age 50), sun damage, tanning, a history of ephelides, and birth control use.
- Agminated lentigines. A grouping of small light brown macules, one of the named lentigo types.
8.2 · Objective a — Seborrheic keratosis and dermatosis papulosa nigrans
| Seborrheic keratosis | Dermatosis papulosa nigrans | |
|---|---|---|
| Appearance | Beige to black papules and plaques 2 to 20 mm, velvety or warty, look stuck on | Smooth firm black or dark brown papules 1 to 5 mm — identical to small seborrheic keratoses |
| Site and group | Older adults, anywhere | Face and neck; African Americans, dark-skinned Asians, Polynesians; females more than males |
| Origin | Benign epidermal proliferation | Genetic; a developmental defect of the hair follicle |
| Management | Supportive; cryotherapy if itchy or inflamed, though it recurs | Best left untreated; excision, curettage or laser. Avoid cryotherapy — post-inflammatory hyperpigmentation |
What these look like
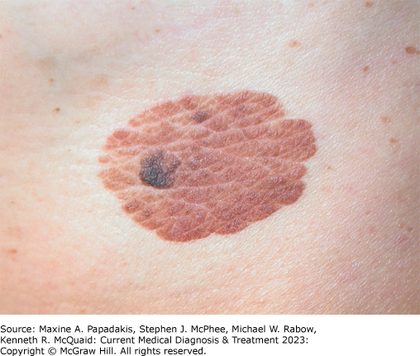
Seborrheic keratoses are easily mistaken for neoplasms, which is exactly why they matter in an older adult presenting with a new dark growth.
Also tested
- Seborrheic keratosis features. Dermoscopy shows comedone-like openings, with a stuck-on appearance clinically. Solar lentigo shows finger-like projections and a moth-eaten border instead.
- Biopsy in dermatosis papulosa nigrans. Biopsy is indicated when the diagnosis is uncertain; the diagnosis is otherwise clinical.
- Dermatosis papulosa nigrans counseling. The lesions are benign and best left untreated, with removal available for cosmetic reasons. Options are excision, curettage or laser, avoiding cryotherapy.
- Cryotherapy in dermatosis papulosa nigrans. Cryotherapy is avoided in this condition because of post-inflammatory hyperpigmentation. Excision, curettage or laser can be used where treatment is wanted.
- Multiple dark warty growths in older adults. They are benign and common in older adults, and the diagnosis is clinical without any need for biopsy. Cryotherapy helps if a lesion becomes itchy or inflamed, though it may recur.
- Symptomatic seborrheic keratosis. An itchy, inflamed lesion can be treated with cryotherapy, though the lesion may recur afterwards; asymptomatic lesions need no treatment at all.
- Seborrheic keratoses. Benign beige to brown to black papules and plaques 2 to 20 mm across, velvety or warty, looking stuck onto the skin, common in older adults. They are easily mistaken for neoplasms.
- Seborrheic keratosis diagnosis and management. They are benign, diagnosed clinically, and management is supportive. They are common in older adults and easily mistaken for neoplasms.
8.3 · Objective a — Vitiligo
An autoimmune disease causing depigmentation through T-cell mediated destruction of melanocytes. It can begin at any age but usually starts before the thirties — half before twenty, a third before twelve. Males and females are equally affected. Lesions are asymptomatic white non-scaly macules and patches with distinct margins that fluoresce under a Wood's lamp in a dark room.
| Non-segmental | Segmental | |
|---|---|---|
| Distribution | Well defined, symmetrical; prefers face (periorificial), genitals, acral areas | Unilateral, does not cross the midline, block-like patterns |
| Course | Progressive | Unpredictable cycles of flare and stabilization |
What these look like
| Extent | Treatment |
|---|---|
| Under 5% body surface | Topical steroid (cheap, effective; watch skin atrophy and intraocular pressure) or topical calcineurin inhibitor — tacrolimus, pimecrolimus — for face, neck, intertriginous areas and children (increased cancer risk), combined with phototherapy |
| Over 5% body surface | Phototherapy first line: narrow band ultraviolet B, preferred over PUVA because PUVA raises skin cancer risk. Combination with topical therapy is ideal |
| Highly stable disease only | Surgical tissue or cellular grafting |
Investigations: Wood's lamp in a dark room, and a complete blood count and antinuclear antibody for the other autoimmune diseases associated with it.
Also tested
- Segmental versus non-segmental vitiligo. Distinguishing them matters because the two differ in their diagnostic tools and in their treatment. Segmental disease is unilateral, does not cross the midline, and follows block-like patterns.
- Psychosocial impact of vitiligo. The psychological and social impact is real, and psychological intervention is part of management. Low self-esteem and poor body image are named explicitly.
- Vitiligo treatment. Phototherapy with narrow band ultraviolet B, ideally combined with topical therapy, is preferred over PUVA, which carries adverse effects including increased skin cancer risk.
- Vitiligo above five percent of body surface. Narrow-band ultraviolet B phototherapy is first line, ideally combined with topical therapy.
- Non-pharmacologic vitiligo management. Psychological intervention, cosmetic therapies and non-traditional approaches; the psychological and social impact is emphasized.
- Surgery for vitiligo. Tissue or cellular grafting is an option, since surgery is reserved for highly stable disease.
- First-line vitiligo treatment. Topical therapy suits under five percent involvement, ideally combined with phototherapy; calcineurin inhibitors are useful where steroids cannot be applied, such as face and neck.
8.4 · Objective a — The melanocytic naevi
Melanocytic naevi divide by cell of origin: acquired naevi from junctional melanocytes, congenital naevi from neural-crest derived precursors migrating along neurovascular bundles. Dysplastic naevi are the group showing atypical architectural and cytologic features.
| Naevus | Appearance and who | What matters |
|---|---|---|
| Congenital melanocytic | Flat brown patch or plaque at birth, sometimes pebbly or verrucous; trunk and extremities | The larger the lesion the higher the melanoma risk. Head, neck or posterior midline → magnetic resonance imaging for neurocutaneous melanosis |
| Naevus spilus | Tan café-au-lait-like patch with scattered darker macules; trunk and extremities | Rarely progresses to melanoma. Observation and sun protection. Vascular, central nervous system and connective tissue anomalies can accompany it |
| Common acquired (mole) | Under 6 mm, homogenous, round to oval, sharply demarcated; peaks in the thirties then declines | Very dark brown or black on light skin is suspicious. Melanoma risk rises with the number |
| Blue | Deeply pigmented dermal spindle or epithelioid melanocytes; women more than men, twenties; dorsal hands and feet, scalp, buttocks, sacrum | Common blue under 1 cm from adolescence; cellular blue over 1 cm before forty. Small lesions clinical, larger by biopsy |
| Pigmented spindle cell (Reed) | Jet-black sharply circumscribed papule under 7 mm; thirties, females, thigh | Benign, but confirm by biopsy and excise with negative margins |
| Spitz | Solitary pink or red hairless firm dome-shaped lesion; growth phase then stable; spares palms, soles, mucosae | Sometimes resembles melanoma — biopsy or wide excision. Multiple lesions can indicate a familial cancer syndrome |
| Dysplastic | At least 5 mm, irregular indistinct borders, variable tan to brown, smooth or pebbly; sun-exposed skin | Commonest in Caucasians with a family history. Over 100 by adolescence defines the syndrome. May progress to melanoma |
What these look like
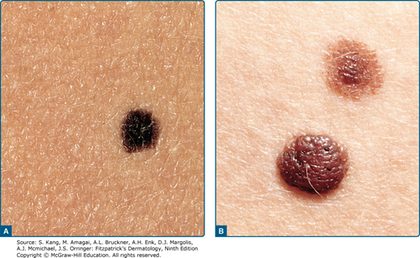
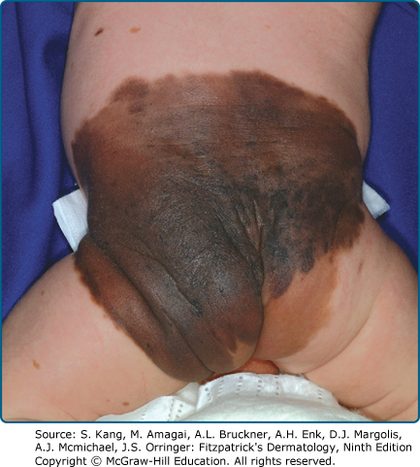
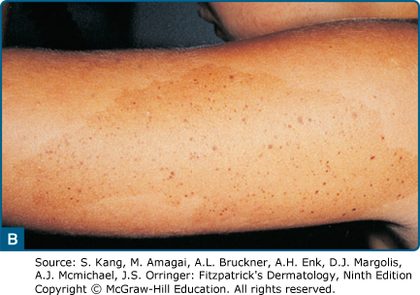
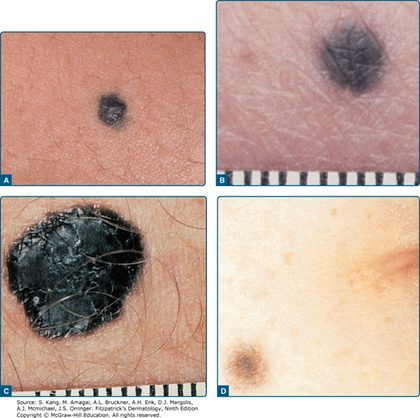
Also tested
- Macule. It is a flat lesion less than one centimeter, without elevation or depression; a patch is the same lesion larger than one centimeter.
- Purulent wound testing. Order bacterial culture and sensitivity: the culture names the organism and the sensitivity directs the antibiotic.
- Bulla. A fluid-filled lesion greater than one centimeter is called a bulla; a vesicle is the same lesion up to one centimeter.
- Common acquired melanocytic nevi. They are usually under 6 mm, homogeneous in surface and color, round to oval with sharp demarcation. A very dark brown or black lesion on a light-skinned individual is suspicious and warrants evaluation.
- Purpura. Non-blanching blood deposits of 4 mm or more are purpura, a medical emergency until proven otherwise; with fever in a child it demands immediate evaluation.
- Potassium hydroxide wet preparation. It detects fungal elements in skin, hair or nail samples and is the appropriate bedside confirmation before treating a suspected dermatophyte infection.
- Poorly demarcated. A poorly demarcated lesion has an irregular or blotchy appearance without well-defined borders, in contrast to a well-demarcated lesion, which has clearly defined borders.
- Dermatoscope. It is used for magnified examination of a lesion's surface and pigment pattern, and is the first-line tool for evaluating a pigmented lesion.
- Plaque versus patch. A plaque is elevated and plateau-like, while a patch is flat with no elevation; both exceed one centimeter, so elevation is the discriminator.
- Wheal. A wheal is a firm edematous plaque produced by infiltration of fluid into the dermis. The fluid is in the tissue rather than in a cavity, which separates it from a vesicle.
- Describing a skin finding. Six features translate a dermatological finding into words: primary morphology, secondary morphology, demarcation, color, size and distribution. Including all six lets another provider picture the lesion without seeing it.
- Lichenification. It is thickening and hardening of the skin, and it develops from chronic rubbing or scratching.
- Transillumination. This bedside technique shows whether a soft subcutaneous nodule is fluid-filled: a fluid-filled lesion glows when a light is placed against it.
- Common acquired melanocytic naevi natural history. They develop slowly after birth, enlarge symmetrically, stabilize and regress, peaking in number in the thirties and then declining. Melanoma risk rises with the number of lesions.
- Common acquired melanocytic naevi risk factors. They include ultraviolet radiation exposure, male sex, and a genetic component, with more lesions in light skin tones that sunburn. The number of lesions peaks in the thirties.
- Naevus spilus. It is thought to arise from a somatic mutation and appears at birth or in the first years of life. It is a variant of congenital naevus.
- Congenital melanocytic naevi. Neurofibromatosis type I is a named associated risk factor. Congenital naevi also carry a high risk of developing into melanoma.
- Large congenital naevus with neurological symptoms. Seizures and vomiting with a large naevus over the head and neck indicate neurocutaneous melanosis, and the prognosis is poor once neurological symptoms appear. Symptoms usually appear within the first few years of life.
- Large congenital naevus workup. Head, neck or posterior midline lesions raise neurocutaneous melanosis, so magnetic resonance imaging of the brain, with or without total spine, is required, matched to where the naevus sits.
- Numerous dysplastic naevi counseling. Between visits, use sun protection and report any lesion that changes or is newly developing. Management is observation, biopsy of changing lesions and excision where melanoma is a concern.
- Removing a melanocytic naevus. Removal for symptomatic or cosmetic reasons is reasonable, alongside sun protection counseling. The diagnosis is clinical and management is otherwise observation.
- Neurocutaneous melanosis. A related condition in patients with naevi on the head, neck or posterior midline, causing seizures, hydrocephalus, neurological deficits and vomiting; prognosis is poor once neurological symptoms appear, usually in the first few years of life.
- Pigmented spindle cell naevus (Reed naevus). A sharply circumscribed darkly pigmented papule usually under 7 mm, jet-black with shades of blue, gray or brown, on the extremities and mainly the thigh. Commonest in the thirties, females more than males; benign.
- Melanoma risk and common acquired melanocytic naevi. Risk increases as the number of naevi increases. Naevus numbers peak in the thirties and then decline.
- Blue naevi location. Most commonly on the dorsal hands and feet, scalp, buttocks or sacral region. The lesions are blue, blue-gray or blue-black.
- Spitz naevus. A solitary asymptomatic pink or red hairless firm dome-shaped lesion on face, neck, trunk or extremities, sparing palms, soles and mucous membranes. It has a growth phase, fast or slow, followed by a stable period.
- Pigmented spindle cell naevus management. Confirmed by biopsy, with excision and negative margins as management. The lesion is benign despite its jet-black appearance.
- Common versus cellular blue naevi. Common blue naevi are deeply pigmented lesions under 1 cm arising in adolescence; cellular blue naevi are larger plaques or nodules over 1 cm arising before age forty. Both occur on dorsal hands and feet, scalp, buttocks or sacral region.
- Changing lesion in dysplastic naevi. Biopsy the lesion, since all changing or developing lesions are biopsied. Excision follows where there is concern for melanoma.
- Dysplastic naevi. They are common on sun-exposed skin surfaces. They are at least 5 mm with irregular indistinct borders and variable pigmentation.
- Cellular blue naevus diagnosis. Diagnosis is clinical for small lesions but by biopsy for larger ones. Observation follows, with biopsy or excision if changes are noted.
- Excisional biopsy. An excisional biopsy removes the whole lesion, taking all deep and wide margins, and always needs stitches to close the wound.
- Dysplastic nevus syndrome and melanoma. The higher the number of nevi, the higher the risk of melanoma; over one hundred nevi by adolescence defines the syndrome.
- Diagnosing a dysplastic melanocytic nevus. Biopsy establishes the diagnosis, because the lesion is diagnosed histologically.
- Management of nevus spilus. Observation with periodic clinical evaluation, plus sun protection counseling, because it rarely progresses to melanoma.
- Common acquired nevus color. It is skin colored, brown or pink, with a homogenous surface and color, whereas a dark brown or black nevus on light skin is suspicious; it is usually under 6 mm, round to oval, and sharply demarcated.
- Dysplastic melanocytic nevus. Diagnosis is by biopsy; management is observation, biopsy of all changing or developing lesions, excision where melanoma is a concern, and sun protection. Melanoma risk rises with the number of nevi present.
8.5 · Objective b — Care strategies in adults and the elderly
| Population | What changes |
|---|---|
| Adult | Naevus counts peak in the thirties, so this is when dysplastic naevus syndrome declares itself. Vitiligo usually begins before thirty and needs psychological support alongside therapy. Solar lentigines begin appearing and mark cumulative sun damage |
| Elderly | Seborrheic keratoses are common and are easily mistaken for neoplasms — the clinical diagnosis is what avoids unnecessary biopsy. Solar lentigines are near-universal by 70 in fair skin, and sit alongside actinic keratosis and skin cancers. Naevus counts fall, so a new pigmented lesion in an older patient deserves more suspicion, not less |
Across both groups the same three things carry: daily broad-spectrum sun protection, annual full-body skin examination, and biopsy of anything that is changing.
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Ephelides (freckles) | Sun protection, with proper patient education and counseling — this is the key. |
| Lentigines | Treatment is not necessary. Cosmetic removal if the patient prefers: cryotherapy or quality-switched laser. |
| Solar lentigo also Lecture 3 | Treatment is not necessary. Cosmetic removal: retinoids, cryotherapy, or quality-switched laser. |
| Seborrheic keratosis | Management is supportive. If itchy or inflamed: cryotherapy may help — however they do recur after treatment. |
| Dermatosis papulosa nigrans | Best left untreated. If treatment is wanted: excision, curettage or laser. AVOID CRYOTHERAPY — post-inflammatory hyperpigmentation. |
| Vitiligo | Under 5% body surface (with phototherapy): topical steroids (good efficacy, easy, cheap — watch skin atrophy and intraocular pressure) or topical calcineurin inhibitors — tacrolimus, pimecrolimus — safe and good for face, neck, intertriginous areas and children, but with increased cancer risk. Over 5% body surface: PHOTOTHERAPY is first line — narrowband ultraviolet B, preferred over PUVA (PUVA raises skin cancer risk). Combination of topical + phototherapy is ideal. Surgical (tissue and cellular grafting): only for highly stable disease. |
| Congenital melanocytic naevus | Depends on melanoma risk plus cosmetic and functional considerations. The goal is to remove as much as possible while preserving function and improving appearance. Observation versus surgical — ideally surgical, but if there is little skin for a graft site, observation may be the better option. Symptoms are another indication. |
| Naevus spilus | Observation with periodic clinical evaluation. |
| Common acquired melanocytic naevus (mole) | Observation. Remove for cosmetic reasons or symptomatic relief. |
| Blue naevus | Observation. Biopsy or excision if changes are noted. |
| Pigmented spindle cell naevus (Reed) | Excision with negative margins. |
| Spitz naevus | Excision. |
| Dysplastic melanocytic naevus | Observation. Biopsy on ALL changing or developing lesions. Excision where there is concern for melanoma. Sun protection. |
Also tested
- Treating freckles. Start with sun protection and counseling, then topical depigmenting agents, with intense pulsed light or laser if needed; the topical options are hydroquinone, retinoids, alpha-hydroxy acids and botanicals.
- Light or laser treatment of freckles. Patients should expect that lesions can relapse, so treatment is not necessarily permanent.
- Freckles management. Manage with sun protection, patient education and topical depigmenting agents; cryotherapy is not used because of the size of the lesions. Laser or intense pulsed light is preferred, but the lesions can relapse.
- Ephelides. Topical depigmenting agents named are hydroquinone, retinoids, alpha-hydroxy acids and botanicals, though sun protection and counseling remain the priority.
- Treating solar lentigines. Treatment is cosmetic; reducing skin cancer risk depends on sun protection and surveillance for other lesions. The lesions mark sun damage rather than causing the cancers associated with it.
- Very large congenital naevus. Counseling and support groups for families and patients with large naevi are appropriate support, named alongside the surgical and observational decision.
- Cryotherapy of seborrheic keratosis. Tell the patient beforehand that the lesion can come back after freezing, so she is not surprised or disappointed later.
- Removing seborrheic keratoses. Treatment is not necessary; removal is elective, for cosmetic or symptomatic reasons, using retinoids, cryotherapy or quality-switched laser.
- Congenital melanocytic naevus management. It depends on melanoma risk together with cosmetic and functional considerations, removing as much as possible while preserving function; observation may be better where there is little skin for a graft site.
- Very large congenital naevus. Point families to counseling and support groups; management balances melanoma risk, cosmetic outcome and preserved function. The goal is removing as much as possible while preserving function and improving appearance.
- Small congenital melanocytic nevus. Observation, since management balances melanoma risk with cosmetic and functional considerations; smaller lesions carry lower melanoma risk than larger ones.
- Cosmetic removal of solar lentigines. Retinoids, cryotherapy or quality-switched laser; treatment is not necessary as the lesions are benign.
9 · Pre-Malignant and Malignant Cutaneous Lesions
Instructional Objectives
- Compare and contrast the etiologies, epidemiology, risk factors, clinical manifestations, differential diagnosis, diagnostic testing (including ordering and interpretation), management (acute and chronic, including applicable rehabilitative and palliative care), appropriate referrals, patient education, and prognosis of the following pre-malignant and malignant cutaneous lesions:
- Precancerous lesions
- Actinic keratosis
- Skin cancer
- Squamous cell carcinoma
- Basal cell carcinoma
- Malignant melanoma
- Nail neoplastic conditions
- Kaposi’s sarcoma
- Cutaneous T-cell lymphoma
- Identify medical care strategies for pre-malignant and malignant cutaneous lesions in the lecture topic list for the following populations.
- adult
- elderly
Where the lecture audio and a slide disagree on a fact, THE SLIDE WINS. Every fact in this section and in the four Lecture 9 quizzes comes from the PowerPoint.
Three slides in this deck carry content that exists ONLY as a picture and extract as blank text: the level of invasion diagram, the Stages of Melanoma diagram, and the full TNM staging table. They are covered in 9.5 below and in the quizzes. If you revise from the slide text alone you will miss all three.
9.1 · Objective 1 — Describe before you name
The deck opens with a discipline rather than a disease: characterize the lesion systematically before assigning a diagnosis — primary lesion type, color, surface texture, border definition, size, distribution, palpability, ulceration, bleeding, induration, and temporal evolution.
| Examination priorities | Key history |
|---|---|
| Good lighting; dermoscopy when trained; total-body skin survey when indicated Palms, soles and nails Oral mucosa when Kaposi sarcoma is possible Regional lymph nodes for invasive or high-risk disease |
Onset and change; bleeding or non-healing; pain or pruritus Sunburns, occupational or recreational ultraviolet exposure, tanning-bed use Prior skin cancer; immunosuppression or transplant; human immunodeficiency virus risk Chronic scars, wounds or radiation sites Family history; the lesion the patient themselves has noticed |
Two of those are easy to skip and carry the most weight: the oral cavity, because a hard-palate lesion may be the presenting site of Kaposi sarcoma, and chronic scars or old radiation fields, because squamous cell carcinoma arises in them.
Also tested
- Describe before naming. Evaluate any premalignant or malignant lesion by first characterizing it: primary lesion type, color, surface texture, border definition, size, distribution, palpability, ulceration and bleeding, before assigning a diagnosis.
- Examining a suspected malignant skin lesion. Use good lighting, dermoscopy when trained, and a total-body skin survey when indicated; examine palms, soles and nails, the oral mucosa when Kaposi sarcoma is possible, and regional nodes for invasive or high-risk disease.
9.2 · Objective 1 — Actinic keratosis
Premalignant, and on a biologic continuum with keratinocyte carcinoma — not a distinct separate entity. Chronic ultraviolet injury produces dysplastic keratinocytic change across a field of sun-damaged skin, which is the idea the whole management section turns on.
Small 0.2 to 0.6 cm flesh-colored, pink or slightly hyperpigmented papules with a sandpaper texture; a lesion may be more apparent by touch than by sight. Sun-exposed face, scalp, ears, forearms and dorsal hands.
About 1 in 1,000 lesions per year progresses to squamous cell carcinoma — and cumulative field risk matters more than the risk from any individual lesion, which is difficult to predict for a given patient.
| Lesion-directed | Field-directed |
|---|---|
| Isolated or few lesions with clear borders Liquid nitrogen cryotherapy — the lesion crusts and disappears over 10 to 14 days |
Multiple lesions in one anatomic region (field cancerization) Topical fluorouracil · imiquimod · photodynamic therapy Fluorouracil plus calcipotriene — possible benefit |
What is NOT a typical actinic keratosis, and should trigger biopsy: bleeding, induration, ulceration or rapid enlargement. The most important distinction is early squamous cell carcinoma or carcinoma in situ, and the interpretation must separate the three, because invasion changes treatment, margins and risk substantially.
Treatment reduces lesion burden but the surrounding field remains at risk, so surveillance continues even after a successful course.
What these look like
Also tested
- Concerning actinic keratosis. Induration, tenderness and bleeding are the concerning features named for progression; biopsy the lesion to exclude invasive squamous cell carcinoma.
- Actinic keratosis versus early squamous cell carcinoma. Squamous cell carcinoma must be excluded when a lesion is thick, indurated, ulcerated, enlarging, painful, bleeding, persistent or recurrent.
- Thickened, indurated, bleeding actinic keratosis. Order a shave or punch biopsy, because induration and bleeding raise concern for squamous cell carcinoma and are not part of a typical actinic keratosis.
- Actinic keratosis pathogenesis. Actinic keratoses are intraepidermal keratinocytic dysplasias induced by cumulative ultraviolet B exposure; ultraviolet-induced TP53 mutation is the critical molecular event. They represent a field cancerization process.
- Field cancerization. Clinically normal skin around the lesions harbors subclinical mutations, so multiple or confluent lesions need field-directed therapy: 5-fluorouracil, imiquimod, tirbanibulin or diclofenac treat the field rather than single lesions.
- Transplant recipients. Immunosuppression raises the risk of actinic keratosis and skin cancer about sixty-fold, so they need aggressive photoprotection and biannual skin surveillance.
- Actinic keratosis biopsy. Morphology or behavior raising concern for squamous cell carcinoma, or persistence or recurrence after therapy, prompts biopsy. A shave or punch biopsy is used.
- Fate of an actinic keratosis. An individual lesion may persist, involute, recur, or progress, so individual lesion behavior is unpredictable.
- Actinic keratosis field therapy. Warn patients to expect erythema and crusting, and stress adherence to the full treatment duration. Patients who are not warned stop the course early.
- Actinic keratosis recurring after therapy. Persistence or recurrence after therapy is a biopsy trigger, so take a shave or punch biopsy. Recurrence plus induration is exactly what should prompt sampling.
- Squamous cell carcinoma. A firm nodule with heaped keratin or ulceration, on chronically sun-damaged skin.
9.3 · Objective 1 — Squamous cell carcinoma
The second most common skin cancer, following prolonged cumulative sun exposure — contrast basal cell carcinoma, which follows intense intermittent exposure. It may arise from an actinic keratosis.
Classically a small red, conical, hard nodule that may ulcerate; also a non-healing ulcer, a warty nodule, or an irregular pink plaque with hemorrhagic crust.
| Red flags | Rapid growth, pain, bleeding, ulceration, induration, fixation, palpable regional nodes |
| High-risk sites | Mucosal surfaces, lip, ear, scalp, temple, nose, genitalia |
| Tumor count | More than 10 means higher local recurrence and nodal metastasis |
| Immunosuppression | Common and often aggressive after transplant, with multiple tumors typically at about 5 years. Chronic lymphocytic leukemia and human immunodeficiency virus also raise risk and aggressiveness |
| Chemoprevention | Nicotinamide 500 mg orally twice daily reduces new squamous cell carcinoma by about 30% in high-risk patients |
Use time course, firmness or induration, ulceration, site, immune status and pathology to separate it from its differential — not morphology alone.
Management by stage. In situ without high-risk features: imiquimod, topical fluorouracil, or curettage and electrodesiccation. Invasive: surgical excision or Mohs. Advanced or metastatic: programmed death 1 blockade; cetuximab.
Mohs indications — high-risk sites (lips, temples, ears, nose, genitalia); recurrent tumors; aggressive histology with perineural or perivascular invasion; lesions over 1 cm on the face or over 2 cm on trunk or extremities; immunosuppression; tumors within scars; genetic disease-associated tumors.
Follow-up is at least annual skin AND lymph-node examination. Referral is urgent for high-risk site, size, recurrence, aggressive histology, immunosuppression, neurologic symptoms or nodal disease. Metastatic rate for actinically induced disease: 3 to 7%.
What these look like
Also tested
- Squamous cell carcinoma pathology report. It should identify differentiation grade, depth or thickness, perineural or perivascular invasion, margin status, and aggressive subtype. Each feeds the decision about Mohs and about follow-up.
- Regional assessment in squamous cell carcinoma. Alongside biopsy, palpate the draining lymph-node basins, considering imaging or nodal evaluation for high-risk tumors. The nodes are examined at diagnosis, not only at follow-up.
- Squamous cell carcinoma prevention in transplant recipients. Nicotinamide five hundred milligrams twice daily reduces new squamous cell carcinoma by about thirty percent in high-risk patients.
- Squamous cell carcinoma biopsy requirement. The sample must allow the pathologist to determine whether the disease is in situ or invasive, along with the histologic risk features. Sufficient depth makes that distinction possible.
9.4 · Objective 1 — Basal cell carcinoma
The most common form of cancer. The histologic subtype determines behavior and dictates treatment — not the clinical appearance.
The deck gives the subtypes TWICE and the two lists are not the same. Clinical: superficial, nodular, pigmented, morpheaform. Histologic: superficial, nodular, micronodular, infiltrative. Morpheaform is a clinical description; micronodular and infiltrative are histologic ones. It is the histologic list that dictates treatment, which is why the biopsy report matters more than what the lesion looked like. Treatment planning asks whether the tumor is low-risk versus morpheaform, micronodular, infiltrative, recurrent, or in a tissue-sensitive site.
| Subtype | What you see |
|---|---|
| Nodular | Papule or nodule with central erosion, slow growth over years to 1–2 cm; pearly or translucent with telangiectasias accentuated by STRETCHING the skin |
| Pigmented | Stippled or focal pigmentation that may mimic melanocytic disease; the pearly border and slow growth discriminate |
| Superficial | Reddish, shiny, scaly thin papules or plaques on back or chest; may have a thready pearly border and spotty edge pigmentation |
| Morpheaform / sclerosing | Scar-like or ivory-white, with clinically subtle extension beyond the visible pink segment — higher risk of subclinical spread |
Warning patterns: a pearly papule, an erythematous patch larger than 6 mm, or a non-healing ulcer — commonly on face, trunk or lower legs.
Numbers worth holding. A second basal cell carcinoma develops in up to 50% of patients, so at least annual full-skin examination is mandatory. Nicotinamide 500 mg twice daily reduces development by about 20% — note that is the 20%, against 30% for squamous cell carcinoma. Excision recurrence 5% or less; Mohs cure about 98%.
Selected superficial disease may be treated topically: imiquimod five nights weekly for 6 to 10 weeks, or fluorouracil twice daily for up to 12 weeks, with clinical clearance confirmed afterwards. Advanced or metastatic disease: hedgehog pathway inhibitors — vismodegib or sonidegib.
Prognosis is usually slow-growing and highly curable when treated early; the morbidity comes from local destruction, recurrence, delayed diagnosis and anatomically complex sites rather than from spread.
What these look like
She told you how far into the staging table to go, and it is not far. On the T, N and M grid: “I want you to kind of know this … but I don’t necessarily want you to memorize it. I feel like for this stage of where you’re at … it just might be too much.” And on the sub-classifications, the N1a and T1a-versus-T1b rows: “that’s why I didn’t put all that, you guys don’t need to know that. I just want you to know this exists.”
What she DOES want, in her words: that T is the tumor, N the nodes and M the metastases; and the five stages in plain terms — 0 confined to the epidermal region, I localized and very thin, II localized but thicker, III spread to lymph nodes, IV spread to other organs. “That’s the general of what I do want you to know.” The quizzes here ask exactly that and no more — what the letters denote and the anchor stages, never a row of the grid.
Two survival figures she gave out loud that are on NO slide. Under one millimeter Breslow, “your prognosis is good … over 95-ish percent survival”; with distant metastases, “about a 15 percent survival”. The deck says only that survival drops sharply with thickness and spread. No quiz question is built on these, because they are not on a slide and she stumbled over the first figure — but the contrast is the reason she gives for catching it early, so it is worth carrying.
On referral she was blunt. Anything deeper than one millimeter goes to a specialist, and “I am not treating family medicine melanoma. Neither should you. It’s too dangerous.”
Also tested
- Mohs surgery for basal cell carcinoma. Indicated for high-risk anatomic sites, recurrent tumors, aggressive histology, or where tissue sparing is needed. The goal is complete eradication with minimal cosmetic and functional deformity.
- Sampling basal cell carcinoma. A suspected lesion is sampled with a shave or punch biopsy to confirm the diagnosis. Pathology then determines the histologic subtype, which dictates treatment.
- Basal cell carcinoma in immunosuppression. It is more common and more likely to recur after non-Hodgkin lymphoma, solid-organ transplant, or allogeneic stem cell transplant.
- Imaging in basal cell carcinoma. Routine imaging is not needed in typical localized disease; it is reserved for advanced, deeply invasive or metastatic disease. That specialist-directed workup is the exception rather than the rule.
- Topical therapy for basal cell carcinoma. Patients must understand that local inflammation is expected, and that clearance has to be confirmed afterwards. Inflammation is not a reason to stop, and clearing visibly is not the same as being clear.
9.5 · Objective 1 — Malignant melanoma
The 4th most common cancer in the United States and the leading cause of death due to skin disease. Incidence doubled over the preceding 30 years, while mortality has fallen with earlier detection and immunotherapy. 2023 figures: about 97,610 new invasive melanomas, about 7,990 deaths, roughly two-thirds of deaths in men. Lifetime risk about 2% in white individuals and 0.1 to 0.5% in persons of color — lower, but not zero, which is why acral and nail sites still get checked.
| Subtype | Behavior |
|---|---|
| Superficial spreading (~2/3) | Intermittently sun-exposed skin; evolves radially before vertical growth |
| Lentigo maligna | Chronically sun-exposed skin of older adults; slow radial growth phase |
| Nodular | Rapidly growing; often amelanotic; may LACK the classic features — high-risk for exactly that reason |
| Acral lentiginous | Palms, soles and nail units |
ABCDE: Asymmetry · Border irregular, notched or poorly defined · Colour variegation — brown, red, white, black, blue within one lesion · Diameter greater than 6 mm, though smaller lesions can be melanoma · Evolution.
The next three items exist only as pictures in the deck. A note on naming: slide 50 labels these simply “Level I” to “Level V”. The word Clark does not appear anywhere in this deck — it is the conventional name for this system and you will meet it everywhere else, so it is used below, but do not go hunting your slides for it.
| Level of invasion (slide 50) | What it means |
|---|---|
| I | Confined to the epidermis |
| II | Into the papillary dermis |
| III | Filling the papillary dermis |
| IV | Into the reticular dermis |
| V | Into the subcutaneous tissue |
The level of invasion (Clark) is an anatomic LAYER; Breslow thickness is a MEASUREMENT — and Breslow is the dominant prognostic variable, which must be measured accurately at the initial biopsy. Ulceration and mitotic activity further modify stage-based prognosis.
| Stage (slide 53) | Meaning | TNM anchor (slide 54) |
|---|---|---|
| 0 | Confined to the epidermal region of skin | Tis, N0, M0 |
| I | Localized, only in skin and very thin | T1–T2a, N0, M0 |
| II | Localized, thicker than stage I | T2b–T4b, N0, M0 |
| III | Spread to lymph nodes | Any N≥N1, M0 |
| IV | Spread to other organs | Any T, any N, M1 |
In the staging table, T is primary tumor thickness, N is the number of tumor-involved regional lymph nodes, and M is the number of metastases at a distant site.
Sentinel lymph node biopsy is offered or discussed at 1.0 mm or greater Breslow thickness, or 0.8 mm or greater with additional histologic risk factors — ulceration, high mitotic rate, or lymphovascular invasion. It is a staging procedure and may not itself improve overall survival, which is the honest thing to tell a patient.
| Re-excision margin | Thickness |
|---|---|
| 0.5 to 1 cm | In situ |
| 1 cm | Less than 1 mm |
| 1 to 2 cm | More than 1 mm |
Refer to an expert center for melanoma deeper than 1 mm, or with lymph-node or other-site spread. Patients perform monthly self-examination using ABCDE and ugly-duckling principles, including scalp, back, palms, soles and nails.
What these look like
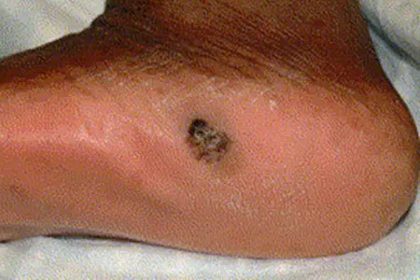
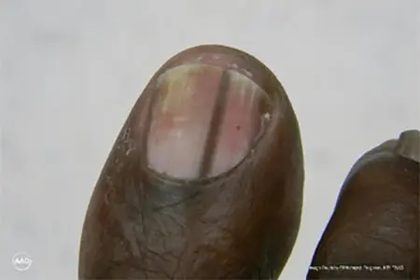
Also tested
- Stage IV melanoma. It is defined by any T, any N, with M1, meaning distant metastasis is present whatever the primary or nodal status; M1 alone determines it.
- Melanoma with nodal spread. Nodal spread, such as a positive sentinel node, is an explicit referral trigger to an expert center for coordinated dermatology and surgical oncology care. Nodal or other-site spread crosses the threshold regardless of thickness.
- Suspicious pigmented lesion. The initial diagnostic test is biopsy or excision to confirm the diagnosis. Tissue is required before staging decisions.
- Small suspicious pigmented lesions. An asymmetric lesion with an irregular border that is darkening should be biopsied or excised, because smaller lesions can still be melanoma; the 6 mm figure is a prompt, not a rule-out.
- Melanoma self-examination. Perform it monthly using the recognition mnemonic and ugly-duckling principles, including the scalp, back, palms, soles and nails, since acral and scalp sites are easy to miss.
- Malignant melanoma appearance. The lesion is asymmetric, irregularly bordered and unevenly colored; a lesion on the sole demands more suspicion.
- Re-excision margin for melanoma in situ. The margin is 0.5 to 1 cm; margins widen with Breslow thickness from there.
- Melanoma levels of invasion (Clark level). I is confined to the epidermis; II into the papillary dermis; III filling the papillary dermis; IV into the reticular dermis; V into the subcutaneous tissue. It is an anatomic layer, unlike Breslow thickness, a measurement.
- Melanoma re-excision margins by thickness. Definitive local margins are 0.5 to 1 cm in situ, 1 cm under 1 mm, and 1 to 2 cm over 1 mm; expert-center referral applies to melanoma deeper than 1 mm or with lymph node involvement.
- Melanoma stages 0 to II. Stage 0 is melanoma confined to the epidermal region of the skin; stage I is localized disease, only in skin and very thin; stage II is localized disease thicker than stage I. All three are still local.
- Melanoma subtype with delayed diagnosis. Acral lentiginous melanoma is frequently delayed in diagnosis, so early reporting is critical: patients report new pigment, widening bands or periungual pigment promptly.
- Melanoma deeper than 1 mm. A thickness over 1 mm calls for a 1 to 2 cm re-excision margin and referral to an expert center; the same threshold governs both.
- Melanoma re-excision margin. A melanoma under 1 mm Breslow thickness with no adverse features takes a 1 cm margin.
9.6 · Objective 1 — Kaposi sarcoma and cutaneous T-cell lymphoma
Kaposi sarcoma is caused by human herpesvirus 8 combined with a weakened immune system, arising in the cells lining blood and lymph vessels. Red or purple macules, plaques or nodules on skin or mucous membranes.
| Form | Population and course | First move |
|---|---|---|
| Classic | Older men; chronic; rarely fatal | Palliative local therapy — intralesional vincristine, vinblastine or bleomycin, or radiation |
| Endemic | Young Black men in equatorial Africa; often aggressive, can be rapidly fatal | As clinically indicated |
| Iatrogenic | With immunosuppressive therapy | Reduce immunosuppressive doses where feasible — coordinate with the transplant team first |
| Epidemic | Acquired immunodeficiency | Begin or optimize antiretroviral therapy — immune restoration is the cornerstone |
Two examination points carry disproportionate weight. Oral examination is essential when Kaposi sarcoma is suspected, because hard-palate lesions are common and may be the presenting site. And marked edema may occur with few or no visible skin lesions — so do not use edema severity to gauge disease burden.
Systemic first-line is liposomal doxorubicin and paclitaxel, and antiretroviral therapy plus chemotherapy is more effective than antiretroviral therapy alone in advanced disease.
Cutaneous T-cell lymphoma (mycosis fungoides) begins in the skin and may remain confined there for years or decades. Early: localized or generalized erythematous patches or scaly plaques, usually on the trunk, frequently larger than 5 cm, and it resembles psoriasis, eczema or tinea — which is why it is diagnosed late.
Two clues to hold: itch out of proportion to the apparent inflammatory activity, and follicular involvement with hair loss. Folliculotropism is what discriminates it from routine eczema or psoriasis.
The management philosophy is the exam point. Early aggressive treatment has not been proven to cure disease or prevent progression, and overly aggressive therapy may cause complications and premature death. A stage-directed, skin-first approach suits most early disease: topical corticosteroids, topical mechlorethamine, bexarotene gel, ultraviolet phototherapy.
What these look like
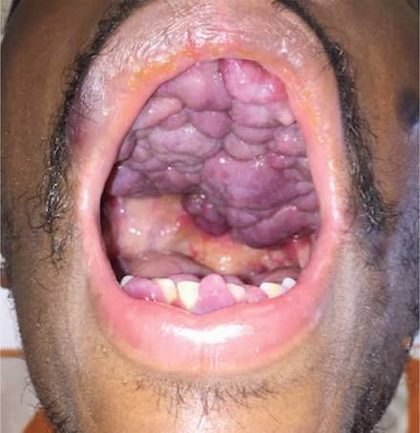
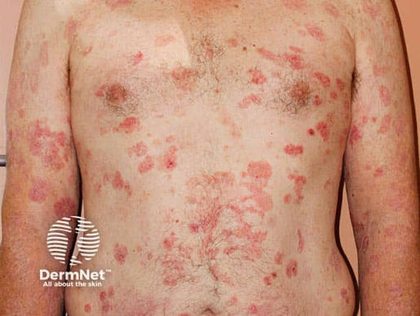
Also tested
- Confirming Kaposi sarcoma. Biopsy a representative lesion; human herpesvirus 8-associated findings on histology support the diagnosis.
- Kaposi sarcoma immune reconstitution inflammatory syndrome. It is especially dangerous in patients with visceral disease; endemic or visceral disease with this syndrome can be aggressive and rapidly fatal.
- Cutaneous T-cell lymphoma prognosis. Tumors, erythroderma and lymphadenopathy worsen prognosis; survival is not reduced in limited patch-stage disease.
- Mycosis fungoides. It may resemble psoriasis, eczema or tinea; the discriminators are chronicity, treatment resistance, and large or oddly distributed lesions. Early patches or scaly plaques are usually on the trunk, frequently greater than 5 cm.
- Cutaneous T-cell lymphoma versus psoriasis, eczema and tinea. Discriminators are chronicity, treatment resistance, large or oddly distributed patches, severe pruritus, follicular hair loss, tumors or erythroderma, nodes, and histology over time. No single one settles it, so longitudinal reassessment is stressed.
- Procedures in Kaposi sarcoma. Bronchoscopy is for suspected pulmonary disease, and endoscopy is driven by symptoms or management rather than done routinely in asymptomatic patients. A chest radiograph is used when pulmonary involvement is possible.
- Antiretroviral therapy in Kaposi sarcoma. Patients must be told the lesions may worsen early, as immune reconstitution inflammatory syndrome. Warning them beforehand stops early worsening being read as treatment failure.
- Biopsy site in suspected cutaneous T-cell lymphoma. Select an active, representative, untreated lesion, coordinating with dermatopathology. Treating a lesion first can obscure the histology being read.
- Establishing cutaneous T-cell lymphoma. Patients should be told the diagnosis may require repeated biopsies and the disease is usually chronic. Setting that expectation early matters, because the diagnosis is often slow to confirm.
- Regression of Kaposi sarcoma. Iatrogenic disease may regress when immunosuppression is reduced, which is why the transplant team is consulted before any reduction.
- Kaposi sarcoma versus lookalikes. It is told apart from bacillary angiomatosis, hemangioma and other violaceous lesions by immune status, distribution, oral lesions, edema, visceral symptoms and biopsy, not color alone.
- Immune context in suspected Kaposi sarcoma. Test for human immunodeficiency virus if status is unknown; if known, assess CD4 count, viral load, antiretroviral history and adherence. Knowing the status is not enough; the degree of immune suppression matters.
- Blood tests in advanced cutaneous T-cell lymphoma. They are complete blood count with differential, eosinophilia, circulating Sezary cells, T-cell gene-rearrangement testing and specialist flow cytometry. These belong to advanced disease rather than the initial skin diagnosis.
- Nondiagnostic biopsy in suspected cutaneous T-cell lymphoma. A single nondiagnostic biopsy does not exclude the disease; correlate clinically and reassess over time. Numerous biopsies may be needed.
- Enlarged nodes in cutaneous T-cell lymphoma. They may be benign dermatopathic change or lymphoma involvement, and require directed biopsy or imaging to distinguish. Enlargement alone does not establish spread.
- Kaposi sarcoma in a transplant recipient. Reduce immunosuppressive medication doses where clinically feasible, coordinating with the transplant team before making any change.
- Classic Kaposi sarcoma. The classic form affects older men, has a chronic indolent course, is rarely fatal, and is related to age-associated immune senescence.
9.7 · Objective 1 — Nail unit neoplasms
The deck calls diagnostic delay a recurring theme and a preventable harm in this module, and every item below is arranged around that.
| Tumor | Pattern |
|---|---|
| Nail unit melanoma | Rare acral melanoma, most often from the matrix. Not clearly ultraviolet-driven; any skin tone. Thumb and great toe. New or evolving longitudinal melanonychia in ONE digit, increasing width, irregular color/thickness/spacing, proximal widening or triangular shape, blurred borders, nail splitting, ulceration or subungual mass |
| Nail unit squamous cell carcinoma / Bowen | The most common malignant nail tumor. Chronic unilateral verrucous periungual papule or plaque, subungual hyperkeratosis, onycholysis, oozing, bleeding, nail-plate destruction, longitudinal erythronychia — often repeatedly labeled a wart, paronychia or fungal infection. Associations: high-risk human papillomavirus, immunosuppression, chronic inflammation or trauma, prior radiation, older age |
| Nail unit basal cell carcinoma | Exceptionally uncommon — consider it in a persistent ulcerated or pearly lesion of the nail fold or bed |
| Glomus tumor | Small red-blue subungual focus with severe paroxysmal pain, exquisite point tenderness and cold sensitivity; the nail may look nearly normal. The triad suggests it but does not replace imaging or specialist evaluation |
| Onychopapilloma / onychomatricoma | A single nail with longitudinal erythronychia or leukonychia, distal subungual hyperkeratosis, splinter hemorrhages or localized plate abnormality |
Hutchinson sign — periungual pigment extending onto the proximal nail fold — is highly concerning for nail unit melanoma and should prompt urgent expert evaluation regardless of other features. (Note this is a different sign of the same name from the zoster ophthalmicus one in Lecture 6.)
Amelanotic nail melanoma may be red, pink, eroded or mass-like with no dark band at all — the absence of pigment does NOT exclude melanoma. Consider biopsy for any unexplained, progressive single-nail lesion.
Before you inspect: remove the polish and examine every nail, the periungual skin, palms and soles, and the regional nodes.
Amputation is not automatic. Contemporary care is digit-sparing wide excision or Mohs with immunostaining where margins can be reliably assessed; amputation is reserved for deep, extensive or bone-involving disease. For nail unit squamous cell carcinoma, complete margin-controlled surgery is preferred and partial destructive treatment carries a higher recurrence risk.
What these look like
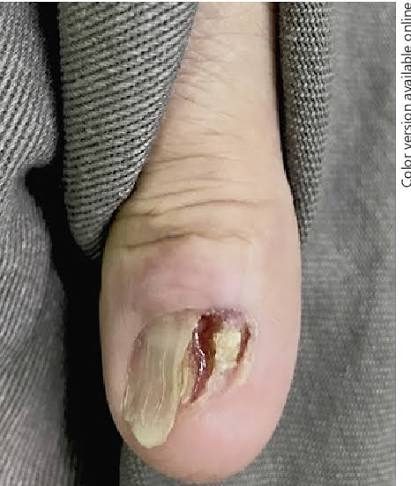
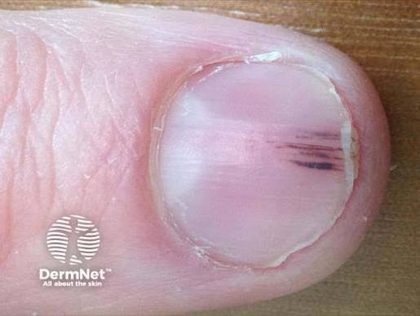
Also tested
- Biopsy of a suspicious nail lesion. It requires prompt referral to a dermatologist experienced in nail-unit biopsy, with the biopsy sampling the correct site.
9.8 · Objective 11 — Care strategies in adults and the elderly
| Population | What changes |
|---|---|
| Adult | Cumulative and intermittent ultraviolet exposure both accumulate through working life. Immunosuppression and transplant status dominate risk: squamous cell carcinoma is common and aggressive after transplant, typically multiple at about 5 years, and nicotinamide 500 mg twice daily is a real option. Melanoma self-examination is monthly and lifelong. Kaposi sarcoma in this group is usually epidemic or iatrogenic — treat the immune state first. |
| Elderly | Actinic keratosis burden and field cancerization rise with cumulative exposure — favor field-directed therapy. Lentigo maligna arises on chronically sun-exposed skin of older adults. Classic Kaposi sarcoma is a disease of older men and is managed palliatively rather than aggressively. In cutaneous T-cell lymphoma, the deck's warning that overly aggressive therapy may cause premature death weighs most heavily here. Basal cell carcinoma’s up-to-50% second-primary rate makes annual full-skin examination non-negotiable. |
Immunosuppression cuts across both and moves every answer the same way: more disease, more aggressive disease, a lower threshold for biopsy and for Mohs, and earlier referral.
First-line treatment
Every condition in this lecture, with what you reach for first and nothing else. Where the deck bands treatment by severity or site, those bands are kept, because that is the choice being tested. Second line, and the reasoning behind each, are in the comparison chart.
| Condition | First line |
|---|---|
| Actinic keratosis | Lesion-directed (isolated, clear borders): liquid nitrogen cryotherapy — crusts and disappears over 10–14 days. Field-directed (multiple lesions in one region — field cancerization): topical fluorouracil, imiquimod, photodynamic therapy; fluorouracil plus calcipotriene possibly. |
| Squamous cell carcinoma | In situ (no high-risk features): imiquimod, topical fluorouracil, or curettage and electrodesiccation. Invasive: surgical excision or Mohs. Advanced/metastatic: programmed death 1 blockade; cetuximab. Mohs indications: lips, temples, ears, nose, genitalia; recurrent; perineural or perivascular invasion; >1 cm on face or >2 cm on trunk/extremities; immunosuppression; tumors in scars; genetic disease. |
| Basal cell carcinoma — nodular | Superficial, selected: imiquimod 5 nights weekly for 6–10 weeks, or fluorouracil twice daily up to 12 weeks — confirm clearance afterwards. Surgery: curettage and electrodesiccation, excision, or Mohs by size, site and histologic risk. Excision recurrence ≤5%; Mohs cure ~98%. Advanced/metastatic: hedgehog inhibitors — vismodegib or sonidegib. |
| Basal cell carcinoma — superficial | The subtype most often suitable for topical therapy: imiquimod or fluorouracil, with clearance confirmed. Curettage and electrodesiccation also used. |
| Basal cell carcinoma — pigmented and morpheaform | Mohs for aggressive histology — morpheaform, micronodular or infiltrative — and for recurrent tumors or where tissue sparing matters. |
| Malignant melanoma | Re-excision margins: in situ 0.5–1 cm; <1 mm → 1 cm; >1 mm → 1–2 cm. Refer to an expert center for melanoma deeper than 1 mm or with nodal/other-site spread. |
| Nail unit melanoma | Coordinate dermatology, nail surgery and surgical oncology. Digit-sparing wide excision or Mohs with immunostaining for in situ and selected invasive tumors when margins can be reliably assessed. Amputation is NOT automatic — reserved for deep, extensive or bone-involving disease. Sentinel node discussion and systemic therapy follow melanoma stage and Breslow principles. |
| Nail unit squamous cell carcinoma / Bowen disease | Complete margin-controlled surgery preferred — Mohs or wide surgical excision. Partial or limited destructive treatment carries a higher recurrence risk. Distal phalanx or digital amputation reserved for bone invasion or disease that cannot otherwise be cleared. |
| Glomus tumor and the benign nail tumors | Diagnosis-specific surgical removal when symptoms, growth or diagnostic uncertainty warrant it. |
| Kaposi sarcoma | Epidemic (AIDS-associated) — FIRST PRIORITY: begin or optimize antiretroviral therapy. Immune restoration is the cornerstone. Classic/older adult: palliative local therapy — intralesional vincristine, vinblastine or bleomycin, or radiation. Iatrogenic: reduce immunosuppressive doses where feasible — coordinate with the transplant team first. Systemic first-line: liposomal doxorubicin and paclitaxel. Antiretroviral therapy plus chemotherapy beats antiretroviral therapy alone in advanced disease. |
| Cutaneous T-cell lymphoma (mycosis fungoides) | Stage-directed, skin-first. Early aggressive treatment has NOT been proven to cure or prevent progression, and may cause complications and premature death. Initial skin-directed: topical corticosteroids, topical mechlorethamine, bexarotene gel, ultraviolet phototherapy. Progressive: PUVA ± retinoids or interferon; methotrexate; extracorporeal photopheresis; systemic bexarotene; romidepsin or vorinostat; brentuximab or mogamulizumab; total-skin electron-beam treatment. |
Also tested
- Diagnosing squamous cell carcinoma. Use shave, punch or excisional biopsy sampling sufficient depth to separate in situ from invasive disease, because they carry different treatment, margins and risk.
- Single persistent nail abnormality. Avoid repeated empiric antifungal, antibiotic or wart treatment when the abnormality persists despite treatment. Repeating empiric therapy on a solitary persistent nail lesion is how diagnostic delay happens.
- Follow-up after squamous cell carcinoma. Examine skin and lymph nodes at least annually, with closer intervals if the patient is high-risk or immunosuppressed. The interval tightens rather than the examination changing.
- Photographing a concerning pigmented band. Do not let photographing it delay referral. Documentation is for tracking change, not for postponing the specialist.
- Neurologic symptoms after squamous cell carcinoma. New numbness and tingling in the distribution of the scar are an urgent referral trigger, since they raise concern for perineural invasion.
- Mohs micrographic surgery. Indicated for invasive squamous cell carcinoma on a high-risk site such as the temple, and for a lesion exceeding 1 cm on the face; either is a separate indication.
- Nail unit squamous cell carcinoma. Incomplete excision, immunosuppression, delayed diagnosis and bone invasion increase recurrence and functional morbidity. It is often curable with complete surgery.
- Early-stage cutaneous T-cell lymphoma. Early aggressive treatment has not been proven to cure the disease or prevent progression, and may itself cause harm. A stage-directed, skin-first approach suits most early disease.
- Mohs micrographic surgery for squamous cell carcinoma. Refer when the site is high-risk, the tumor is over one centimeter on the face, or histology is aggressive such as perineural invasion; each independently qualifies.
- Spread of actinically induced squamous cell carcinoma. An estimated 3 to 7%, raised substantially by high-risk sites or features, immunosuppression, multiple tumors, recurrence, or nodal involvement. The baseline is modest but modifiable.
10 · How this course is built
Clinical Medicine and Surgery I covers six areas — dermatology, ophthalmology, otorhinolaryngology (ear, nose and throat), cardiology, pulmonology, and hematology-oncology — emphasizing etiology, clinical manifestations, appropriate diagnostic evaluation, and management.
For every condition, the course compares and contrasts the same nine things. Worth learning as a checklist now, because it is the shape every later lecture and every vignette question takes:
| Etiology | Epidemiology | Risk factors |
| Clinical manifestations (signs and symptoms) | Diagnostic evaluation | Management |
| Patient education | Referrals / consults | Monitoring / follow-up |
Source: 1. svClinical Reasoning and Problem Solving.pptx (Professor Lauren M. Reynolds), Slides 1–30, and the PAJ 5500 syllabus instructional objectives. Further reading the lecture points to: Bates' Chapter 5 (clinical reasoning, diagnostic errors, documentation), Chapter 7 (health maintenance and screening), and Chapter 8 (evaluating clinical evidence).