1 · Disorders of the External and Middle Ear
Instructional Objectives
DISORDERS OF THE EARS, NOSE, THROAT AND NECK — External and Middle Ear Disorders
- Compare and contrast the etiologies, epidemiology, risk factors, clinical
manifestations, differential diagnosis, diagnostic testing (including ordering and
interpretation), management (acute and chronic, including applicable rehabilitative and
palliative care), appropriate referrals, patient education, and prognosis of the following
external and middle ear conditions:
- Acute otitis media
- Barotrauma
- Cerumen impaction
- Cholesteatoma
- Chronic otitis media
- Eustachian tube dysfunction
- Ear trauma
- Blunt and penetrating trauma
- Tympanic membrane perforation
- Hematoma of external ear
- Foreign body in the ear
- Otitis externa
- Otosclerosis
- Neoplasms: a. Benign · b. Malignant
- Identify medical care strategies for external and middle ear disorders in the lecture topic list for the following populations: 1. adolescent · 2. adult · 3. elderly
Two things he said out loud that are on no slide. The otitis media slide lists three bacteria and nothing else, which reads as though the disease were bacterial. It is not: “far and away the most common cause for otitis media is a viral infection”. And the three-organism sequence is no longer in order of prevalence — Moraxella catarrhalis has overtaken Haemophilus influenzae because of vaccination, which is why immunization status is worth asking. An unimmunized child puts H. influenzae back on the list.
His emphasis marker is repetition. He said “it's important, it's important, it's important to remember the three most common bacterial causes” — S. pneumoniae, H. influenzae, M. catarrhalis — and pointed out he had highlighted them on the slide himself. He signposted the exam nowhere else in the entire lecture, so his silence elsewhere means nothing.
Mastoiditis is filed here, though the syllabus lists it under Lecture 16. The only teaching on it in either deck is one line of this lecture’s slide 19, as a complication of acute otitis media. It sits where the content is.
The three columns to read down. Ear disease sorts on pain, the type of hearing loss and what the drum looks like. Those three are printed under every condition below and are the axes of the comparison chart.
1.1 · The external canal
Cerumen impaction Routine
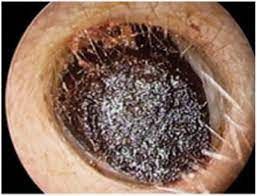
Gives itself away by: Self-induced by cleaning · wax filling the canal · conductive loss that clears on removal
- Presentation & who gets it
- Cerumen is a protective, thick, oily secretion of the outer third of the canal, and the canal is normally self-cleansing. Impaction is most commonly self-induced by cleaning attempts that push wax deeper. May be asymptomatic, or cause pruritus, fullness and conductive hearing loss.
- Pain / hearing loss / key finding
- No — pruritus, fullness · Conductive · Wax obstructing the canal
- Testing & cause
- Otoscopy: visible cerumen fully or partially obstructing the canal, wet and sticky, dry and flaky, or dark.
- First-line treatment
- Over-the-counter otic preparations to soften it. Irrigation or suction in clinic — irrigation uses body-temperature water and ONLY if the drum is intact. Curette removal suits soft wax and a compliant patient. If tympanostomy tubes or a perforation are present, removal must be done by ENT.
- Education & prognosis
- Do not insert anything into the canal. If cleaning is wanted, a washcloth over the index finger at the opening is the whole technique.
Slides 27–29
Otitis externa Routine
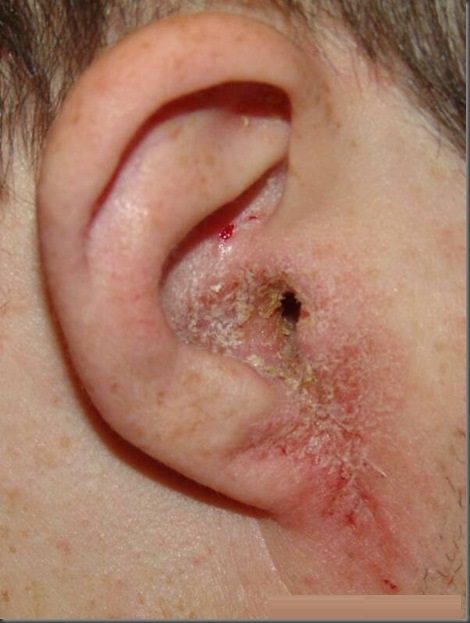
Gives itself away by: Pain on moving the tragus · swimmer · discharge from the canal
- Presentation & who gets it
- Inflammation and infection of the external canal, affecting 10% of people in their lifetime, all ages but commonest in children and early adolescence and in summer. Organisms: P. aeruginosa 38%, S. epidermidis 9%, S. aureus 8%; other bacteria and fungi possible. Risk factors: moisture and swimming, epithelial damage from aggressive cleaning, foreign bodies such as cotton swab fibers, occlusion by hearing aids or headphones, dermatitis of the auricle, radiation. Symptoms: otalgia exacerbated by touching or moving the auricle or tragus, otorrhea, pruritus, fullness, reduced hearing.
- Pain / hearing loss / key finding
- YES — worse on moving the tragus · Conductive if the canal closes · Canal erythematous and edematous
- Testing & cause
- Clinical diagnosis. Cultures reserved for severe, chronic or recurrent infection, immunosuppression, post-operative infection and treatment failure. Examination: tenderness to palpation, visible discharge, erythema and edema of the canal, periauricular and anterior cervical lymphadenopathy, thickened canal skin in chronic disease. Differential: otomycosis, suppurative otitis media, contact dermatitis, psoriasis and the rare carcinoma of the ear canal.
- First-line treatment
- Remove debris, then otic drops: antiseptic (boric acid, ichthammol, phenol, aluminum acetate, gentian violet, thymol, cresylate, alcohol), antibiotic (ofloxacin, ciprofloxacin, colistin, polymyxin B, neomycin, chloramphenicol, gentamicin, tobramycin) or acidifying (acetic acid). Combination drops with a steroid reduce pain and inflammation. An ear wick if the canal is stenosed.
- Education & prognosis
- Keep the ear dry, stop cleaning it, and use the drops for the full course — the pain settles well before the infection does.
Slides 54–59
Malignant otitis externa Emergent
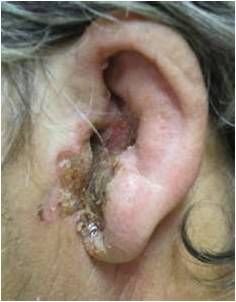
Gives itself away by: Elderly diabetic · pain out of proportion to the exam · facial nerve weakness
- Presentation & who gets it
- Also called necrotizing external otitis. A severe and potentially fatal infection of the bone and marrow spaces of the skull base and the soft tissue and cartilage of the temporal region. Elderly diabetics and immunocompromised patients are most at risk. Over 95% is spread of P. aeruginosa from an otitis externa. Symptoms: severe otalgia out of proportion to the physical findings, copious otorrhea, sometimes visible necrosis of the canal and evidence of facial nerve weakness.
- Pain / hearing loss / key finding
- SEVERE — out of proportion · Conductive · Canal necrosis, facial nerve weakness
- Testing & cause
- MRI or CT shows infection in the bony structures — that is what separates it from ordinary otitis externa.
- First-line treatment
- Antipseudomonal antibiotics — for example ciprofloxacin.
- Education & prognosis
- The complaint that matters is pain far worse than the ear looks, in a diabetic or immunocompromised patient. That combination is not treated as a routine swimmer's ear.
Slides 61
Otomycosis Routine
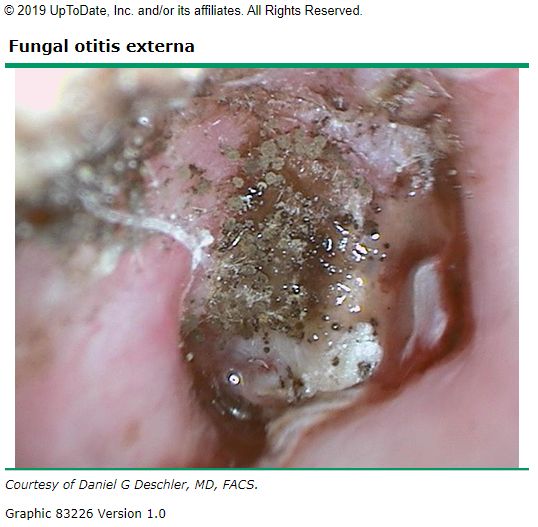
Gives itself away by: Itch more than pain · “wet newspaper” spores or white curd
- Presentation & who gets it
- Fungal infection of the external canal, 9% of ear canal infections and varying with climate. Commonest organisms Aspergillus niger and Candida. Pruritus, discomfort that is less painful than bacterial otitis externa, otorrhea, foreign body sensation.
- Pain / hearing loss / key finding
- Less than bacterial — itch dominates · Conductive if obstructing · “Wet newspaper” or white curd
- Testing & cause
- Otoscopy is the diagnosis. Aspergillus: visible fungal spores and filaments, described as “wet newspaper”. Candida: white, fluffy, curd-like material. Mild to moderate edema.
- First-line treatment
- Debris removal and topical antifungals.
- Education & prognosis
- It is treated by cleaning the canal as much as by the drops; the itch outlasting the pain is the clue that it is fungal.
Slides 62–63
Foreign body of the canal Urgent
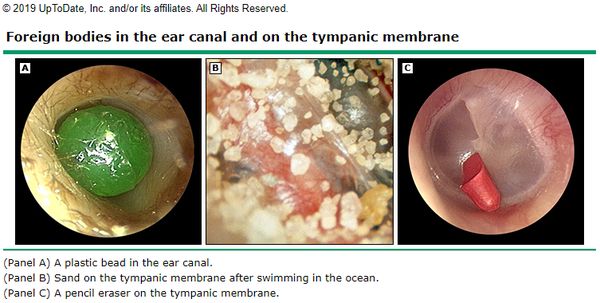
Gives itself away by: Child · anything that fits · do not push it deeper
- Presentation & who gets it
- Commoner in children but possible at any age, and can be anything that fits — beads, popcorn, crayons, insects, pencil erasers, paper. Otalgia varies with the shape of the object; bloody discharge if the canal lining is damaged; fullness and foreign body sensation.
- Pain / hearing loss / key finding
- Varies with the object · Conductive if obstructing · Object in the canal
- Testing & cause
- Otoscopy.
- First-line treatment
- CAUTION — do not push the object deeper. Firm objects come out with a loop or hook, soft ones with alligator forceps. Irrigation only if the drum is known to be intact, and with care: organic objects swell when wet and lodge harder. Insects are immobilized first by filling the canal with lidocaine — again only if the drum is intact. Refer to ENT for removal under microscopy where warranted.
- Education & prognosis
- Nothing goes into the ear at home to fetch it out; attempts are what turn a simple removal into a referral.
Slides 49–50
Also tested
- Canal versus middle ear disease. Pain on moving the tragus or pinna localizes disease to the canal, because middle ear infection sits behind an intact drum and is unaffected by moving the external ear.
- Retained ear canal foreign body. A porous object obstructs drainage and acts as a nidus for infection; foul unilateral discharge without pain or fever in a young child should prompt a search for something in the canal.
- Vertigo after ear trauma. A simple perforation does not cause vertigo, so vertigo calls for urgent assessment for inner ear injury (ossicular disruption with perilymphatic fistula, or labyrinthine injury) as well as for a perforation.
- Embedded earring back. It should be removed because infection is the main risk; removal treats the source and prevents spread into the auricular cartilage, where perichondritis can deform the ear.
- Otitis externa with a swollen canal. When edema stops drops at the outer canal, place an ear wick. It is an absorbent strip that draws medication along the canal by capillary action, restoring delivery without changing the drug.
- Sudden pain relief in otitis media. In acute otitis media pain comes from pus under pressure stretching the drum. When the drum perforates, the pressure is released, pain stops abruptly and discharge appears.
- Removing a smooth round object from the canal. Forceps push it deeper. Instead, pass a hook or curette beyond it under direct vision and draw it outward, since the risk is pushing the object against or through the drum.
- Swimmer's otitis externa. Treatment must cover Pseudomonas and Staphylococcus. Water raises canal pH and macerates skin, favoring Pseudomonas; topical fluoroquinolones cover both, whereas oral amoxicillin would be inadequate.
- Necrotizing external otitis. It is confirmed by imaging (computed tomography or magnetic resonance imaging) showing infection in the bony structures.
- Facial palsy in necrotising otitis externa. It means the infection has reached the skull base and facial nerve, marking advanced disease and a worse prognosis.
- Preventing otitis externa. Dry the ears after swimming and avoid cotton buds: retained water raises the pH and macerates the skin, while cotton buds strip the protective wax and abrade the epithelium.
- Otitis externa frequency. About ten percent of people experience otitis externa in their lifetime.
- Fungal external ear infection. Treatment involves clearing the debris and topical antifungals; cleaning matters as much as the drops.
- Home care in otitis externa. Keep the ear dry and finish the full course, because the pain settles well before the infection does.
- Foreign body in the ear canal. A smooth, round, manufactured blue object in the canal is a foreign body in the ear canal, because its color and shape are ones no biological material has.
- Ear canal infection with water exposure. Pain on moving the pinna localizes disease to the canal; water macerates canal skin and raises its pH so Pseudomonas and Staphylococcus overgrow. Treat with topical ciprofloxacin-dexamethasone: the fluoroquinolone covers those organisms and the steroid shrinks the edema.
- Otitis externa with spreading infection. Topical therapy is first line because disease is confined to canal skin; once infection extends into surrounding soft tissue, with cellulitis, fever and regional nodes, it is beyond a topical agent and the next step is to add systemic antibiotics.
- Small traumatic tympanic membrane perforation. With clean edges and no vertigo or facial nerve deficit, keep the ear dry and review: the drum heals spontaneously, and keeping water out stops bacteria reaching the middle ear through the hole.
- Persistent tympanic membrane perforation. Most close within weeks to a few months; one still open at eight months with persistent conductive loss is unlikely to heal spontaneously, so refer for consideration of tympanoplasty, which restores hearing and closes the route for water.
- Tragus. The small projection immediately in front of the ear canal opening, which is why pressing it hurts in canal infection.
- Clinical divisions of the ear. The ear is separated into three: external, middle and inner.
- Otitis externa with significant pain. Adding a corticosteroid to the antibiotic drops addresses the pain directly, because it reduces pain and inflammation.
1.2 · The auricle
Hematoma of the external ear Urgent
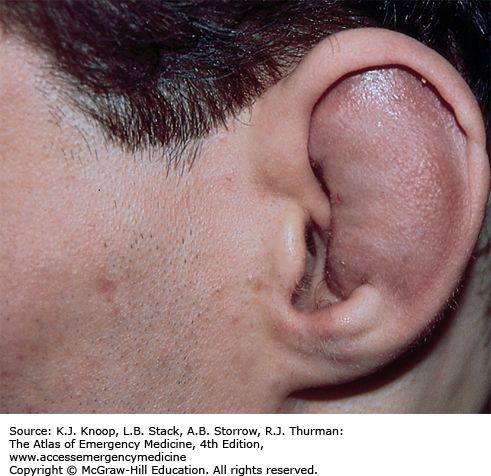
Gives itself away by: Blunt trauma · cartilaginous landmarks lost · drain early or cauliflower ear
- Presentation & who gets it
- Blood pooling in the sub-perichondrial space, usually after blunt trauma. The collection keeps oxygen and nutrients from the cartilage, which is what risks necrosis. May develop hours after the injury, so patients are re-checked at 12–24 hours. Examination: edema and ecchymosis of the auricle with loss of the cartilaginous landmarks.
- Pain / hearing loss / key finding
- YES · None · Auricle swollen, landmarks lost
- Testing & cause
- Clinical.
- First-line treatment
- Drain it — incision or large-needle aspiration — and do it early. After 7 days granulation tissue makes drainage much harder. Follow with irrigation and topical and/or systemic antibiotics. Ear splinting improves the cosmetic result and prevents re-accumulation: cotton bolsters, plaster molds, silicone putty, thermoplastic splints.
- Education & prognosis
- Early diagnosis and drainage is what prevents cauliflower ear. Come back at 12–24 hours even if it looks minor, because the hematoma can appear late.
Slides 39–42
Lacerations and avulsion Urgent
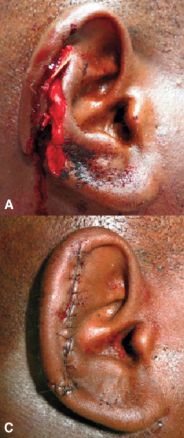
Gives itself away by: Blunt or sharp trauma to the auricle · prompt repair · pressure dressing after
- Presentation & who gets it
- Blunt or sharp trauma to the auricle. Prompt repair and infection prevention are critical. Simple lacerations close with sutures; complex ones and avulsions may need debridement first; tissue grafts if there is tissue loss. If avulsed tissue is recovered, reattachment is often successful.
- Pain / hearing loss / key finding
- YES · None · Visible wound of the auricle
- Testing & cause
- Clinical.
- First-line treatment
- Repair as above, then cover with a pressure dressing to prevent a hematoma forming under the repair.
- Education & prognosis
- Bring any avulsed tissue — reattachment often works.
Slides 43
Foreign body of the auricle Urgent
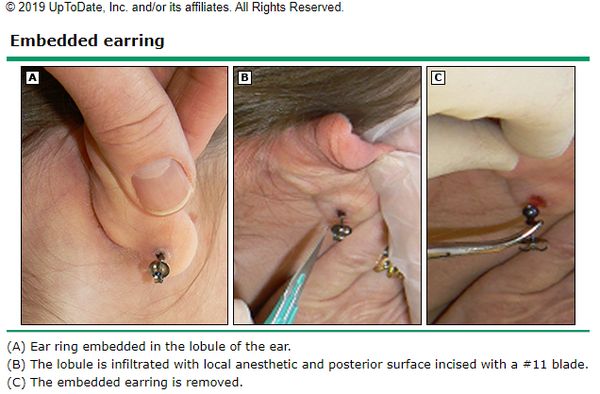
Gives itself away by: Embedded earring · girls and young adolescents · infection is the concern
- Presentation & who gets it
- Piercings becoming embedded in the earlobe or elsewhere on the auricle. Most common in girls and young adolescents with pierced ears. Pain, erythema and edema; may have purulent drainage from the piercing site. Examination: pain on palpation, and the foreign body may be palpable.
- Pain / hearing loss / key finding
- YES · None · Embedded piercing
- Testing & cause
- Clinical.
- First-line treatment
- Removal under local anesthetic; younger or non-compliant patients may need sedation.
- Education & prognosis
- Infection is the biggest concern, not the object itself.
Slides 51–52
Keloid of the ear Routine
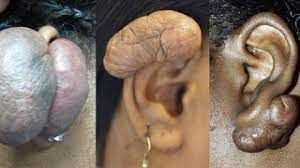
Gives itself away by: Hypertrophic scar after trauma — classically after piercing
- Presentation & who gets it
- Benign neoplasm of the ear: keloid and hypertrophic scars resulting from trauma.
- Pain / hearing loss / key finding
- No · None · Scar on the auricle
- Testing & cause
- Clinical.
- First-line treatment
- Avoid further trauma. Intralesional steroid injection, corticosteroid tape, excision. Radiation therapy in adults, NEVER in children. Follow closely for recurrence.
- Education & prognosis
- Recurrence is the rule rather than the exception, which is why follow-up is part of the treatment.
Slides 69–70
Also tested
- Suspected canal carcinoma. Otitis externa unresponsive to appropriate treatment, with bloody otorrhea and friable tissue, needs biopsy of the canal lesion, since only histology distinguishes malignancy from chronic inflammation.
- Diving barotrauma. Persistent vertigo and sensorineural loss after diving suggest inner ear barotrauma with possible perilymphatic fistula, from a ruptured round or oval window membrane; it needs prompt specialist assessment and avoidance of straining.
- Flying with a cold. Use a topical decongestant before descent and swallow or yawn frequently; the decongestant shrinks the mucosa around the eustachian tube opening so it can open and equalize pressure.
- Undrained auricular swelling. Left undrained, a swollen ear leads to permanent deformity, known as cauliflower ear.
- Avulsed auricle. Recovered detached tissue should be reattached; reattachment is often successful.
- Auricular hematoma. A tense, boggy swelling of the auricle with loss of the normal ridges should be drained now; early drainage is what prevents permanent deformity.
- Earlobe keloid. After excision the patient must be followed closely for recurrence, which is common.
- Auricular hematoma. Drain within seven days; after that, granulation tissue makes drainage much harder.
- Auricle blow that looks bruised but not swollen. Arrange re-examination in twelve to twenty-four hours, because the collection can appear hours after the injury.
- Perichondritis. A red, hot, exquisitely tender auricle that spares the lobule, which contains no cartilage, implicates the perichondrium. Pseudomonas is the usual organism after high piercings, so treatment needs antipseudomonal antibiotics or the cartilage necroses and the ear deforms.
- Swollen, tense, purple auricle. Blood collecting between the perichondrium and the cartilage strips the cartilage of its blood supply, which comes entirely from the perichondrium; untreated it necroses into cauliflower ear, so treat with drainage and a pressure dressing, which stops it reaccumulating.
- Keloid. Firm rounded overgrowths of scar tissue at a site of previous trauma, extending beyond the original wound.
1.3 · The eustachian tube and pressure
Eustachian tube dysfunction Routine
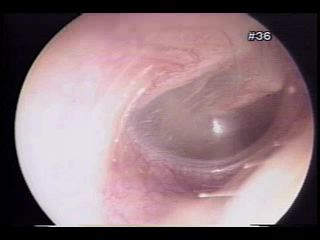
Gives itself away by: Fullness after a cold · crackling or popping on swallowing · retracted drum
- Presentation & who gets it
- Edema of the tube lining after an upper respiratory infection or allergy stops the tube equalizing pressure. Fullness, mild to moderate hearing impairment, and crackling or popping with yawning or swallowing, which indicates the blockage is only partial. Usually transient — days to weeks.
- Pain / hearing loss / key finding
- No — fullness · Conductive, mild to moderate · Retracted drum, reduced mobility
- Testing & cause
- Clinical. Otoscopy: retraction of the tympanic membrane and decreased mobility on insufflation. Tympanometry, taught in the next lecture, shows a negative pressure peak.
- First-line treatment
- Systemic or intranasal decongestants and intranasal corticosteroids. Forced exhalation against resistance. Caution with active nasal discharge — that maneuver can force infected fluid into the middle ear and trigger acute otitis media.
- Education & prognosis
- Avoid air travel and other pressure changes until symptoms resolve. It is the commonest single reason an ear will not clear on a plane.
Slides 6–10
Barotrauma Routine
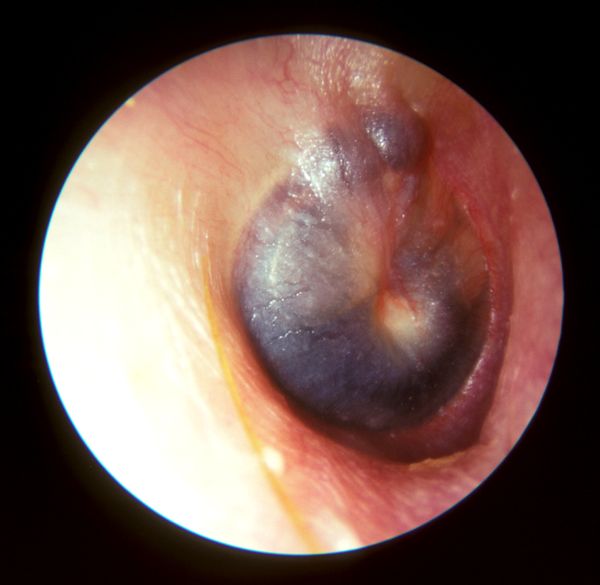
Gives itself away by: Cannot equalize · flying or SCUBA · hemotympanum behind the drum
- Presentation & who gets it
- Inability to equalize middle ear pressure, seen with air travel, rapid altitude change and SCUBA diving. May rupture the tympanic membrane or bleed into the middle ear. Otalgia and conductive hearing loss.
- Pain / hearing loss / key finding
- YES — otalgia · Conductive; sensorineural if the window ruptures · Hemotympanum, reduced mobility
- Testing & cause
- Otoscopy: decreased mobility on insufflation, visible hemotympanum if there is hemorrhage, visible perforation if present. Severe cases can rupture the round or oval window, adding tinnitus, sensorineural hearing loss, vertigo, nausea and vomiting — that combination means the inner ear is involved.
- First-line treatment
- Equalize by swallowing, yawning, exhaling through the nose against resistance. Oral or intranasal decongestants may help. Myringotomy gives instant relief and is reserved for severe otalgia and hearing loss with an intact membrane (ENT). Recurrent episodes in frequent flyers may justify tympanostomy tubes (ENT).
- Education & prognosis
- Avoid pressure changes while a respiratory illness or allergy flare is active. If flying is unavoidable, take a decongestant beforehand and equalize on descent.
Slides 22–25
Also tested
- Ear discharge character. Scanty discharge suggests the canal, which has no mucous glands; mucoid discharge suggests the middle ear, where mucous membrane exists, and profuse mucoid otorrhea comes through a perforation.
- Allergic rhinitis and the ear. Mucosal edema obstructs the eustachian tube, which is lined by the same respiratory mucosa as the nose; trapped middle ear air is absorbed, the drum retracts, and fullness with popping results.
- Eustachian tube dysfunction. When the tube cannot ventilate the middle ear, trapped air is absorbed, pressure falls below atmospheric and the drum retracts. Tympanometry shows a type C tympanogram, with the peak shifted to negative pressure.
- Normal tympanic membrane. The normal drum is pearly gray; loss of that appearance is the first sign something lies behind it.
- Pneumatic otoscopy. Puffing air against the drum through a bulb assesses whether the drum moves; reduced mobility signals fluid or pressure behind it.
- Normal drum. A normal tympanic membrane is pearly gray and mobile.
- Forceful exhalation against a pinched nose. With purulent nasal discharge it can force infected material into the middle ear, which risks acute otitis media.
- Diving ear pain with vertigo. Spinning vertigo, ringing, nausea and reduced hearing mean the inner ear has been involved; rupture of the round or oval window adds these features.
- Chronic otitis media. A perforation that has failed to heal, with recurrent painless discharge and conductive hearing loss over years, defines chronic suppurative otitis media; absence of pain separates it from acute infection, and absence of keratin debris or a retraction pocket separates it from cholesteatoma.
- Eustachian tube in young children. The child's tube is shorter, wider and flatter (nearly horizontal) than the adult tube, which runs downward at an angle, so nasopharyngeal secretions and organisms reach the middle ear easily and drain poorly; this is why young children get infections more often than adults.
- Barotrauma. Severe ear pain and muffled hearing beginning during the descent of a flight, with a dark blue-black drum that barely moves on insufflation, indicate barotrauma with hemotympanum (blood behind the eardrum).
1.4 · The otitis media family
Acute otitis media Routine
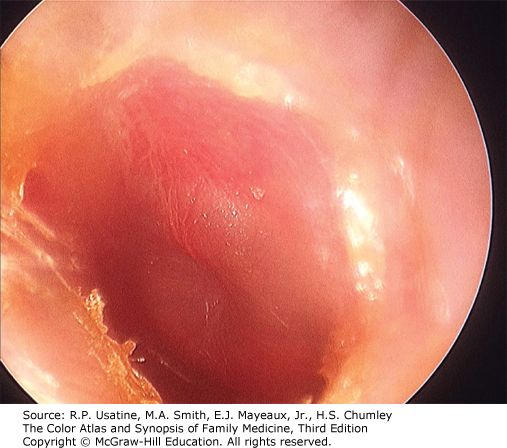
Gives itself away by: Bulging, erythematous drum · otalgia and fever after a cold · child around 2 years
- Presentation & who gets it
- Rapid-onset middle ear inflammation, most often following an upper respiratory illness. Commonest in children, peak incidence around age 2; adults are only 3–15% of diagnoses. Otalgia, fever, hearing loss. Suppurative form discharges into the canal through a perforation. Recurrent means 3 or more episodes in 6 months, or more than 4 in 12 months, with complete resolution between.
- Pain / hearing loss / key finding
- YES — otalgia with fever · Conductive · Bulging, erythematous drum
- Testing & cause
- Diagnosed clinically. Otoscopy: erythematous and/or bulging drum, purulent effusion often visible, decreased mobility on pneumatic otoscopy, sometimes palpable cervical nodes. Tympanometry optional. Far and away the commonest cause is VIRAL — the slide lists only bacteria. The three bacterial organisms are S. pneumoniae, H. influenzae and M. catarrhalis. That sequence used to run in order of prevalence; M. catarrhalis has now overtaken H. influenzae because of vaccination, so ask the immunization status — an unimmunized child puts H. influenzae back on the list.
- First-line treatment
- Most episodes resolve spontaneously. Antibiotics for bacterial involvement — amoxicillin. Analgesics and antipyretics for the pain and fever. Tympanostomy tubes for refractory or recurrent episodes, or when complications are present (ENT).
- Education & prognosis
- Explain that most cases settle on their own, so a wait-and-see period is not neglect — most of these are viral. Return if pain worsens or discharge appears.
Slides 12–19
Otitis media with effusion Routine
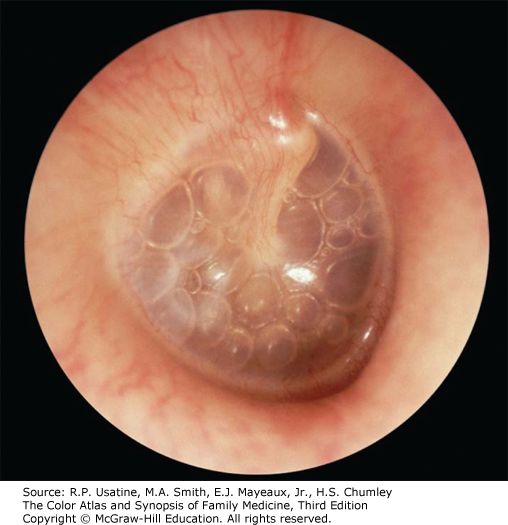
Gives itself away by: Dull drum with an air–fluid level · often asymptomatic · found incidentally
- Presentation & who gets it
- Middle ear inflammation with an effusion but without acute infection. Follows eustachian tube dysfunction trapping fluid, and often persists after a bacterial acute otitis media has resolved. Often asymptomatic and picked up incidentally on otoscopy; otherwise hearing loss and fullness.
- Pain / hearing loss / key finding
- NO — often asymptomatic · Conductive, temporary · Dull drum, air–fluid level
- Testing & cause
- Clinical. Otoscopy: dull tympanic membrane, air/fluid level often visible, decreased mobility on pneumatic otoscopy. Tympanometry optional — a type B curve fits the stiff, fluid-filled middle ear.
- First-line treatment
- Most resolve spontaneously. The decision to intervene turns on how long the fluid has been there, the degree of hearing loss, and the effect on speech and language development. Tympanostomy tubes (ENT); adenoidectomy if hypertrophy is obstructing the tubes (ENT).
- Education & prognosis
- In a child the risk is not the ear but the speech and language delay from months of muffled hearing — which is why duration matters more than the appearance.
Slides 13–19
Chronic otitis media Routine
Gives itself away by: Non-healing perforation · recurrent infection · persistent drainage
- Presentation & who gets it
- Recurrent infection with a non-healing perforation of the tympanic membrane. Duration required for diagnosis is controversial — weeks to months. Three subtypes: benign (dry perforation, no active infection); with effusion, also called chronic serous otitis media (continuous serous drainage through the perforation); and chronic suppurative (persistent purulent drainage).
- Pain / hearing loss / key finding
- Varies with activity · Conductive · Non-healing perforation
- Testing & cause
- Clinical, on the persistent perforation and drainage. Audiometry for the associated conductive loss.
- First-line treatment
- Refer to ENT.
- Education & prognosis
- The perforation is the disease, not just its aftermath — water precautions and follow-up matter because it will not close on its own.
Slides 20
Mastoiditis Urgent
Gives itself away by: Complication of acute otitis media · infection spreading to the mastoid air cells
- Presentation & who gets it
- Spread of acute otitis media infection into the mastoid air cells. Listed with tympanic membrane perforation, labyrinthitis and the rare meningitis or encephalitis as the complications of acute otitis media.
- Pain / hearing loss / key finding
- YES · Conductive · Complication of acute otitis media
- Testing & cause
- Suspected clinically in a child with acute otitis media who is not improving. Imaging defines the extent.
- First-line treatment
- Treat as a complicated acute otitis media — ENT involvement.
- Education & prognosis
- It is the reason acute otitis media that is not settling gets re-examined rather than simply re-prescribed.
Slides 19
Also tested
- Straightening the canal in a toddler. The infant and toddler canal runs upward from the drum, so pull the pinna downward and backward. In older children and adults the pinna is pulled up and back.
- Painless discharge in chronic suppurative otitis media. The perforation gives the middle ear a permanent outlet, so pressure never builds and infection appears as discharge rather than pain. Painlessness is the hallmark separating chronic from acute disease.
- Watchful waiting in acute otitis media. Observation is reasonable with a plan to treat if not improving, provided the child is older, disease is mild and follow-up is reliable. Start antibiotics if there is no improvement in 48 to 72 hours.
- Otitis media failing amoxicillin. Persisting fever and a bulging drum after 72 hours of adequate first-line therapy suggest a beta-lactamase producing organism, typically Haemophilus influenzae or Moraxella catarrhalis. Change to amoxicillin-clavulanate, which keeps pneumococcal coverage.
- Course of acute otitis media. Most episodes resolve spontaneously, which is why watchful waiting is reasonable.
- Diagnosing acute otitis media. With fever, ear pain and a red bulging drum, no confirmatory test is needed; the diagnosis is clinical.
- Unvaccinated child with acute otitis media. Haemophilus influenzae becomes a greater concern, because vaccination is why that organism has become less common.
- Mastoiditis. The mastoid air cells communicate directly with the middle ear, forming one continuous mucosa-lined space, so infection extends by direct continuity; mastoiditis is the classic suppurative complication of untreated otitis media.
- Conductive loss from middle ear fluid. Weber lateralizes toward the affected ear (here, to the right), and bone conduction exceeds air conduction in that ear.
- Recurrent otitis media with persistent effusion. Recurrent acute infections plus a persistent bilateral effusion (flat tympanograms) and hearing concern at the age of language acquisition justify referral for consideration of tympanostomy tubes, which ventilate the middle ear, restore hearing and reduce recurrence.
- Effusion after treated otitis media. Sterile fluid often takes weeks to months to clear as the eustachian tube recovers. An amber, non-bulging drum in an afebrile, painless child is a resolving effusion, so management is observation, with intervention reserved for persistence or developmental concern.
- Chronic otitis media in primary care. Management is referral to an ear, nose and throat specialist.
- Cause of acute otitis media. By far the commonest cause overall is a virus; most episodes are viral, which is why most resolve without antibiotics.
- Ear infection after a cold. Ear pain in a child a few days into a runny nose and cough is most likely acute otitis media caused by a virus; most acute otitis media is viral, so most resolves without antibiotics.
- Acute otitis media treatment. A bulging drum with reduced mobility and acute fever indicates bacterial acute otitis media, not a simple effusion. High-dose oral amoxicillin is first line in a child with no recent antibiotic exposure and no penicillin allergy.
1.5 · The tympanic membrane and behind it
Tympanic membrane perforation Routine
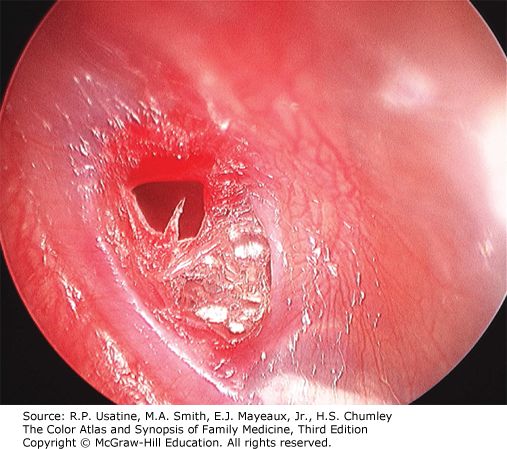
Gives itself away by: Pain stops after the rupture · conductive loss · visible defect
- Presentation & who gets it
- Follows impact injury, explosive acoustic trauma, barotrauma or severe acute otitis media. Symptoms vary with cause but it is generally not painful once the membrane has ruptured. Conductive hearing loss. Otoscopy distinguishes central (does not reach the margin) from marginal (involves the margin); drainage through the perforation if it followed acute otitis media.
- Pain / hearing loss / key finding
- Stops once it ruptures · Conductive · Visible defect, central or marginal
- Testing & cause
- Clinical, on otoscopy.
- First-line treatment
- Most resolve spontaneously over several weeks — and as little as 48–72 hours when it followed acute otitis media. Surgical reconstruction for large perforations or ones present a long time (ENT).
- Education & prognosis
- Keep the ear dry while it heals. Report worsening hearing or dizziness — trauma can disrupt the ossicles as well.
Slides 45–47
Cholesteatoma Urgent
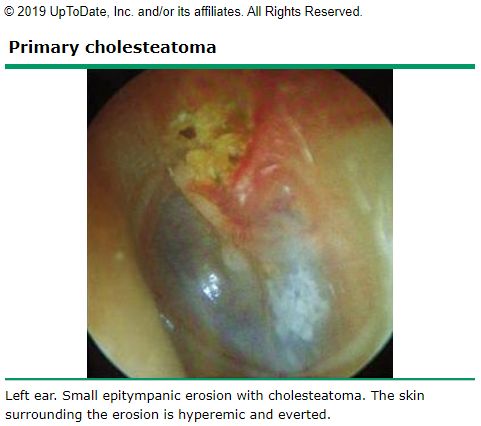
Gives itself away by: Keratin debris in a retraction pocket · recurrent otorrhea with no otitis externa
- Presentation & who gets it
- A collection of keratinized squamous epithelium in the middle ear or mastoid. No cholesterol in it and not a neoplasm, despite the name. Primary is commonest and forms from retraction of the tympanic membrane, usually the pars flaccida; secondary follows epithelial migration or surgery; congenital is least common and forms with no retraction or perforation. Risk factors are eustachian tube dysfunction and chronic middle ear inflammation. May be asymptomatic; otherwise tinnitus, recurrent otorrhea in the absence of otitis externa, and hearing loss as a late finding.
- Pain / hearing loss / key finding
- No — otorrhea · Conductive, a late finding · Keratin debris in a retraction
- Testing & cause
- Usually a clinical diagnosis. Otoscopy: retraction containing squamous epithelium and keratin debris, debris behind the drum, sometimes purulent otorrhea, granulation tissue or visible ossicular erosion. Audiometry to assess hearing loss. CT for extent in severe cases, and useful in secondary acquired disease when the drum is opaque.
- First-line treatment
- Refer to ENT. Remove canal debris, treat infection with antibiotics, then surgical removal, usually with tympanoplasty. Mastoidectomy if it extends into the mastoid with bony erosion.
- Education & prognosis
- It erodes bone, so it is removed rather than watched — the discharge is a symptom of that, not a simple infection.
Slides 31–37
Also tested
- Cholesteatoma complications. Vertigo with a same-sided facial palsy involving the forehead means the cholesteatoma is eroding into the labyrinth and facial nerve canal. Accumulating keratin releases enzymes that erode adjacent bone.
- Imaging cholesteatoma. Computed tomography defines the extent of a suspected cholesteatoma and is especially useful when the drum is opaque and extent cannot be judged by looking.
- Perforation after acute otitis media. A small perforation that follows discharge may close within days, in as little as forty-eight to seventy-two hours.
1.6 · Conductive fixation and neoplasms
Otosclerosis Routine
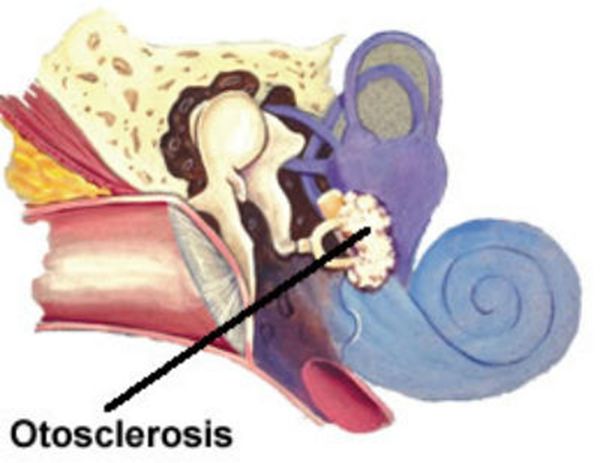
Gives itself away by: Hearing is better in background noise · gradual conductive loss · normal drum
- Presentation & who gets it
- Bony overgrowth affecting the stapes, which eventually fixes and causes hearing loss. Gradual conductive loss, bilateral and asymmetric in 70%, unilateral in 30%. The patient reports that hearing is better with background noise. Tinnitus.
- Pain / hearing loss / key finding
- NO · Conductive, gradual · NORMAL drum
- Testing & cause
- Visual examination is normal — its job is to exclude the other causes of conductive loss such as foreign body and cerumen impaction. Weber lateralizes to the affected ear (or the more affected ear if bilateral) and bone conduction is greater than or equal to air conduction on Rinne. Audiometry for the extent; CT is the initial imaging of choice. Differential: perforation, severe tympanosclerosis, otitis media with effusion, cholesteatoma, ossicular discontinuity, middle ear tumor.
- First-line treatment
- Observation if unilateral or the patient is untroubled. Hearing aids. Surgery is elective, generally one ear at a time, replacing the stapes with a prosthesis or placing a cochlear implant (ENT). Non-surgical options under investigation — sodium fluoride, bisphosphonates — with recommendations varying widely (ENT).
- Education & prognosis
- A conductive loss with a normal-looking drum is the pattern; improved hearing in noise is the sentence patients volunteer.
Slides 65–67
Carcinoma of the ear canal Emergent
Gives itself away by: Otitis externa that will not respond to treatment · bloody otorrhea · friable canal
- Presentation & who gets it
- Very rare and aggressive. Presents with an abnormal growth in the ear canal, bloody otorrhea, a friable ear canal and failure to respond to treatment for external otitis. Late findings are hearing loss and facial paralysis. Often misdiagnosed as otitis externa.
- Pain / hearing loss / key finding
- YES · Conductive, late · Friable growth, bloody otorrhea
- Testing & cause
- Definitive diagnosis is biopsy.
- First-line treatment
- Biopsy first, then oncological management (ENT).
- Education & prognosis
- The teaching point is the misdiagnosis: an otitis externa that does not respond, especially with blood, gets looked at again rather than re-treated.
Slides 71
Also tested
- Wax impaction. Complete occlusion by wax causes a purely mechanical conductive loss; the drum, ossicles and cochlea are normal. Weber lateralizes to the blocked ear and hearing returns to baseline once the wax is removed.
- Non-healing external ear "infection". An external ear problem that fails repeated treatment and now bleeds on touch with an irregular growth needs a biopsy of the lesion, because canal carcinoma is often misdiagnosed as external otitis.
- Rinne test. It compares air conduction against bone conduction in one ear.
- Weber test. It compares bone conduction between the two ears: a tuning fork is placed on the midline and the patient says which side is louder.
- Otosclerosis. It causes gradual conductive hearing loss with a normal-looking drum, and hearing is better in noise than in a quiet room.
2 · Disorders of the Inner Ear, Balance and Hearing Loss
Instructional Objectives
DISORDERS OF THE EARS, NOSE, THROAT AND NECK — Inner Ear, Balance and Hearing Loss
- Compare and contrast the etiologies, epidemiology, risk factors, clinical
manifestations, differential diagnosis, diagnostic testing (including ordering and
interpretation), management (acute and chronic, including applicable rehabilitative and
palliative care), appropriate referrals, patient education, and prognosis of the following
disorders of the inner ear, balance, and hearing loss:
- Acoustic neuroma
- Hearing impairment
- Sensorineural
- Conductive
- Tinnitus
- Ototoxicity
- Mastoiditis
- Vertebro-basilar arterial occlusion
- Labyrinthitis
- Benign paroxysmal positional vertigo
- Meniere’s disease
- Explain the difference between Weber and Rinne testing.
- Apply Weber and Rinne findings to sensorineural and conductive hearing loss.
- Explain how to interpret an audiogram and tympanogram.
- Describe vestibular testing and indications for ordering vestibular testing.
- Interpret results of vestibular testing.
- Identify medical care strategies for disorders of the inner ear, balance, and hearing loss in the lecture topic list for the following populations: 1. infant · 2. child · 3. adolescent · 4. adult
Four of the seven objectives are about the TESTS, not a disease. Objectives b through f ask you to explain Weber against Rinne, apply their findings, read an audiogram and a tympanogram, and describe and interpret vestibular testing. That is why this section opens with them rather than with a condition.
Sort the vertigo by duration first. Seconds → benign positional vertigo. Minutes to hours → Ménière’s. Days to weeks → labyrinthitis or vestibular neuronitis, and the one word separating those two is whether hearing is affected. She called the types-of-vertigo table one to “definitely know”.
2.1 · Weber, Rinne, and reading the two tracings
She stopped the lecture to say a question like this is on the paper. Her words: “this is what I expect you to get right on the test, because there is a test question like this.” The vignette she worked through:
A 39-year-old man is evaluated for right ear fullness and decreased hearing that developed after an upper respiratory tract infection. He denies tinnitus, vertigo, fever and ear drainage. On examination an amber effusion is visible behind an intact right tympanic membrane, which has decreased mobility. The left ear is normal. Which Weber and Rinne findings are most likely?
A right middle ear effusion is a conductive loss, so Weber lateralizes to the right and Rinne becomes abnormal on the right, with bone conduction at least equal to air.
She also described the question the other way round, and it is worth writing down: “I can give you these Weber and Rinne results and you’ll automatically know if it’s conductive or sensorineural … I have things like wax impaction on there, and that would be the answer, because the other choices wouldn’t be conductive.” The distractors die on loss type before you think about anything else.
| Weber | Rinne | Voice | In noise | |
|---|---|---|---|---|
| Normal | No lateralization | AC > BC | Normal | Normal |
| Conductive | TO the bad ear | BC ≥ AC | Soft | Better |
| Sensorineural | AWAY, to the good ear | AC > BC (same as normal) | Loud | Worse |
Why Weber carries the diagnosis. A sensorineural loss leaves the Rinne relationship looking exactly like a normal ear — air still beats bone. Only Weber separates them.
Audiometry severity, and she flagged this chart to know outright. It runs in twenties: normal 0–20 dB, mild 20–40, moderate 40–60, severe 60–80, profound above 80. Her own words for it: “it's all by 20s.” The prevalence percentages on the neighboring slide are explicitly NOT to be memorized — “you don’t have to memorize these statistics”.
Tympanometry, by shape. A normal · B flat, meaning fluid or a perforation · C peak shifted negative, meaning eustachian tube dysfunction · As shallow and stiff, meaning ossicular fixation or tympanosclerosis · Ad deep and over-compliant, meaning ossicular discontinuity or a monomeric drum.
Vestibular testing. Electronystagmography is the gold standard for a disorder affecting one ear at a time; magnetic resonance imaging with gadolinium is the gold standard when retrocochlear disease is suspected; the Dix-Hallpike maneuver diagnoses positional vertigo and the Epley maneuver treats it.
Also tested
- Wax removal with possible drum defect. Irrigation is contraindicated when the drum may not be intact, since water forced into the middle ear causes suppurative otitis media; use microsuction or a curette under direct vision.
- Mixed hearing loss. An air-bone gap indicates a conductive component, and elevated bone conduction thresholds indicate a sensorineural component. Both together define a mixed loss, so correcting the conductive part will not restore normal hearing.
- Shallow tympanogram peak at normal pressure. It indicates a stiff mechanism, as in ossicular fixation (type As), pointing to otosclerosis or tympanosclerosis.
- Weber lateralizing to one ear. A Weber that lateralizes to the left ear means a left conductive loss or a right sensorineural loss: it lateralizes toward a conductive loss and away from a sensorineural loss, so only Rinne separates the two.
- Keloid. An overgrowth of collagen in response to skin injury that extends beyond the boundaries of the original wound, unlike a hypertrophic scar, which stays within it; ear piercing is the classic auricular trigger, and keloids recur readily after excision.
- Tympanogram. Type A indicates a normal middle ear.
2.2 · The two patterns, and presbycusis
Conductive hearing loss Routine
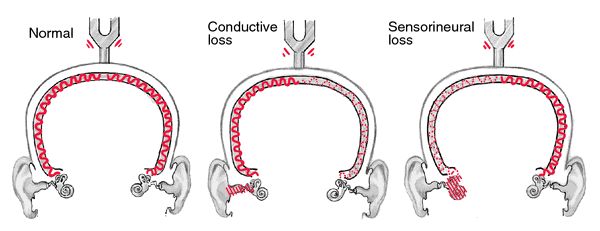
Gives itself away by: Weber lateralizes TO the bad ear · BC ≥ AC · hearing better in noise
- Presentation & who gets it
- An external or middle ear disorder impairing sound conduction to the inner ear. Four mechanisms: obstruction (cerumen), mass loading (effusion), stiffness (otosclerosis) and discontinuity (ossicular disruption). Onset is typically childhood to age 40. The abnormality is usually visible on otoscopy — except in otosclerosis. Hearing seems to improve in a noisy environment and the voice stays soft, because the inner ear and cochlear nerve are intact. Causes: cerumen impaction*, eustachian tube dysfunction*, otitis media, perforation, otosclerosis, foreign body, cholesteatoma, exostosis, glomus tumor, ossicular discontinuity (*commonest in adults).
- Pain / hearing loss / key finding
- Depends on the cause · Conductive · Weber TO the bad ear; BC ≥ AC
- Testing & cause
- Weber lateralizes to the impaired ear. Rinne: BC = AC or BC > AC. Audiometry for the degree; tympanometry for the middle ear.
- First-line treatment
- Treat the cause. Often correctable — which is the headline difference from sensorineural loss.
- Education & prognosis
- The reassuring half of the pair: most conductive loss has a fixable mechanical cause.
Slides 10–11, 42
Sensorineural hearing loss Urgent
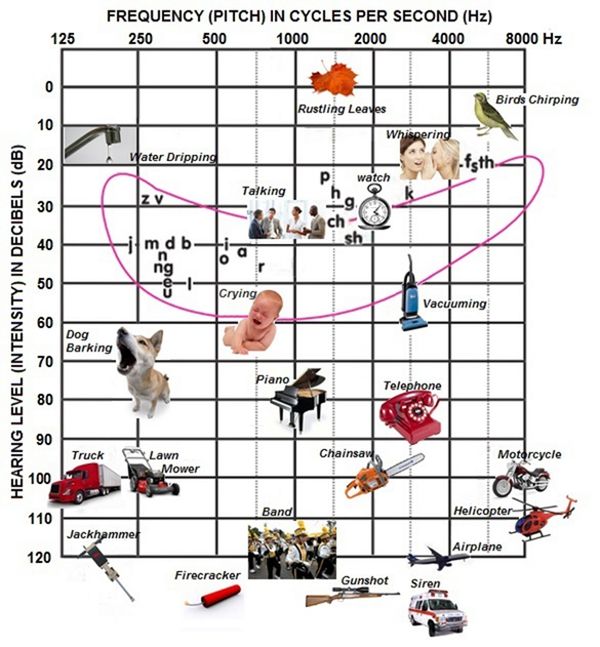
Gives itself away by: Weber lateralizes AWAY to the good ear · AC > BC · worse in noise
- Presentation & who gets it
- Sensory (deterioration of the cochlea and loss of hair cells) and neural (lesions of the eighth nerve, auditory nuclei, ascending tracts, auditory cortex) are difficult to separate clinically and are grouped together. Onset in middle or later years; the ear canal and drum look normal. Higher registers are lost so sound is distorted, hearing worsens in a noisy environment, and the voice may be loud because hearing is difficult.
- Pain / hearing loss / key finding
- No · Sensorineural · Weber to the GOOD ear; AC > BC
- Testing & cause
- Weber lateralizes to the GOOD ear. Rinne: AC > BC — the same as normal, which is why Weber carries the diagnosis. Audiometry classifies severity: normal 0–20 dB, mild 20–40, moderate 40–60, severe 60–80, profound >80 dB. It is all by 20s — 20, 40, 60, 80, which is how it was given in the lecture, and it is one of the few charts flagged as one to know outright.
- First-line treatment
- Usually not correctable, but may be stabilized and some types prevented. Acute-onset sensory loss may respond to corticosteroids in the first weeks.
- Education & prognosis
- The window for steroids in sudden loss is short, which is why new one-sided hearing loss is not a wait-and-see problem.
Slides 12–14, 42
Presbycusis Routine
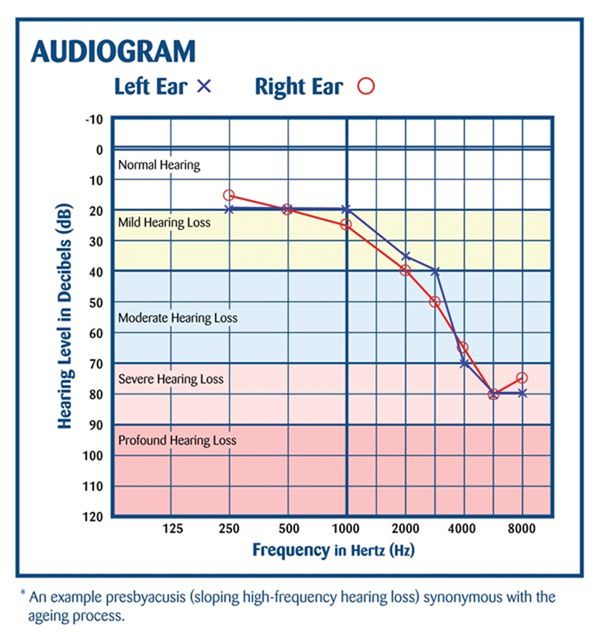
Gives itself away by: Hears people speak but cannot make out words · bilateral · high frequency first
- Presentation & who gets it
- The commonest sensorineural hearing loss. Progressive age-related loss from hair cell loss in the organ of Corti and cochlear nerve degeneration. Bilateral, symmetrical, gradual. High frequencies go first, progressing to mid and low. Patients hear speech but cannot make out the words, miss the doorbell and the phone, may have tinnitus, and lip-read more than they realize. It is common enough that primary care screens everyone aged 65 and over for it as a matter of routine. The prevalence percentages on the slide are explicitly not to be memorized — “you don’t have to memorize these statistics”.
- Pain / hearing loss / key finding
- No · Sensorineural, bilateral · High-frequency loss, normal drum
- Testing & cause
- Audiometry showing bilateral symmetrical high-frequency loss.
- First-line treatment
- Amplification and communication strategy. Not correctable.
- Education & prognosis
- Face the patient, do not shout — volume is not the problem, discrimination is.
Slides 15, 60–61
Also tested
- Otosclerosis counseling. It often runs in families and may worsen during pregnancy.
- Imaging in sudden hearing loss. Magnetic resonance imaging is done to exclude a retrocochlear lesion such as a schwannoma, because a proportion of sudden loss turns out to be vestibular schwannoma and clinical features cannot identify them.
- Ototoxic drug classes. Aminoglycosides destroy cochlear hair cells, usually permanently, starting at high frequencies; loop diuretics affect the stria vascularis and their effect is more often reversible.
- Childhood hearing loss urgency. Language acquisition depends on hearing during a limited early-childhood window. Reduced auditory input then produces delays that persist even after hearing is restored, so the threshold to intervene is lower than in adults.
- Aminoglycoside monitoring. Baseline and serial audiometry are used because aminoglycosides damage the outer hair cells at the cochlear base, which encode the highest frequencies. Early detection allows the drug to be changed, as the damage is usually permanent.
- Otosclerosis on tuning fork testing. Abnormal bone fixes the stapes footplate in the oval window, so bone conduction exceeds air conduction on the affected side (reversed Rinne). The cochlea is normal, so this is a conductive loss.
- Untreated presbycusis. Reduced auditory input contributes to social withdrawal, isolation, depression and accelerated cognitive decline. Framing hearing aids as protection against these is usually what persuades reluctant patients.
- Normal hearing range. Normal hearing is zero to twenty decibels, and the whole scale then runs in twenties.
- Hearing screening age. Hearing is screened routinely in primary care from age sixty-five.
- Profound hearing loss. Hearing loss is classified as profound above eighty decibels.
- Pure tone audiometry. This test presents single tones at set frequencies to find the softest audible level.
- Rinne in sensorineural loss. Air conduction remains greater than bone conduction bilaterally, because a sensorineural loss leaves the normal Rinne relationship intact.
- Ototoxicity. Loop diuretics are ototoxic; ototoxicity from the diuretic can explain a sensorineural hearing loss.
- Otosclerosis treatment. Stapedectomy and a hearing aid are both reasonable: surgery addresses the mechanism, an aid amplifies. Surgery carries a small chance of a sensorineural loss.
- High-frequency sensorineural loss. Consonants are high-frequency sounds and carry most of the meaning, whereas vowels are low-frequency and loud; losing high frequencies removes the information while leaving the sound.
- Weber in unilateral sensorineural loss. It lateralizes to the unaffected ear, away from the bad side.
- Age-related hearing loss. The characteristic audiogram is a curve sloping downward at high frequencies.
- Acoustic neuroma. It is a sensorineural cause of hearing loss: a tuning fork on the forehead is loudest in the unaffected ear, and in the affected ear air conduction exceeds bone conduction.
- Otosclerosis tuning fork findings. Otosclerosis is a conductive loss, so Weber lateralizes to the affected ear and bone conduction in that ear is at least equal to air.
2.3 · Tinnitus, and the masses you can see
Tinnitus Routine
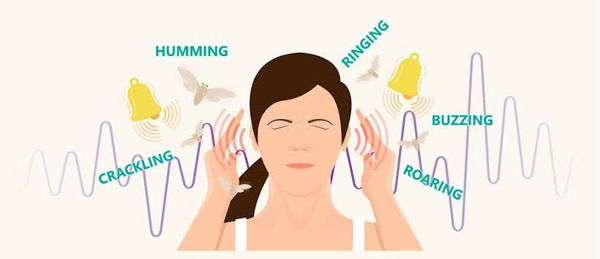
Gives itself away by: Ringing with no external source · RED FLAG: unilateral or pulsatile
- Presentation & who gets it
- Can accompany any type of hearing loss and is often the first symptom of it. Described as ringing, buzzing, humming, hissing, a motor running, insects. Usually subjective; occasionally objective, meaning the examiner can hear it too. Everyone hears normal head noise in silence; low tolerance for it is associated with depression, neurosis, stress and fatigue.
- Pain / hearing loss / key finding
- No · Any type — often the first symptom · Unilateral or pulsatile is the red flag
- Testing & cause
- Clinical. RED FLAG: unilateral or pulsatile tinnitus — that pattern is investigated rather than reassured.
- First-line treatment
- No drug has been more effective than placebo. Biofeedback and masking noises may work.
- Education & prognosis
- Avoid loud noise, get the lead level checked, avoid stimulants, exercise daily, get adequate rest, and learn to treat the noise as an annoyance rather than a threat.
Slides 44–46
Exostosis Routine
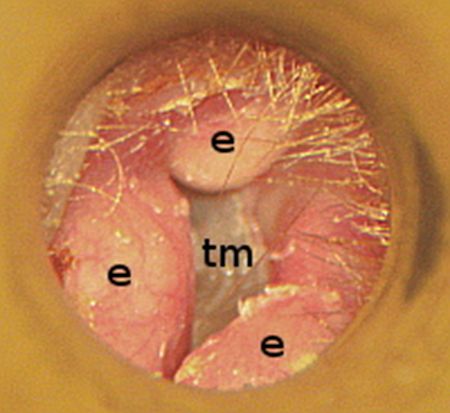
Gives itself away by: Surfer or diver · bilaterally symmetrical bony canal growths
- Presentation & who gets it
- Bony growth in the external canal, bilaterally symmetrical, related to repetitive cold water exposure — divers and surfers. Can block the canal or collect debris.
- Pain / hearing loss / key finding
- No · Conductive · Bilateral bony canal growths
- Testing & cause
- Otoscopy. Causes conductive hearing loss.
- First-line treatment
- Address obstruction and trapped debris; surgical removal if the canal is occluded.
- Education & prognosis
- Earplugs in cold water are the prevention; the growths themselves are slow and painless.
Slides 48
Glomus tumor Urgent
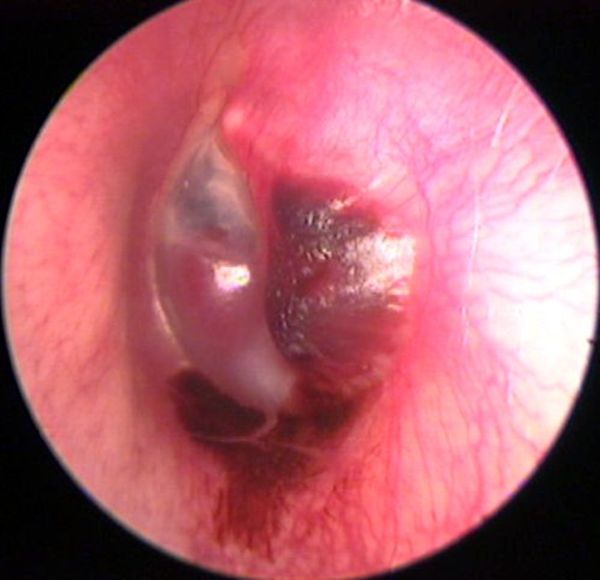
Gives itself away by: Pulsatile tinnitus · vascular middle ear mass · cranial nerve IX, X, XI palsy
- Presentation & who gets it
- Benign but highly vascular tumor derived from the normal glomus formations of the middle ear and jugular bulb. Produces a middle ear mass effect, can present with spontaneous hemorrhage and paralysis of cranial nerves IX, X and XI, and may erode the skull base.
- Pain / hearing loss / key finding
- No · Conductive · Vascular middle ear mass; pulsatile tinnitus
- Testing & cause
- Causes conductive hearing loss and pulsatile tinnitus — the combination that separates it. Imaging for extent.
- First-line treatment
- ENT and skull base management.
- Education & prognosis
- Pulsatile tinnitus with a mass behind the drum is not reassured away.
Slides 50
Also tested
- Exostoses. These are multiple smooth bony swellings of the canal wall that narrow the lumen but are covered by normal skin.
- Temporary threshold shift. Intense sound temporarily fatigues cochlear hair cells, and hearing recovers within 24 to 48 hours; repeated temporary shifts eventually become permanent, so recovery is a warning rather than a reassurance.
- Exostoses (surfer's ear). Repeated exposure to cold water stimulates new bone formation in the canal walls, giving bilateral, symmetrical swellings that trap water and debris and cause recurrent otitis externa.
- Jugular foramen mass. A tumor at the jugular foramen compresses cranial nerves nine, ten and eleven (glossopharyngeal, vagus, spinal accessory), causing difficulty swallowing, hoarseness and shoulder weakness alongside pulsatile tinnitus and conductive loss.
- Bilateral non-pulsatile tinnitus. With symmetrical sensorineural loss it is generated centrally as the brain compensates for reduced input. Management is reassurance, hearing aids and sound therapy; amplification often reduces it, and sound therapy reduces the contrast between tinnitus and silence.
- Tinnitus. It is sound perceived with no external source, such as ringing, buzzing, humming or hissing.
- Glomus tumor. Paralysis of the ninth, tenth and eleventh cranial nerves may accompany it.
- Unilateral pulsatile tinnitus. Tinnitus in one ear that beats in time with the pulse needs further investigation, since unilateral and pulsatile tinnitus are both red flags.
- Exostoses. Hard, smooth, symmetric swellings of the canal wall that narrow both canals and trap debris are exostoses, bony growths from repeated cold water exposure.
- Tinnitus drug treatment. No drug has proved better than placebo; masking and biofeedback may help instead.
- Tinnitus red flag. Pulsatile unilateral tinnitus requires investigation for a vascular cause. Tinnitus that is unilateral or synchronous with the pulse suggests turbulent blood flow or a vascular middle ear lesion such as a glomus tumor.
- Noise-induced hearing loss. Cumulative noise exposure classically produces an audiogram notch centered around 4000 hertz with some recovery at higher frequencies, unlike presbycusis, which declines progressively as frequency rises and does not recover; the curve shape makes the diagnosis.
2.4 · Acquired sensorineural loss
Ototoxicity Urgent
Gives itself away by: Bilateral sensorineural loss on a known drug · aminoglycosides
- Presentation & who gets it
- Aminoglycosides are the most ototoxic and the most common — monitor peak levels. Also furosemide, aspirin and platinum-based chemotherapy. Many other agents have potential ototoxicity, and drugs that are ototoxic are frequently also nephrotoxic and vice versa, including the non-steroidal anti-inflammatories. Produces bilateral sensorineural hearing loss.
- Pain / hearing loss / key finding
- No · Sensorineural, BILATERAL · Normal drum; drug history
- Testing & cause
- History of exposure plus audiometry. Monitor aminoglycoside peak levels.
- First-line treatment
- Stop or change the agent where possible; the loss is often not reversible.
- Education & prognosis
- If a drug is ototoxic, ask about the kidneys too — the two toxicities travel together.
Slides 52–53
Noise-induced hearing loss Routine
Gives itself away by: Temporary threshold shift recovering in 24–48 h · “crickets” and fullness
- Presentation & who gets it
- One of the most common occupationally induced disabilities; exposure is regulated by OSHA. Most acute exposures produce temporary sensorineural loss recovering in 24–48 hours — a temporary threshold shift, with the ear feeling full and “crickets”. If the level is high enough or repeated often enough the loss becomes permanent — a permanent threshold shift. Rarely, extremely intense impulse exposure perforates the drum, giving a conductive loss instead.
- Pain / hearing loss / key finding
- No — fullness, “crickets” · Sensorineural · Normal drum; exposure history
- Testing & cause
- Audiometry. Exposure history against the decibel table: damage is possible after 2 hours at 80–85 dB, 50 minutes at 95, 15 minutes at 100, under 5 minutes at 105–110, and pain and injury at 120.
- First-line treatment
- Remove the exposure and protect hearing. The permanent component is not recoverable.
- Education & prognosis
- The temporary shift is the warning shot — recovering by the next day does not mean no damage is accumulating.
Slides 54–55
Acoustic trauma Urgent
Gives itself away by: Single loud noise · immediate loss · may perforate the drum
- Presentation & who gets it
- A single loud noise creating immediate hearing loss, and it may perforate the tympanic membrane. Blows to the head can cause labyrinthine injury with resulting sensorineural loss. Penetrating injuries are rare but usually involve subluxation of the stapes, causing profound sensorineural loss.
- Pain / hearing loss / key finding
- YES at the time · Sensorineural; conductive if perforated · May show perforation
- Testing & cause
- Audiometry. Depending on the type, the loss can mimic noise-induced loss or be a complete loss of both auditory and vestibular function.
- First-line treatment
- Supportive; ENT for perforation or suspected ossicular injury.
- Education & prognosis
- One event can do what years of exposure does — and a penetrating injury threatens balance as well as hearing.
Slides 56–57
Perilymphatic fistula Urgent
Gives itself away by: Audible “pop” then sudden loss and vertigo after straining or barotrauma
- Presentation & who gets it
- A pathological communication between the perilymphatic space of the inner ear and the middle ear, at the round or oval window. Congenital or acquired. Acquired causes: barotrauma, temporal bone trauma, or a complication of stapedectomy. Presents as sudden sensorineural loss and vertigo after head injury, barotrauma, or heavy lifting and straining, sometimes with an audible “pop”. A rare cause of vertigo and sensorineural loss.
- Pain / hearing loss / key finding
- No · Sensorineural, sudden · Audible “pop” with vertigo
- Testing & cause
- Clinical, on the history. Fistula test is among the vestibular studies.
- First-line treatment
- Treat symptomatically and refer to ENT.
- Education & prognosis
- The trigger is the diagnosis: sudden hearing loss and vertigo that began with a strain, a dive or a blow.
Slides 63–64
Autoimmune sensorineural loss Urgent
Gives itself away by: Bilateral, progressive, in periods of deterioration and stabilization
- Presentation & who gets it
- Sensorineural loss that is most often bilateral and progressive, with periods of deterioration and stabilization, and may be accompanied by vestibular dysfunction. Uncommon: Cogan's syndrome, polyarteritis nodosa, relapsing polychondritis, granulomatosis with polyangiitis. Even less common: scleroderma, temporal arteritis, systemic lupus erythematosus, sarcoidosis.
- Pain / hearing loss / key finding
- No · Sensorineural, bilateral · Stepwise deterioration
- Testing & cause
- Routine screening for autoimmune disorders is not warranted — test when the picture suggests it.
- First-line treatment
- Treat the underlying disease.
- Education & prognosis
- The stepwise pattern — worse, then stable, then worse — is what distinguishes it from a steady decline.
Slides 65–66
Syphilitic sensorineural loss Urgent
Gives itself away by: Indistinguishable from Ménière's · the treatable cause you must not miss
- Presentation & who gets it
- Congenital or acquired. Hearing loss is not associated with primary acquired syphilis, but reaches as high as 80% in symptomatic neurosyphilis. Presentation is often indistinguishable from Ménière's: fluctuating sensorineural loss, tinnitus, aural fullness and episodic vertigo.
- Pain / hearing loss / key finding
- No · Sensorineural, fluctuating · Mimics Ménière's
- Testing & cause
- The one exception to not ordering labs. FTA-ABS and MHA-TP should be obtained. VDRL is not helpful.
- First-line treatment
- Antibiotic with the addition of systemic corticosteroids.
- Education & prognosis
- It is tested for precisely because it is a potentially treatable cause of sensorineural loss hiding behind a Ménière's picture.
Slides 35, 68
AIDS-related sensorineural loss Urgent
Gives itself away by: Unexplained sensorineural loss with risk factors present
- Presentation & who gets it
- Sensorineural loss is among the numerous neurological manifestations of AIDS. It may come from an infectious complication — cryptococcal meningitis or syphilis — or be a primary neurological manifestation.
- Pain / hearing loss / key finding
- No · Sensorineural · Unexplained loss with risk factors
- Testing & cause
- Consider in any patient with unexplained sensorineural loss and risk factors present.
- First-line treatment
- Treat the underlying cause.
- Education & prognosis
- It is on the list so that unexplained loss prompts a risk-factor history rather than an audiogram alone.
Slides 67
Hereditary sensorineural loss Routine
Gives itself away by: Waardenburg, Alport, Usher · and the nonsyndromic majority
- Presentation & who gets it
- Nonsyndromic hereditary hearing loss, plus the named syndromes: Waardenburg's, Alport and Usher's.
- Pain / hearing loss / key finding
- No · Sensorineural · Family history; syndromic features
- Testing & cause
- Family history; genetic evaluation where indicated.
- First-line treatment
- Amplification and the associated systemic disease.
- Education & prognosis
- The syndromic names carry the other organ involved — kidney in Alport, vision in Usher.
Slides 71
Sudden sensorineural hearing loss Emergent
Gives itself away by: Unilateral, sudden · a syndrome, not a disease · prompt ENT referral
- Presentation & who gets it
- Unilateral. Described explicitly as a syndrome, not a disease. Viral or vascular etiology; rarely retrocochlear pathology — horses not zebras. The exact cause is rarely certain.
- Pain / hearing loss / key finding
- No · Sensorineural, UNILATERAL · Normal drum, sudden onset
- Testing & cause
- Audiometry to confirm and side it. Imaging only in selected patients.
- First-line treatment
- Demands prompt referral to ENT. Acute sensory loss may respond to corticosteroids within the first weeks.
- Education & prognosis
- Speed is the whole management. This is the one hearing complaint that is seen the same day.
Slides 13, 79
Also tested
- Autoimmune inner ear disease. Rapidly progressive bilateral sensorineural loss is managed with a trial of systemic corticosteroids, which is both therapy and a diagnostic test, as it is one of the few sensorineural losses that responds to treatment.
- Sudden sensorineural hearing loss. It is a syndrome rather than a disease, and a cause is often never found; because the differential includes treatable and dangerous entries, it prompts urgent referral and imaging.
- Suspected perilymphatic fistula. Initial management is bed rest with head elevation and avoidance of straining, since the leak is pressure-dependent; many fistulae close spontaneously before surgical repair is considered.
- Syphilis testing in hearing loss. When syphilis is suspected as a cause, order fluorescent treponemal antibody and microhemagglutination assays.
- Syphilis in sensorineural hearing loss. It is specifically sought because it is treatable and mimics another condition exactly; its presentation is often indistinguishable.
- Sudden one-sided hearing loss. It needs same-day assessment because treatment works only if started early.
- Sensorineural loss with sexual infection risk. Consider human immunodeficiency virus and syphilis in unexplained sensorineural hearing loss with multiple risk factors, since both can produce it.
- Temporary threshold shift. It is hearing loss recovering in twenty-four to forty-eight hours.
- Sudden sensorineural hearing loss. It demands prompt specialist referral, because the corticosteroid window is short.
- Sudden hearing loss and vertigo after a dive. With a popping sensation at onset, management is symptomatic treatment and specialist referral.
- Sudden hearing loss and vertigo after heavy lifting. With a pop at onset, the likely mechanism is an abnormal opening at the round or oval window.
- Waardenburg syndrome. Sensorineural deafness with a white forelock, widely spaced medial canthi and heterochromia of the irises defines Waardenburg syndrome, a neural crest disorder; neural crest gives rise to the melanocytes of skin, hair and iris and to the stria vascularis of the cochlea.
- Waardenburg syndrome. Sensorineural hearing loss with a white forelock and eyes of different colors suggests Waardenburg syndrome, one of the named hereditary causes.
- Syphilis and inner ear symptoms. In fluctuating hearing loss, tinnitus and vertigo with suspected syphilis, the Venereal Disease Research Laboratory test should not be relied on; it is specifically described as not helpful here.
2.5 · The inner ear syndromes — sorted by how long the vertigo lasts
Benign paroxysmal positional vertigo Routine
Gives itself away by: Seconds of vertigo on rolling over · hearing normal, no tinnitus
- Presentation & who gets it
- Severe vertigo with change in head position — rolling over, getting into bed, standing up, bending, looking up to reach an object, tilting the head back to shave, a haircut, turning rapidly. A specific side is typically described. Symptoms come on after a short latency of 10–15 seconds and last only 10–60 seconds; more than a minute should prompt an alternative diagnosis. Bouts cluster in time with remissions of months or more. Between attacks there may be constant lightheadedness worse with head movement, and imbalance for hours after an episode.
- Pain / hearing loss / key finding
- No · NOT affected · Positive Dix-Hallpike; seconds only
- Testing & cause
- Diagnosed by the classic eye movements on the Dix-Hallpike maneuver plus a suggestive history. Most cases have no identifiable etiology; canalithiasis of the posterior semicircular canal is thought to be the commonest cause.
- First-line treatment
- The Epley maneuver, which repositions the otoliths in the semicircular canal.
- Education & prognosis
- Hearing is not affected and there is no tinnitus — those two absences are what place it against Ménière's.
Slides 89–93, 97
Ménière's disease Urgent
Gives itself away by: Vertigo hours long · LOW-frequency fluctuating loss · fullness and low-tone tinnitus
- Presentation & who gets it
- Fluctuating LOW-frequency sensorineural hearing loss that may fluctuate at first then progress. Low-tone, “blowing” tinnitus. Unilateral fullness in the ear. Episodes of vertigo, often the presenting complaint. Typical attack: episodic, spontaneous, severe spinning vertigo lasting several hours, frequently with nausea, vomiting and diaphoresis.
- Pain / hearing loss / key finding
- No — fullness · Sensorineural, LOW frequency, fluctuating · Vertigo lasting hours + tinnitus
- Testing & cause
- Clinical. Duration separates it: seconds for benign positional vertigo, minutes to hours for Ménière's, days to weeks for vestibular neuronitis and labyrinthitis. Rule out syphilis, which mimics it exactly.
- First-line treatment
- Symptomatic control of the attacks and the underlying management.
- Education & prognosis
- The tetrad is vertigo, fluctuating hearing loss, tinnitus and fullness — and unlike the other peripheral causes, hearing is affected.
Slides 69–70, 89, 97
Labyrinthitis Urgent
Gives itself away by: Sudden vertigo WITH hearing loss lasting days to weeks
- Presentation & who gets it
- Inflammation of the membranous labyrinth of the inner ear. Relatively sudden onset of sensorineural hearing loss AND acute vertigo. Exact etiology rarely certain; evidence supports a viral cause, and it may be associated with bacterial infection or systemic autoimmune disease. Also listed as a complication of acute otitis media.
- Pain / hearing loss / key finding
- No · Sensorineural — hearing IS affected · Sudden vertigo, days to weeks
- Testing & cause
- Clinical. Duration several days to weeks.
- First-line treatment
- Symptomatic. Antibiotics if bacterial symptoms such as fever are present. Oral corticosteroids. Oral diazepam or meclizine during the acute vertigo.
- Education & prognosis
- The difference from vestibular neuronitis is one word: labyrinthitis affects hearing.
Slides 95, 97
Vestibular neuronitis Urgent
Gives itself away by: Dramatic sudden vertigo with NO hearing change · benign and self-limiting
- Presentation & who gets it
- Inflammation of the vestibular portion of cranial nerve VIII, likely viral though the cause is unknown. Considered benign and self-limiting. Dramatic, sudden vertigo with nausea and gait imbalance. Dizziness lasts days with gradual improvement; balance symptoms may persist for months. Not associated with any change in hearing or focal neurological complaints.
- Pain / hearing loss / key finding
- No · NOT affected · Sudden vertigo, no hearing change
- Testing & cause
- Clinical diagnosis.
- First-line treatment
- Symptomatic. Oral diazepam or meclizine during the acute phase, antiemetics, and oral corticosteroids are questioned in the deck rather than asserted.
- Education & prognosis
- Normal hearing and no focal neurology is what makes it benign — either of those being abnormal moves the diagnosis.
Slides 96–97
Also tested
- Vestibular neuronitis counseling. It is benign and self-limiting and settles over days to weeks; patients should move about rather than lie still, since bed rest and vestibular suppressants delay central compensation.
- Otosyphilis. Syphilis can mimic Meniere disease exactly and is worth excluding serologically, because it has a specific curative treatment while Meniere does not.
- Meniere disease self-care. Restricting dietary salt, caffeine and alcohol is advised. The underlying abnormality is endolymphatic hydrops; less sodium lowers fluid retention and endolymph volume, and caffeine and alcohol are recognized triggers.
- Meniere disease. It is defined by episodic vertigo lasting minutes to hours, fluctuating sensorineural hearing loss, tinnitus and aural fullness, all in the same ear. Loss is low-frequency because the cochlear apex, which codes low frequencies, distends most from endolymphatic hydrops.
- Audiogram in Meniere disease. Loss confined to the low frequencies that improves between attacks suggests Meniere disease: a low-frequency, fluctuating sensorineural loss.
- Benign paroxysmal positional vertigo. Most cases are thought to be caused by debris in the posterior semicircular canal.
- Positional nystagmus on Dix-Hallpike. Nystagmus that begins after a brief delay, lasts under a minute and diminishes on repetition indicates a peripheral cause, consistent with positional vertigo; central positional nystagmus begins immediately, persists and does not fatigue.
2.6 · Retrocochlear, central, and not-organic
Acoustic neuroma Urgent
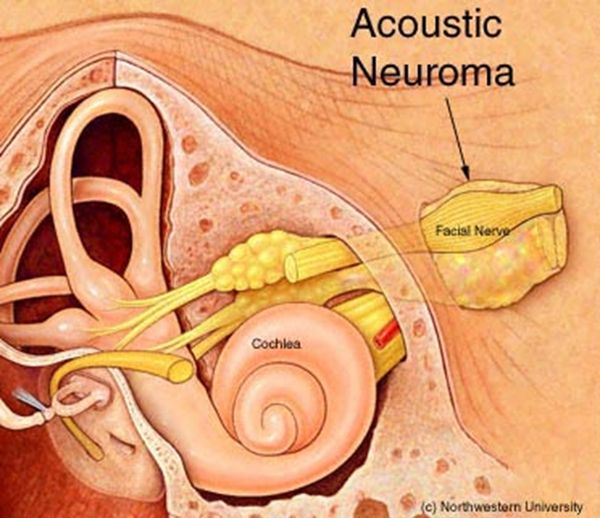
Gives itself away by: Unilateral loss with speech discrimination worse than the tone loss predicts
- Presentation & who gets it
- Benign tumor of cranial nerve VIII, rare, and most often unilateral. Symptoms: unilateral hearing loss, which may be sudden; poor speech discrimination compared with what the tone loss would predict; often disequilibrium. Progression may not be so “benign”. May involve cranial nerves V and VII.
- Pain / hearing loss / key finding
- No · Sensorineural, unilateral · Speech discrimination worse than expected
- Testing & cause
- MRI with gadolinium is the gold standard for evaluating potential retrocochlear loss. Electronystagmography is the gold standard vestibular test for disorders affecting one ear at a time. Radiographic imaging is warranted in selected patients with sensorineural loss.
- First-line treatment
- Observation with annual MRI, surgery, or radiation.
- Education & prognosis
- The discriminating symptom is not the volume of the loss but the disproportionately poor word understanding on the affected side.
Slides 72–75, 97
Vertebrobasilar insufficiency or occlusion Emergent
Gives itself away by: Vertigo in an elderly patient with brainstem signs
- Presentation & who gets it
- A common cause of vertigo in elderly patients. Occlusion may be thrombotic or embolic. Symptoms: acute vertigo, nausea and vomiting, facial paralysis, tinnitus, ipsilateral gaze paralysis, ipsilateral loss of pain and temperature on the face, contralateral partial loss of pain and temperature on the trunk and limbs, and ipsilateral Horner's syndrome. Vascular disease is the commonest non-vestibular cause of dizziness and balance loss in the elderly.
- Pain / hearing loss / key finding
- No · May be affected · Brainstem signs with the vertigo
- Testing & cause
- Magnetic resonance angiography, which also shows small vessel disease as scattered small white lesions. Carotid dopplers.
- First-line treatment
- Vascular and stroke management.
- Education & prognosis
- Vertigo with any crossed sensory finding, facial weakness or gaze palsy is a brainstem problem until proven otherwise.
Slides 77, 85–87
Isolated cerebellar infarction Emergent
Gives itself away by: Vertigo with ataxia, headache or facial numbness
- Presentation & who gets it
- Symptoms include vertigo, facial pain or numbness, headache, or ataxia. The deck's instruction is explicit: “Don't miss something bigger than the hearing loss” — look for signs of a more sinister acute problem.
- Pain / hearing loss / key finding
- Headache possible · Not affected · Ataxia, facial numbness
- Testing & cause
- Neuroimaging.
- First-line treatment
- Refer for evaluation.
- Education & prognosis
- It is in a hearing lecture as a warning, not as an ear disease.
Slides 78
Functional hearing loss Routine
Gives itself away by: Claims profound bilateral loss but the voice is normal
- Presentation & who gets it
- Suspected when the history contains inconsistencies, complaints and exaggerated listening effort. The patient's voice and speech quality provide important information: someone claiming significant bilateral loss while speaking at a normal level with normal articulation should be suspected of functional behavior.
- Pain / hearing loss / key finding
- No · Claimed, not organic · Normal voice despite claimed loss
- Testing & cause
- The mismatch between claimed loss and the voice is the finding. Audiometry with cross-checks.
- First-line treatment
- Address the underlying reason rather than the audiogram.
- Education & prognosis
- A genuinely deaf voice changes. That is the observation the diagnosis rests on.
Slides 80
Also tested
- Central versus peripheral vertigo. Headache, ataxia, or focal neurological signs raise concern for a central cause. Severe truncal ataxia, direction-changing nystagmus, diplopia, dysarthria or facial numbness point to the brainstem or cerebellum and require urgent imaging.
- Suspected non-organic hearing loss. Auditory brainstem response testing records electrical activity along the auditory pathway, giving a threshold estimate without the patient reporting anything. It resolves discrepancies between claimed and demonstrated hearing.
- Vertigo with crossed sensory findings. Acute vertigo with facial weakness, crossed loss of pain sensation and a drooping eyelid requires emergency evaluation for stroke, since crossed sensory findings mean a brainstem problem.
- Vestibular schwannoma and balance. Balance is only mildly affected because central compensation adjusts to a slowly growing lesion: vestibular input falls gradually over years and the brainstem and cerebellum recalibrate, so patients describe unsteadiness rather than the dramatic spinning of a sudden vestibular loss such as neuronitis.
3 · Disorders of the Nose and Paranasal Sinuses
Instructional Objectives
DISORDERS OF THE EARS, NOSE, THROAT AND NECK — Nose and Paranasal Sinuses
- Compare and contrast the etiologies, epidemiology, risk factors, clinical
manifestations, differential diagnosis, diagnostic testing (including ordering and
interpretation), management (acute and chronic, including applicable rehabilitative and
palliative care), appropriate referrals, patient education, and prognosis of the following
disorders of the nose and paranasal sinuses:
- Acute and chronic sinusitis
- Nasal trauma
- Deviated septum
- Perforated septum
- Septal hematoma
- Nasal fracture
- Epistaxis
- Nasal foreign body
- Nasal polyp
- Rhinitis: i. Allergic · ii. Vasomotor
- Neoplasms: i. Benign · ii. Malignant
- Identify medical care strategies for disorders of the nose and paranasal sinuses in the lecture topic list for the following populations: 1. adolescent · 2. adult · 3. elderly
The whole first half of this lecture is one decision: is it viral or bacterial? 90–98% of acute rhinosinusitis is viral, and only 0.5–2% of those develop a bacterial superinfection — yet it is the fifth leading reason antibiotics get prescribed. The features that shift you toward bacterial are:
- Double worsening — getting worse again more than 5–6 days after initially improving
- Persistent symptoms for 10 days or more
- Persistent purulent discharge
- UNILATERAL upper tooth or facial pain, or unilateral maxillary tenderness
- Fever, or altered mental status
Pain is the big distinguishing factor — it occurs only in bacterial and fungal sinusitis, and it is reproducible on palpation, which a common cold is not.
And no test settles it. Nothing distinguishes viral from bacterial, routine sinus radiography is discouraged, and three or more clinical findings have similar accuracy to imaging anyway. CT is for recurrent disease, treatment failure, or suspected extrasinus involvement.
His second emphasis marker: the yellow highlight. Talking through the epidemiology he said — “maybe it’s highlighted in yellow and I’m trying to make a specific point about this, maybe like in the last lecture when something was highlighted in yellow and I said it was important to remember” — and then walked the class to the answer he wanted: the commonest pathogen in otitis media is viral, and so is the commonest pathogen in sinusitis. When a slide of his has something highlighted in yellow, that is deliberate. It sits alongside his other marker, saying a thing three times.
He called acute sinusitis “one of your bread-and-butter diagnoses … something you’re going to see all the time, especially in primary care”, and was blunt about the reflex to treat: “everybody says oh no it’s bacterial and everybody’s going to go home with a course of antibiotics — is that the right thing to do? No, of course not. We have to be good stewards of our antibiotics.”
Discharge color is the thing patients trust most and the thing that helps least. Yellow or green is explicitly the least useful. Clear may be viral or allergic. Yellow and putrid suggests bacterial. Black suggests fungus. Rust-colored may be S. pneumoniae.
Allergy does not cause an “-itis”. It creates the perfect environment for infection. Many patients who believe they have sinusitis have allergic disease.
One objective has no slide. The syllabus lists rhinitis as allergic and vasomotor; the deck covers allergic rhinitis in full and never mentions vasomotor rhinitis. It is flagged here rather than quietly omitted — it is a named objective with no lecture content behind it.
3.1 · Sinusitis, acute through chronic
Acute sinusitis (rhinosinusitis) Routine
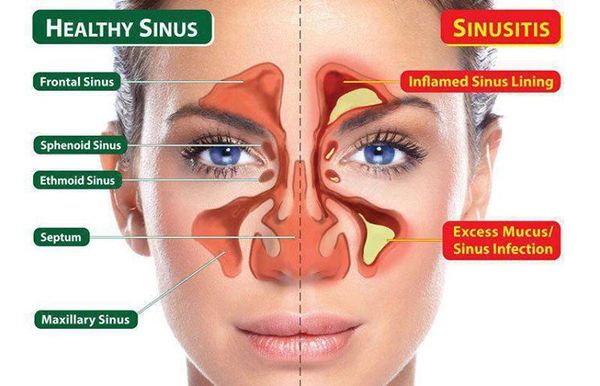
Gives itself away by: Under 4 weeks · 90–98% VIRAL · facial pain that is worse bending forward
- Presentation & who gets it
- Symptomatic inflammation of one or more paranasal sinuses lasting under four weeks, from impaired drainage and retained secretions, with obstruction and/or facial pain, pressure or fullness. “Rhinosinusitis” is the preferred term because rhinitis and sinusitis usually coexist. Affects 1 in 8 adults — over 30 million a year in the United States — and is the fifth leading reason antibiotics are prescribed. Nasal drainage and congestion, rhinorrhea, postnasal drip, headache. Pain localizes to the involved sinus and is worse bending over or lying flat.
- Pain / discharge / key finding
- Pressure; frank pain suggests bacterial · Rhinorrhea, postnasal drip · Pain worse bending forward
- Testing & cause
- No diagnostic test distinguishes viral from bacterial, and none is indicated routinely. Routine sinus radiography is discouraged: three or more clinical findings have similar accuracy to imaging, and imaging cannot separate the two causes anyway. Limited coronal CT for recurrent infection or failure to respond, or if signs suggest extrasinus involvement. Viral causes rhinovirus, parainfluenza, influenza; bacterial S. pneumoniae, nontypable H. influenzae and — in children — M. catarrhalis. Immunocompromised: fungal — Rhizopus, Mucor, occasionally Aspergillus. Nosocomial cases are polymicrobial with S. aureus and gram-negative bacilli.
- First-line treatment
- Most improve WITHOUT antibiotics. Symptomatic: decongestants, non-steroidal anti-inflammatories, nasal or sinus lavage, intranasal steroids, neti pot, saline sprays. If bacterial: amoxicillin/clavulanate. Penicillin allergy: doxycycline, or an antipneumococcal fluoroquinolone such as moxifloxacin. If influenza, oseltamivir for five days in anyone over 13. Medical treatment fails → ENT referral for surgery.
- Education & prognosis
- Tell the patient what they have, how they got it, how to use the medicine or device, and — if referring — to which specialty. Most cases are viral and settle without antibiotics.
Slides 9–27
Bacterial sinusitis — the features that suggest it Routine
Gives itself away by: Double worsening · ≥10 days · UNILATERAL tooth or facial pain
- Presentation & who gets it
- Only 0.5–2% of viral episodes develop a bacterial superinfection, so these features are what raise the possibility: worsening after 5–6 days of initial improvement; persistent symptoms for 10 days or more; persistent purulent discharge; UNILATERAL upper tooth or facial pain; unilateral maxillary tenderness; fever; altered mental status.
- Pain / discharge / key finding
- YES — and REPRODUCIBLE on palpation · Purulent, sometimes putrid · UNILATERAL maxillary tenderness
- Testing & cause
- PAIN is the big distinguishing factor — it occurs only in bacterial and fungal sinusitis, and it is reproducible on palpation, which a common cold is not. Fever above 100.4°F and severe pain point bacterial or fungal — check the patient is not on an antipyretic first. Discharge color is largely unhelpful: yellow or green is the least useful; clear may be viral or allergic; yellow AND putrid suggests bacterial; BLACK suggests fungus; rust-colored may be S. pneumoniae.
- First-line treatment
- Symptomatic treatment plus antibiotics — amoxicillin/clavulanate first line.
- Education & prognosis
- The color of the discharge is the thing patients most expect to be diagnostic, and it is the thing that matters least.
Slides 16–19, 23
Sinusitis with urgent features Emergent
Gives itself away by: Diplopia · periorbital swelling or erythema · altered mental status
- Presentation & who gets it
- The lecture names these separately as symptoms requiring urgent attention in a patient with sinusitis: visual disturbance, especially diplopia; periorbital swelling or erythema; altered mental status.
- Pain / discharge / key finding
- YES · Any · Diplopia, periorbital swelling, confusion
- Testing & cause
- Sinus CT if signs suggest extrasinus involvement. These are the findings that say the disease has left the sinus.
- First-line treatment
- Urgent evaluation and imaging rather than another course of symptomatic treatment.
- Education & prognosis
- The orbit sits next door to the ethmoid sinus. Eye signs in a sinusitis patient are the ones that change the plan.
Slides 17, 21
Chronic bacterial sinusitis Urgent
Gives itself away by: Over 12 weeks · constant congestion with flares · impaired mucociliary clearance
- Presentation & who gets it
- Sinusitis lasting more than twelve weeks. The mechanism is impaired mucociliary clearance causing REPEATED infections rather than one persistent infection. Constant nasal congestion and sinus pressure, with periods of increased severity.
- Pain / discharge / key finding
- Pressure, with flares · Constant congestion · >12 weeks
- Testing & cause
- Sinus CT defines extent, detects an underlying anatomic defect or obstruction, and assesses response. Endoscopy-derived tissue for histology and culture should guide treatment. Consider full blood count with differential and IgE.
- First-line treatment
- Repeated antibiotic courses, often 3–4 weeks at a time — oral steroids plus two weeks of amoxicillin/clavulanate is the stated regimen. Adjuncts: intranasal glucocorticoids, sinus irrigation. Refer to ENT for surgical evaluation and to allergy for skin testing.
- Education & prognosis
- It is a drainage problem as much as an infection, which is why it keeps coming back and why surgery enters the conversation.
Slides 28–29
Chronic fungal sinusitis Urgent
Gives itself away by: Aspergillus · a fungus ball · allergic form has peanut-butter mucus
- Presentation & who gets it
- Noninvasive disease in immunocompetent hosts, typically Aspergillus and dematiaceous molds. Recurrence is common. The allergic form is seen in patients with nasal polyps and asthma and presents as pansinusitis with thick, eosinophil-laden mucus the consistency of peanut butter.
- Pain / discharge / key finding
- Variable · Peanut-butter mucus in the allergic form · Fungus ball on imaging
- Testing & cause
- Imaging and endoscopy. Unilateral disease with a mycetoma (fungus ball) is the characteristic finding.
- First-line treatment
- Mild indolent disease is cured by endoscopic surgery WITHOUT antifungals. A fungus ball is treated surgically — and with antifungals only if bony erosion has occurred.
- Education & prognosis
- The surprise here is that most of it is treated surgically rather than with drugs.
Slides 30
Also tested
- Invasive fungal sinusitis. Black necrotic mucosa in a diabetic or immunocompromised patient indicates angioinvasive fungal disease; because the blood supply is destroyed, surgical debridement is needed alongside systemic therapy and control of the diabetes.
- Impaired mucociliary clearance. The cilia can no longer move the mucus blanket out of the sinus: chronic inflammation damages the cilia and thickens the mucus, so secretions stagnate and invite repeated infection.
- Orbital cellulitis from sinusitis. Periorbital swelling with painful restricted eye movement and diplopia means infection has crossed the paper-thin lamina papyracea from the ethmoid sinus; it needs urgent imaging and admission for intravenous antibiotics.
- Sinusitis with immunosuppression. Management needs earlier imaging and a lower threshold for invasive fungal disease, because Aspergillus and the mucormycetes can invade blood vessels and cause tissue infarction within days; inspect the nasal mucosa for necrotic tissue.
- Sinusitis pain on bending. Bending forward increases the hydrostatic pressure of the fluid within the obstructed sinus against inflamed mucosa; postural worsening is characteristic of sinusitis.
- Bacterial rhinosinusitis. Symptoms persisting ten days or more without improvement help identify the small bacterial minority of rhinosinusitis (90 to 98 percent is viral). Amoxicillin-clavulanate twice daily is first line, as clavulanate covers beta-lactamase producing Haemophilus influenzae and Moraxella catarrhalis plus pneumococcus.
- Ethmoid sinusitis and the orbit. The lamina papyracea, the medial orbital wall separating ethmoid from orbit, is paper-thin, the thinnest bone in the orbit. Ethmoid sinusitis is therefore the commonest sinus source of orbital cellulitis, particularly in children.
- Sinusitis in children. The same criteria apply as in adults, so ten days of purulent discharge without improvement indicates bacterial sinusitis. Children have maxillary and ethmoid sinuses from birth, and ethmoid proximity to the orbit makes recognition important.
- Fever in suspected bacterial sinusitis. Before accepting fever as a sign, confirm that the patient is not taking an antipyretic.
- Viral share of rhinosinusitis. Ninety to ninety-eight percent of acute rhinosinusitis is viral.
- Sinus tenderness. Absence of tenderness on pressing the maxillary and frontal areas argues against bacterial infection: that pain is reproducible on palpation, whereas a common cold's is not.
- Early, mild rhinosinusitis. With afebrile course, clear discharge and pressure not reproduced on palpation, use symptomatic treatment alone, since most acute rhinosinusitis is viral and improves without antibiotics.
- Fungus ball. In an immunocompetent patient with unilateral sinus disease and no bony erosion, surgery alone is the treatment. Antifungals are added only if bony erosion has occurred.
- Sinusitis with orbital signs. Diplopia and periorbital swelling are named urgent features, so the priority is urgent computed tomography.
- Rhinosinusitis duration. Acute is under four weeks and chronic is beyond twelve weeks, with subacute occupying the interval between four and twelve.
- Chronic rhinosinusitis. Continuous symptoms beyond 12 weeks define it; repeated antibiotic courses treat the flares without changing the underlying problem of impaired mucociliary clearance with persistent inflammation.
- Sinusitis in immunocompromised patients. Fungi are the organisms that cause it.
- Nasal discharge color. Yellow or green is the least helpful color for deciding on antibiotics; color barely helps, and only black, rust or pure clear carry any signal.
- Bacterial sinusitis. Double worsening, unilateral pain reproduced on palpation and fever together point to a bacterial cause; start amoxicillin with clavulanate.
- Sinusitis with altered mental status. Altered mental status, like diplopia and periorbital swelling, is an urgent feature; it indicates the infection may have crossed into the cranial cavity (meningitis, epidural or subdural collection, brain abscess), so urgent evaluation for intracranial extension with imaging and admission is needed.
- Imaging in chronic sinusitis. Sinus computed tomography contributes extent, anatomy and response.
- Acute sinusitis risk factors. Smoking is a named risk factor, alongside chronic allergies, immunocompromise and anatomical defects.
- Counseling a patient referred for persistent sinus disease. Tell the patient four elements: diagnosis, cause, treatment and referral.
3.2 · The septum
Deviated septum Routine
Gives itself away by: One passage smaller than the other · congenital or traumatic
- Presentation & who gets it
- The nasal septum is significantly displaced to one side, making one air passage smaller. Congenital or traumatic. Ranges from congestion — through blockage of the ostia — to anosmia. In severe forms: obstructive sleep apnea, snoring, facial pain and recurrent nosebleeds.
- Pain / discharge / key finding
- No, unless severe · Congestion; recurrent bleeds · One passage smaller
- Testing & cause
- Clinical, with a nasal speculum; CT where needed.
- First-line treatment
- Surgery — septoplasty, by an otorhinolaryngologist.
- Education & prognosis
- The recurrent nosebleeds and the snoring are what usually bring the patient in, not the deviation itself.
Slides 32–36
Perforated septum Routine
Gives itself away by: Intranasal steroid or COCAINE use · chronic ischemia
- Presentation & who gets it
- A perforation through the nasal septum. Congenital or traumatic, but many are from intranasal steroid use or cocaine use, both by chronic ischemia. Rarely granulomatosis with polyangiitis (Wegener’s), a vascular autoimmune disease, may cause nasal deformity. Rarely, secondary syphilis — seldom seen now.
- Pain / discharge / key finding
- No · Crusting, whistling · Visible perforation
- Testing & cause
- Physical examination, possibly with CT.
- First-line treatment
- Treat the underlying cause and it may grow back; otherwise septoplasty.
- Education & prognosis
- The drug history is the diagnosis here — ask about both prescribed nasal steroids and cocaine.
Slides 37–40
Septal hematoma Urgent
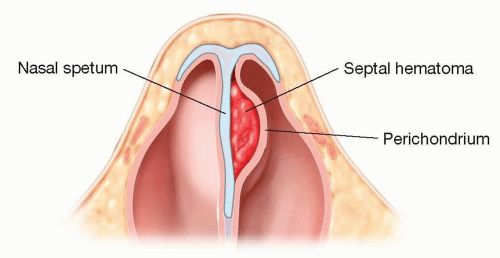
Gives itself away by: Blood between septum and perichondrium · after trauma · drain it
- Presentation & who gets it
- A hematoma between the nasal septum and the perichondrium or mucosal epithelium. Usually secondary to trauma; other causes are bleeding disorders, cocaine, foreign body and medications. Associated with nasal fracture — look for it in every nasal injury.
- Pain / discharge / key finding
- YES · Obstruction · Swelling between septum and perichondrium
- Testing & cause
- Inspection with a nasal speculum. It is one of the four things that must be excluded before a nasal fracture can be managed without imaging.
- First-line treatment
- Drainage via intranasal incision under general anesthesia.
- Education & prognosis
- The same lesson as the auricular hematoma in Lecture 15: cartilage separated from its blood supply does not survive.
Slides 41–43
Also tested
- Auricular laceration. A full-thickness break in the skin and cartilage, it is an open wound rather than a swelling.
- Septal perforation from topical agents. The anterior septum has thin mucosa over cartilage with no other blood supply, so chronic ischemia from prolonged intranasal steroid (especially sprayed at the septum) or cocaine can perforate it.
- Septal deviation. An asymptomatic deviation needs no treatment. It is treated only when it causes obstruction, recurrent epistaxis from the drier open side, obstructive sleep apnea, snoring or facial pain.
- Timing of nasal fracture reduction. A displaced fracture is straightened once swelling settles, within about two weeks. Swelling obscures bony position, and the bones begin to unite after roughly two weeks.
- Saddle nose deformity. Septal cartilage has no blood supply of its own and depends on perichondrium. A hematoma strips it away, causing avascular necrosis and collapse of the dorsum, which is why drainage is urgent rather than elective.
- Undrained septal hematoma. The concern is cartilage damage, because the collection separates cartilage from its blood supply.
- Septal perforation. Management is to treat the cause; otherwise, septoplasty.
3.3 · Epistaxis
Epistaxis — anterior Urgent
Gives itself away by: Kiesselbach’s plexus · 90% of nosebleeds · commonest cause is the patient’s finger
- Presentation & who gets it
- A common emergency department complaint, most cases before age 10 or between 45 and 65, with a winter predominance. The commonest cause is trauma — from the patient’s finger. Chronic dry nose is a risk factor. Anterior bleeds are by far the commonest: 90% arise in the vascular watershed of the nasal septum — Kiesselbach’s plexus.
- Pain / discharge / key finding
- No · Frank blood, anteriorly · Kiesselbach’s plexus
- Testing & cause
- Airway, breathing, circulation first — bleeding can be severe. Normal appearance, vital signs and respiratory function is the reassuring picture. History: tumors, coagulation disorders personal and family, recent trauma or surgery, medications — aspirin, warfarin, clopidogrel, intranasal glucocorticoids, and cirrhosis, HIV or intranasal cocaine. A prothrombin time with INR is NOT a routine test — order it for the anticoagulated patient. Hematocrit and type and crossmatch in massive or prolonged hemorrhage, with two large-bore intravenous lines.
- First-line treatment
- Initial tamponade, and patients can do it themselves: blow the nose to clear clots → spray with oxymetazoline → pinch the alae against the septum continuously for 10 minutes. Also: sit up and lean forward at the waist so blood is not swallowed, a cotton pledget in the nostril, spit out blood in the pharynx, cold compress on the bridge. Then nasal tampons, gauze packing, balloon catheters, thrombogenic foams and gels.
- Education & prognosis
- Teach these maneuvers for use at home. And DO NOT BLOW THE NOSE afterwards.
Slides 45–51
Epistaxis — posterior Emergent

Gives itself away by: Sphenopalatine artery · significant hemorrhage · ASPIRATION risk
- Presentation & who gets it
- Arises most commonly from the posterolateral branches of the sphenopalatine artery, but may arise from branches of the carotid. Results in significant hemorrhage.
- Pain / discharge / key finding
- No · Heavy; blood in the pharynx · Sphenopalatine artery
- Testing & cause
- You must determine whether the bleed is anterior, posterior, or both.
- First-line treatment
- As for anterior bleeding, escalating to packing and ENT involvement.
- Education & prognosis
- Posterior bleeds carry a higher risk because of ASPIRATION and subsequent infection — that is why the distinction is made.
Slides 45–46
Also tested
- Epistaxis on anticoagulation. Clotting studies are not routine in epistaxis but are indicated in anticoagulated patients; correct the anticoagulation as well as treating the nose, or the systemic reason for bleeding is left unaddressed.
- Brisk epistaxis with hemodynamic compromise. Dizziness and confusion mean an intravenous line and fluids come first, since resuscitation precedes control of the bleeding point. Bilateral bleeding with no visible source suggests a posterior (sphenopalatine artery) bleed.
- Epistaxis first aid. Pinch the soft part (alae) continuously for ten minutes, leaning forward. The bleeding point in 90 percent of cases is Kiesselbach plexus on the anterior septum; leaning forward stops blood tracking into the pharynx.
- Epistaxis with clots. Blow out clots first, since retained clot holds the vessel open; then spray a topical vasoconstrictor such as oxymetazoline and pinch the alae continuously for ten minutes.
- Childhood anterior epistaxis. Ninety percent of nosebleeds are anterior, from Kiesselbach plexus; digital trauma is the commonest cause and dry winter air worsens it. Short bleeds stopped by pressure in a well child are managed conservatively with humidification and behavior change.
- Epistaxis blood tests. Clotting studies (prothrombin time and international normalized ratio) are not routine for epistaxis. They are reserved for anticoagulated patients or those with other evidence of a bleeding tendency.
- After epistaxis is controlled. The patient must avoid blowing the nose.
- Positioning in epistaxis. The patient should sit up and lean forward so blood is not swallowed.
- Preventing recurrent epistaxis. A chronic dry nose is a named risk factor, so humidify and keep the nose moist.
- Epistaxis on anticoagulants. Prolonged heavy bleeding in an anticoagulated patient calls for a clotting study, crossmatch and count; the clotting study is indicated because of the anticoagulation.
- Recurrent nosebleeds in children. The commonest cause is trauma from the child's own finger, with a chronic dry nose as a risk factor.
3.4 · Trauma and foreign bodies
Nasal fracture Urgent
Gives itself away by: Contusion and tenderness over the bridge = fracture · commonest facial fracture site
- Presentation & who gets it
- From trauma. Suspect other injuries — orbital and midface fractures. Associated with septal hematoma. The nasal bridge is the commonest site. Examination: palpate for tenderness, crepitus and abnormal movement, and inspect with a nasal speculum.
- Pain / discharge / key finding
- YES · Epistaxis · Tenderness and crepitus over the bridge
- Testing & cause
- X-rays are NOT needed if all four hold: tenderness and swelling isolated to the bony bridge; the patient can breathe through each naris; the nose is straight, with no septal deviation; and there is no septal hematoma. If any fails, plain films.
- First-line treatment
- Initial treatment is ice and head of bed elevated.
- Education & prognosis
- The four criteria are the useful thing to carry — they decide imaging at the bedside.
Slides 56–58
Nasal foreign body Urgent
Gives itself away by: UNILATERAL foul-smelling purulent discharge in a young child
- Presentation & who gets it
- Commonest in young children. Most often on the floor of the nasal passage just under the inferior turbinate, or superiorly just in front of the middle turbinate. Unilateral purulent and foul-smelling nasal discharge in a young child strongly suggests it.
- Pain / discharge / key finding
- Variable · UNILATERAL, purulent, FOUL-SMELLING · Object visible under a turbinate
- Testing & cause
- Visualization establishes the diagnosis. Imaging is rarely needed.
- First-line treatment
- Removal — instrument chosen by what the object is: forceps for graspable objects, a wire loop, right-angle hook or curette for round smooth ones, suction for smooth or free-floating beads, beans, magnets or batteries. Get help — refer to ENT.
- Education & prognosis
- A one-sided smelly discharge in a toddler is a foreign body until proven otherwise, not sinusitis.
Slides 53–55
Also tested
- Nasal foreign body in a calm child. The first attempt is a parent-delivered positive pressure blow: the parent seals the child's mouth with their own and blows while the unaffected nostril is occluded. It is atraumatic and needs no instruments.
- Minor nasal trauma. When tenderness is confined to the bony bridge, each nostril is patent, the nose is straight without septal deviation, and there is no septal hematoma, use ice and elevation without radiography. Treatment of an undisplaced fracture is symptomatic.
- Unilateral foul nasal discharge in a child. Unilateral, foul-smelling purulent discharge in a young child is a retained nasal foreign body until proven otherwise. Direct visualization of the nasal vestibule makes the diagnosis and allows removal.
- Nasal trauma imaging. Imaging can be omitted only when all four reassuring criteria are met. A deviated nose or a blocked nostril fails them, so radiography is indicated and the nose is assessed for reduction.
- Button battery in the nose. Urgent removal is required. The battery generates current across moist mucosa, producing hydroxide ions and liquefactive necrosis that can perforate the septum within hours, making it the one nasal foreign body treated as a true emergency.
- Nasal injury check. Before discharge, inspect and feel the septum for a boggy swelling. A septal hematoma is easy to miss because attention goes to the bridge, yet it destroys cartilage within days if not drained.
- Clear rhinorrhea after trauma. Clear nasal fluid after significant facial or head trauma, especially with bilateral periorbital bruising, suggests a cerebrospinal fluid leak from a skull base fracture through the cribriform plate. It is a neurosurgical problem with a risk of meningitis.
- Nasal foreign body diagnosis. Direct visualization establishes the diagnosis; imaging is rarely needed.
- Nasal fracture. The external nose is deviated and swollen with blood at the nares: deformity, not just bleeding.
- Nasal trauma imaging. When swelling and tenderness are confined to the bony bridge, breathing is free through each nostril, the nose is straight and there is no septal hematoma (all four criteria met), no imaging is required.
3.5 · Polyps and rhinitis
Nasal polyps Urgent
Gives itself away by: Gray, glistening masses · anosmia · asthma and aspirin sensitivity
- Presentation & who gets it
- Abnormal, gray, glistening masses filled with inflammatory material in the nasal cavity or paranasal sinuses. Large or extensive polyps cause congestion or blockage, thick discharge and ANOSMIA. Frequently associated with chronic rhinosinusitis, asthma and aspirin sensitivity — aspirin-exacerbated respiratory disease. In children they occur with chronic sinusitis, allergic rhinitis, cystic fibrosis or allergic fungal sinusitis. From the slide that is an image of a list: associated conditions include bronchial asthma 20–50%, cystic fibrosis 5–44%, allergic fungal sinusitis 85%, aspirin intolerance 8–20%, alcohol intolerance 50%, Churg-Strauss 50%, primary ciliary dyskinesia, Young syndrome and NARES 20%.
- Pain / discharge / key finding
- No · Thick discharge · Gray glistening masses; ANOSMIA
- Testing & cause
- Diagnosed clinically by their appearance on nasal speculum or rhinoscopy, and identifiable on CT. Chloride sweat test if cystic fibrosis is a concern; full blood count with differential, IgE and IgA; consider a nasal smear for eosinophils; CT for extent or surgical planning.
- First-line treatment
- Medical: non-drowsy oral antihistamine (loratadine, fexofenadine, cetirizine, levocetirizine), leukotriene inhibitor at night (montelukast, zafirlukast), intranasal or oral steroids, intranasal ipratropium, immunotherapy, decongestants with caution. Surgery gives only temporary relief — they recur within months to years.
- Education & prognosis
- Evaluate EVERY child with benign multiple nasal polyposis for cystic fibrosis and asthma. The deck gives that its own slide.
Slides 59–65
Allergic rhinitis Routine
Gives itself away by: CLEAR discharge from BOTH nostrils · bluish, boggy mucosa
- Presentation & who gets it
- Rhinorrhea secondary to allergy: the body treats the allergen as foreign and releases chemokines causing hypermucosal production. Extremely common and rising.
- Pain / discharge / key finding
- No · CLEAR, BILATERAL · Bluish, boggy mucosa
- Testing & cause
- Clinical — mostly the history. Findings: clear discharge from each nostril, a bluish hue to the nasal mucosa, edematous mucosa, and with or without nasal polyps.
- First-line treatment
- 80% of patients end up on two or more allergy medicines. Non-drowsy oral antihistamine by day and a drowsy one at night if needed; leukotriene inhibitor at night; intranasal steroids with caution in chronic use; immunotherapy; intranasal ipratropium; decongestants with caution in chronic use and in high blood pressure.
- Education & prognosis
- Allergy does not cause “-itis” itself — it creates the perfect environment for infection. Many patients who think they have sinusitis have allergic disease.
Slides 13, 26, 66–68
Also tested
- Adenoidal hypertrophy. Chronic mouth breathing, snoring and hyponasal speech with bilateral nasal obstruction and no discharge indicate it; the bilateral, discharge-free pattern distinguishes it from a foreign body or infection.
- Vasomotor rhinitis. Clear bilateral rhinorrhea triggered by cold air, strong smells and alcohol, with no itch and negative allergy testing, is driven by autonomic dysregulation rather than an immunoglobulin E response.
- Conductive anosmia. Polyps, chronic inflammation or marked mucosal swelling block airflow to the olfactory epithelium, so receptors are intact but never reached; treating the obstruction can restore smell.
- Allergic rhinitis treatment. About 80 percent of patients need two or more agents because different symptoms are driven by different mediators. A typical combination is an antihistamine with an intranasal corticosteroid, adding a leukotriene inhibitor at night, and immunotherapy if drugs are insufficient.
- Rebound congestion. Prolonged topical decongestant use worsens congestion: receptors downregulate and vessels dilate more each time the drug wears off, prompting more frequent use. These sprays carry a three-to-five-day limit.
- Nasal polyps after surgery. Recurrence is expected, because polyps arise from ongoing mucosal inflammation and surgery gives only temporary relief. Medical treatment of the underlying inflammation continues afterwards.
- Using an intranasal corticosteroid. Aim the spray laterally toward the turbinate, away from the septum. Repeated delivery to the thin mucosa over the septal cartilage, with chronic vasoconstriction there, is a named cause of septal perforation.
3.6 · Neoplasms
Nasopharyngeal carcinoma Emergent
Gives itself away by: Neck mass + diplopia + facial numbness · Epstein-Barr virus
- Presentation & who gets it
- The predominant tumor arising in the nasopharynx. Rare in the United States and Western Europe; endemic in Southern China including Hong Kong, Southeast Asia, North Africa, the Middle East and the Arctic. Two- to threefold more common in males. Associated with Epstein-Barr virus, human papillomavirus and smoking, and with high-salt diets, Chinese herbs, rancid butter and sheep fat.
- Pain / discharge / key finding
- Headache · May be bloody · Neck mass + cranial nerve signs
- Testing & cause
- Presents with headache, diplopia, facial numbness and a mass in the neck. Referral to ENT and endoscopic guided biopsy of the primary tumor.
- First-line treatment
- Oncological management following biopsy (ENT).
- Education & prognosis
- The combination that should prompt referral is a neck mass with cranial nerve symptoms, not nasal symptoms alone.
Slides 69–70
Benign nasal neoplasms Routine
Gives itself away by: Same as skin — the dermatology lesions, on the nose
- Presentation & who gets it
- The lecture defers to the dermatology block: warts, freckles, hemangioma, port-wine stain and the rest behave on the nose as they do elsewhere.
- Pain / discharge / key finding
- No · None · As the equivalent skin lesion
- Testing & cause
- As for the equivalent skin lesion.
- First-line treatment
- As for the equivalent skin lesion — see the dermatology lectures.
- Education & prognosis
- Worth knowing only as the counterpart to the malignant list; the detail lives in the dermatology material.
Slides 71
Also tested
- Nasopharyngeal carcinoma and sex. Incidence is two to threefold higher in males.
4 · Neoplasms and Neck Masses
Instructional Objectives
DISORDERS OF THE EARS, NOSE, THROAT AND NECK — Neck Masses and Neoplasms
- Define the major and minor triangles of the neck
- Identify the lymph nodes of the neck area
- Compare and contrast the etiologies, epidemiology, risk factors, clinical
manifestations, differential diagnosis, diagnostic testing (including ordering and
interpretation), management (acute and chronic, including applicable rehabilitative and
palliative care), appropriate referrals, patient education, and prognosis of the following
neck masses and neoplasms:
- Common neck masses.
- Vascular tumors seen in the neck.
- Benign neoplasms of the neck
- Malignant neoplasms
- Primary
- Secondary
- Identify medical care strategies for disorders of the neoplasms and neck masses in the lecture topic list for the following populations: 1. adolescent · 2. adult · 3. elderly
This lecture has no recording. Everything below comes from the slides. Where sections 1 to 3 also carry a point their lecturer made out loud, this one carries only what is written.
4.1 · The triangles and the nodes
The first two objectives are pure anatomy, and no disease row carries them, so they go first.
The neck is bounded by the mandible above and the clavicle below, and the sternocleidomastoid divides it into an anterior and a posterior triangle. Each is then subdivided by the omohyoid and digastric muscles.
| Triangle | Boundaries | What is in it |
|---|---|---|
| POSTERIOR — sternocleidomastoid in front, trapezius behind, clavicle below; divided by the omohyoid | ||
| Occipital | Upper part of the posterior triangle | Floor from above down: semispinalis capitis, splenius capitis, levator scapulae, scalenus medius. The spinal accessory nerve crosses the floor to pass deep to trapezius; the cutaneous nerves of the neck run in the deep fascia over it. |
| Supraclavicular | Above the middle of the clavicle | Terminal subclavian artery; roots, trunks and divisions of the brachial plexus; thyrocervical trunk branches; tributaries of the external jugular vein. The cupola of the pleural cavity lies deep to its contents. |
| ANTERIOR — sternocleidomastoid behind, midline in front, mandible above | ||
| Submental | Anterior belly of digastric, midline, hyoid bone | Floor formed by mylohyoid. |
| Digastric (submandibular) | Mandible above, the two bellies of digastric | Stylohyoid, mylohyoid and hyoglossus muscles; submandibular gland; hypoglossal nerve; facial vessels. |
| Carotid | Sternocleidomastoid behind, posterior belly of digastric above, omohyoid below | Carotid arteries, internal jugular vein, vagus nerve. |
| Muscular | Omohyoid above, sternocleidomastoid below, midline in front | Thyroid, parathyroid, larynx, trachea, esophagus, thyroid and cricoid cartilage. |
Lymphatic drainage. Superficial nodes are named for where they sit. Occipital, retroauricular and parotid nodes drain the scalp, auricle and middle ear; submandibular nodes drain the face, sinuses, mouth and tongue; retropharyngeal nodes — not truly superficial — take lymph from the deeper structures of the head including the upper pharynx. All of them drain into the deep cervical nodes, and two of those are worth naming: jugulodigastric nodes drain the palatine tonsil, and juguloomohyoid nodes drain the tongue. The deep cervical chain empties into the thoracic duct on the left (at the junction of the left internal jugular and left subclavian veins) or the right lymphatic duct on the right.
Also tested
- Nodal level in neck metastasis. The involved nodal level predicts where the primary is likely to be, because each region drains to a predictable group: jugulodigastric to the tonsil, juguloomohyoid to the tongue, submandibular to the face, sinuses and mouth.
- Jugulodigastric node. This deep cervical node drains the palatine tonsil, so tonsillitis produces a tender node high in the jugular chain just below the angle of the jaw; it is the node examined in a sore throat.
- Posterior triangle nerve injury. The spinal accessory nerve crosses the muscular floor of the occipital triangle before passing deep to trapezius, leaving it superficial and exposed; injury denervates trapezius and causes a painful drooping shoulder.
4.2 · When to think malignancy
Most neck masses under 40 are inflammatory — with the exception of Hodgkin lymphoma. The lecture then gives a list of features that should move you the other way.
Think malignancy when: there is no infectious origin · duration over 2 weeks · size over 1.5 cm · firm, non-cystic, non-tender, with little or no mobility · age over 40 · tobacco and alcohol use · ulceration. Also family history, previous malignancy, immunocompromise and HIV.
And four rules of thumb from the same slide: a mass present for years is usually benign (lipoma or cyst); one growing rapidly is usually infectious if there are other symptoms and lymphoma if there are not; fluctuance means cystic; pulsatile or a bruit means vascular.
The differential, as KITTENS. K congenital — branchial cleft cyst, lymphatic malformation, teratoma, dermoid cyst, thyroglossal duct cyst, external laryngocele. I infectious and iatrogenic — bacterial or viral lymphadenitis, tuberculosis, cat-scratch fever, syphilis, atypical mycobacteria, persistent generalized lymphadenopathy, mononucleosis, sebaceous cyst, deep inflammation or abscess. T toxins and trauma — hematoma. E endocrine — thymic cyst, thyroid hyperplasia, aberrant thyroid tissue, parathyroid cyst. N neoplastic — metastatic or regional malignancy, thyroid neoplasm, lymphoma, hemangioma, salivary gland tumor, vascular tumor, neurogenic tumor, lipoma. S systemic — granulomatous disease, laryngocele, plunging ranula, Kawasaki disease.
The other framework, from slide 17, splits on age first. Congenital divides by position — lateral gives branchial cleft cyst, lymphadenopathy and cystic hygroma; midline gives thyroglossal duct cyst. Adult divides into inflammatory (viral adenopathy; bacterial — strep, staph, Ludwig angina, actinomyces, sialadenitis, tubercular scrofula) and neoplastic (metastatic to cervical nodes from a head and neck primary or melanoma; or primary — thyroid, lymphoma).
What to order. A trial of antibiotics is common, but a mass that persists gets worked up. Contrast computed tomography distinguishes vascularity and solid from cystic, and evaluates for metastasis and staging — but avoid iodine contrast if thyroid cancer is suspected, because it compromises later radioiodine treatment. Fine needle aspiration biopsy is the standard of care: it separates neoplasm from inflammation and carcinoma from lymphoma, and needs a minimum of four separate passes. Then, as indicated: computed tomography angiography for pulsatile masses, magnetic resonance imaging, positron emission tomography, excisional biopsy, and labs — full blood count with differential, comprehensive metabolic panel, HIV, Epstein-Barr virus and cytomegalovirus, erythrocyte sedimentation rate and C-reactive protein, autoimmune panel, thyroid and parathyroid panels, tuberculin skin test, cat scratch and toxoplasmosis titres. Refer early if the mass is suspicious, and especially if it persists after treatment.
Also tested
- Imaging a suspected thyroid cancer. Use ultrasound, which characterizes nodules without radiation and guides aspiration. Avoid iodine-containing contrast computed tomography, because the iodine load saturates the thyroid and compromises subsequent radioiodine treatment.
- Neck mass features suggesting malignancy. These are no infectious origin, duration over two weeks, size greater than 1.5 centimeters, firm, non-cystic, non-tender with little or no mobility, age over 40, and tobacco and alcohol use. Size alone is not diagnostic.
- Malignant node features. An immobile, firm, non-tender cervical node raises concern for malignancy: immobility suggests tumor fixation to surrounding structures, firmness suggests solid tissue, and non-tenderness points away from inflammation.
- Laboratory workup of a persistent neck mass. It includes full blood count, HIV and Epstein-Barr serology, inflammatory markers and thyroid panels; the panel is broad because the differential is broad.
- Positron emission tomography. It measures metabolic uptake of tagged glucose, higher in cancer and inflammation, so a positive result cannot by itself establish cancer.
- Neck mass persisting after antibiotics. Failure of an antibiotic trial is the point to refer to a specialist now rather than prescribe another course, because early and aggressive treatment is needed in some neoplastic conditions.
- Fluctuance in a neck mass. A soft mass with a fluid wave transmits pressure as a fluid would, so it suggests a cystic lesion containing liquid rather than solid tissue. Other rules of thumb: pulsatility means vascular, years of stability means benign, rapid growth means infection or lymphoma.
- Rapidly growing neck mass. Rapid growth is usually infectious when other infective symptoms accompany it and lymphoma when they do not, as with night sweats and weight loss instead; lymphoma is also the noted exception to the rule that masses under 40 are usually inflammatory.
- Neck lump with an obvious infective context. Reactive adenopathy is expected in the first days of an infection and regresses in one to two weeks; duration over two weeks is what appears on the malignancy list, so treat the infection and reassess in two weeks.
- Painless enlarging node under age 40. Most neck masses under 40 are inflammatory, but a painless, firm, enlarging supraclavicular node with no infection suggests lymphoma, with Hodgkin lymphoma the named exception.
4.3 · Congenital neck masses
Branchial cleft cyst Routine
Gives itself away by: LATERAL neck · anterior border of the sternocleidomastoid · swells after an upper respiratory infection
- Presentation & who gets it
- Failure of the pharyngobranchial ducts to obliterate in fetal development. Presents in late childhood or early adulthood, usually when the cyst becomes infected after an upper respiratory infection: a tender, inflammatory mass at the anterior border of the sternocleidomastoid, with overlying erythema and swelling if infected.
- Pain / where it sits / key finding
- Yes when infected · Lateral — anterior border of sternocleidomastoid · Tender inflammatory mass appearing after an upper respiratory infection
- Testing & cause
- Clinical, with imaging to define the tract. Rule out human papillomavirus-associated squamous cell carcinoma before accepting the diagnosis in an adult — it can present as a cystic neck mass.
- First-line treatment
- Control the infection first, then surgical excision of the cyst and its tract. Avoid incision and drainage unless there is frank abscess — and even then needle aspiration is preferred, because I&D makes the definitive excision harder.
- Education & prognosis
- The cyst was always there; the infection is what made it visible. Excision has to take the whole tract or it recurs.
Slides 22
Thyroglossal duct cyst Routine
Gives itself away by: MIDLINE anterior neck · moves up when the tongue is stuck out or on swallowing
- Presentation & who gets it
- About one third of all congenital neck masses. A midline anterior neck mass, often asymptomatic until it becomes infected after an upper respiratory infection. Location varies — some sit lateral or as low as the thyroid, and those are hard to tell from a branchial cleft cyst.
- Pain / where it sits / key finding
- No unless infected · Midline anterior neck · Moves vertically with swallowing or tongue protrusion
- Testing & cause
- Pathognomonic sign: the mass moves vertically with swallowing or tongue protrusion, which demonstrates its attachment to the hyoid bone. All cysts go for histopathology to exclude thyroid carcinoma.
- First-line treatment
- Antibiotics if infected. Sistrunk operation is the standard: the cyst is excised with a cuff of tissue including the center of the hyoid bone, taking care not to injure the hypoglossal nerves.
- Education & prognosis
- Taking the middle of the hyoid out is not overtreatment — leaving it behind is why these recur.
Slides 23
Dermoid cyst Routine
Gives itself away by: MIDLINE, non-tender, mobile · submental
- Presentation & who gets it
- Arises from epithelium entrapped in deeper tissue during embryogenesis, or by traumatic implantation. Presents as a midline, non-tender, mobile mass in the submental region.
- Pain / where it sits / key finding
- No — non-tender · Midline submental · Mobile midline mass that does NOT move with the tongue
- Testing & cause
- Clinical, with imaging to define the plane.
- First-line treatment
- Surgical excision is the mainstay.
- Education & prognosis
- One of the midline masses — thyroglossal duct cyst is the other, and that one moves with the tongue.
Slides 29
Plunging ranula Routine
Gives itself away by: Slow-growing, painless SUBMENTAL mass · arises from the sublingual gland
- Presentation & who gets it
- A mucocele or retention cyst of the floor of the mouth, presenting as a slow-growing, painless submental mass. It arises from the sublingual gland and is called plunging when it extends through the mylohyoid muscle into the neck.
- Pain / where it sits / key finding
- No — painless · Submental, from the sublingual gland · Extends through mylohyoid into the neck
- Testing & cause
- Clinical, with imaging to show the extent below mylohyoid.
- First-line treatment
- Excision of the sublingual gland — the gland is the source, so removing the cyst alone leaves it to recur.
- Education & prognosis
- "Plunging" is an anatomical statement: it has gone through mylohyoid.
Slides 25
Laryngocele Routine
Gives itself away by: Hoarseness with dyspnea · dilation at the level of the false cord
- Presentation & who gets it
- An abnormal dilation or herniation of the saccule of the larynx. Cough, hoarseness, dyspnea, dysphagia or a foreign body sensation, in any combination. Secondary infection of one is called a laryngopyocele.
- Pain / where it sits / key finding
- No · Larynx — level of the false cord · Smooth dilation at the false cord on laryngoscopy
- Testing & cause
- Laryngoscopy shows a smooth dilation at the level of the false cord. Computed tomography confirms it and shows the extent of the lesion.
- First-line treatment
- Symptomatic disease only: laryngoscopic decompression for small lesions; surgical excision by an external approach for larger ones, taking care not to injure the superior laryngeal nerve; or laser endoscopy.
- Education & prognosis
- The airway symptoms are what force the operation, not the size.
Slides 24
Lymphangioma (cystic hygroma) Routine
Gives itself away by: Soft, doughy, compressible · TRANSILLUMINATES
- Presentation & who gets it
- A congenital malformation of the lymphatic channels, arising because the lymph spaces fail to connect to the rest of the lymphatic system. The mass is soft, doughy, smooth, non-tender and compressible, and transilluminates.
- Pain / where it sits / key finding
- No — non-tender · Anywhere; often posterior triangle · Transilluminates — soft, doughy, compressible
- Testing & cause
- Computed tomography and magnetic resonance imaging confirm the extent and define associated abnormalities such as hemangiomas.
- First-line treatment
- Surgical excision or debulking depending on how far it infiltrates. Sclerotherapy is the alternative.
- Education & prognosis
- Positive transillumination is the bedside finding that separates it from the solid masses.
Slides 26
Hemangioma Routine
Gives itself away by: Red or bluish compressible mass that ENLARGES WITH CRYING or straining · 90% self-resolve
- Presentation & who gets it
- A malformation of vascular tissue. Present in the first few months of life, grows rapidly through the first year, then begins to involute at 18 to 24 months. A red or bluish soft mass, compressible, that increases in size with straining or crying, with or without a bruit.
- Pain / where it sits / key finding
- No · Superficial, any site · Enlarges with crying or straining; red or bluish, compressible
- Testing & cause
- Computed tomography and magnetic resonance imaging.
- First-line treatment
- 90% resolve without any therapy — observation alone. Intervene only for airway compromise, skin ulceration, dysphagia, thrombocytopenia or cardiac failure. First line: propranolol. Second line: systemic corticosteroids, interferon alpha, or surgical laser excision.
- Education & prognosis
- Parents need the growth-then-involution curve explained, or the rapid first year reads as failure of treatment.
Slides 27
Teratoma Urgent
Gives itself away by: Firm neck mass noted at birth or in the first year · calcifications on imaging
- Presentation & who gets it
- Head and neck teratomas account for 3.5% of all teratomas. They originate from pluripotent cells and present as firm neck masses, most commonly noted at birth or within the first year. A large one can cause respiratory compromise or dysphagia.
- Pain / where it sits / key finding
- No · Any; noted at birth · Firm, with calcifications on imaging
- Testing & cause
- Computed tomography and magnetic resonance imaging — calcifications are the clue.
- First-line treatment
- Surgical excision.
- Education & prognosis
- Size is the whole problem here: it is a benign lesion that can obstruct an airway.
Slides 28
Thymic cyst Routine
Gives itself away by: Slow-growing and asymptomatic · painful only if infected · Hassall corpuscles on biopsy
- Presentation & who gets it
- Presents as a slow-growing, asymptomatic mass that may become painful if it is infected.
- Pain / where it sits / key finding
- Only if infected · Lower anterior neck · Hassall corpuscles on biopsy
- Testing & cause
- Magnetic resonance imaging and computed tomography help with the differential. Definitive diagnosis is by biopsy — the presence of Hassall corpuscles.
- First-line treatment
- Surgical excision.
- Education & prognosis
- The histology is the diagnosis; imaging only narrows the list.
Slides 29
Sternocleidomastoid tumor of infancy Routine
Gives itself away by: Firm painless mass WITHIN the sternocleidomastoid · related to congenital torticollis
- Presentation & who gets it
- Related to congenital torticollis. A firm, painless, discrete mass within the sternocleidomastoid muscle that enlarges for 2 to 3 months and then regresses over 4 to 8 months.
- Pain / where it sits / key finding
- No — painless · Within the sternocleidomastoid · Firm discrete mass with congenital torticollis
- Testing & cause
- Clinical.
- First-line treatment
- 80% resolve spontaneously and need only physical therapy to prevent restrictive torticollis. Surgical excision is reserved for persistent cases.
- Education & prognosis
- The natural history is the treatment plan: it gets bigger before it gets better.
Slides 29
Also tested
- Infected branchial cleft cyst. Control the infection first, then excise the cyst and its tract; leaving the tract behind is what causes recurrence.
- Neonatal neck teratoma. A large firm neck mass with calcifications noted at birth is a teratoma, requiring surgical excision because large ones cause respiratory compromise or dysphagia.
- Thyroglossal duct cyst. Vertical movement with swallowing or tongue protrusion is pathognomonic: a persistent tract tethers the cyst to the hyoid, so protruding the tongue pulls the cyst upward.
- Infantile hemangioma. Observation is the default because about 90 percent involute, but airway compromise, skin ulceration, dysphagia, thrombocytopenia or cardiac failure call for intervention; start propranolol, first line for infants without a contraindication.
- Infected congenital neck cyst. Control the infection first, then excise the cyst and its tract; the tract must be removed too, because leaving it behind causes recurrence.
- Branchial cleft cyst. It arises from pharyngobranchial ducts that fail to obliterate during fetal development and presents laterally, at the anterior border of the sternocleidomastoid; that position is the first branch of the congenital differential, lateral against midline.
4.4 · Inflammatory neck masses
Reactive viral lymphadenopathy Routine
Gives itself away by: Commonest cause of cervical lymphadenopathy in CHILDREN · with an upper respiratory infection · regresses in 1–2 weeks
- Presentation & who gets it
- The commonest cause of cervical lymphadenopathy in children, associated with an underlying upper respiratory infection. Commonest pathogens are adenovirus, rhinovirus and enterovirus. Nodes regress in 1 to 2 weeks.
- Pain / where it sits / key finding
- Mild · Cervical nodes, children · Regresses in 1–2 weeks with an upper respiratory infection
- Testing & cause
- Observation is usually enough. A node larger than 1 cm is abnormal and needs investigation if it persists beyond 4 to 6 weeks or enlarges — biopsy then looks for fungal, granulomatous or neoplastic causes.
- First-line treatment
- Observation.
- Education & prognosis
- The two numbers that matter are 1 cm and 4 to 6 weeks; past either, it stops being reactive.
Slides 31
HIV-associated cervical adenopathy Urgent
Gives itself away by: Cervical adenopathy in 12–45% of patients with HIV · the neck is the commonest site
- Presentation & who gets it
- Cervical adenopathy is present in 12% to 45% of patients with HIV. Idiopathic follicular hyperplasia is the commonest cause. Persistent generalized lymphadenopathy — lymphadenopathy with no identifiable infectious or neoplastic cause — is also common, and the neck is its commonest site.
- Pain / where it sits / key finding
- No · Neck is the commonest site · Follicular hyperplasia after tuberculosis and lymphoma are excluded
- Testing & cause
- Rule out Mycobacterium tuberculosis, Pneumocystis carinii, lymphoma and Kaposi sarcoma before settling on hyperplasia.
- First-line treatment
- Treat the HIV.
- Education & prognosis
- The adenopathy is a marker of control, not a separate problem to excise.
Slides 32
Suppurative bacterial lymphadenopathy Urgent
Gives itself away by: Submandibular or jugulodigastric · with sore throat, skin lesions and upper respiratory symptoms
- Presentation & who gets it
- Most commonly Staphylococcus aureus and group A beta-hemolytic Streptococcus. Masses develop in the submandibular or jugulodigastric regions, with sore throat, skin lesions and upper respiratory symptoms.
- Pain / where it sits / key finding
- Yes · Submandibular or jugulodigastric · Sore throat and skin lesions with the node
- Testing & cause
- Clinical; culture if aspirated.
- First-line treatment
- Empirical antibiotics against anaerobes and gram-positive organisms. Fine needle aspiration or incision and drainage if antibiotics fail.
- Education & prognosis
- Failure of antibiotics is the trigger to drain, not the starting point.
Slides 33
Cat scratch disease Routine
Gives itself away by: Contact with cats · under 20 years · preauricular and submandibular nodes
- Presentation & who gets it
- Bartonella henselae, with a history of contact with cats. Common under 20 years of age. Lymphadenopathy — commonly preauricular and submandibular — with fever and malaise.
- Pain / where it sits / key finding
- Varies · Preauricular and submandibular · Cat contact, patient under 20
- Testing & cause
- Serologic testing with indirect fluorescent antibodies.
- First-line treatment
- Self-limiting, or azithromycin.
- Education & prognosis
- Self-limiting is the headline; azithromycin shortens it rather than being required.
Slides 34
Toxoplasmosis Routine
Gives itself away by: Undercooked meat or cat feces · fever, malaise, sore throat, myalgias
- Presentation & who gets it
- Toxoplasma gondii, contracted through poorly cooked meat or ingestion of oocytes in cat feces. Fever, malaise, sore throat and myalgias with the adenopathy.
- Pain / where it sits / key finding
- Varies · Cervical nodes · Undercooked meat or cat feces in the history
- Testing & cause
- Serologic testing.
- First-line treatment
- Sulfonamides or pyrimethamine.
- Education & prognosis
- One of four exposure histories on the same slide — cat feces here, cat scratch for Bartonella.
Slides 33
Tularemia Urgent
Gives itself away by: Rabbits, ticks, contaminated water · tonsillitis with painful adenopathy
- Presentation & who gets it
- Francisella tularensis, transmitted by rabbits, ticks and contaminated water. Tonsillitis, painful adenopathy, fever, chills, headache and fatigue.
- Pain / where it sits / key finding
- Yes — painful adenopathy · Cervical nodes · Rabbits, ticks or contaminated water, with tonsillitis
- Testing & cause
- Serologic testing and cultures.
- First-line treatment
- Streptomycin.
- Education & prognosis
- The exposure history is the question: rabbits and ticks.
Slides 33
Brucellosis Routine
Gives itself away by: Unpasteurized milk · total body lymphadenopathy
- Presentation & who gets it
- Brucella, transmitted by ingestion of unpasteurized milk, most commonly in children. Total body lymphadenopathy with fever, fatigue and malaise.
- Pain / where it sits / key finding
- No · Total body, not just neck · Unpasteurized milk
- Testing & cause
- Serology and cultures.
- First-line treatment
- Trimethoprim-sulfamethoxazole or tetracycline.
- Education & prognosis
- Generalized rather than regional adenopathy is what sets it apart from the others on this slide.
Slides 33
Actinomycosis Routine
Gives itself away by: PAINLESS, fluctuant mass · submandibular or upper digastric
- Presentation & who gets it
- Presents as a painless, fluctuant neck mass in the submandibular or upper digastric region.
- Pain / where it sits / key finding
- No — painless · Submandibular or upper digastric · Painless and fluctuant
- Testing & cause
- Clinical and biopsy.
- First-line treatment
- Penicillin.
- Education & prognosis
- Painless and fluctuant together is the combination that points here.
Slides 34
Atypical mycobacteria Urgent
Gives itself away by: Children · UNILATERAL · brawny reddish-brown skin over the mass
- Presentation & who gets it
- A pediatric infection. A unilateral neck mass in the anterior triangle or the parotid gland, with brawny (reddish-brown) skin, induration and pain.
- Pain / where it sits / key finding
- Yes · Unilateral, anterior triangle or parotid · Brawny reddish-brown skin over it, in a child
- Testing & cause
- Stain or culture for acid-fast bacilli, plus skin testing.
- First-line treatment
- Surgical excision, or incision and drainage with antibiotics.
- Education & prognosis
- Unilateral and pediatric here; tuberculous adenitis is more diffuse and bilateral.
Slides 34
Tuberculous adenitis (scrofula) Urgent
Gives itself away by: Adults more than children · DIFFUSE and BILATERAL
- Presentation & who gets it
- Mycobacterium tuberculosis. Cervical tuberculosis is called scrofula. Adults are affected more than children, and the lymphadenopathy is more diffuse and bilateral than in atypical mycobacterial disease.
- Pain / where it sits / key finding
- Varies · Bilateral and diffuse · Adults more than children; acid-fast bacilli
- Testing & cause
- Tuberculin skin test, stain and culture for acid-fast bacilli.
- First-line treatment
- Isoniazid, rifampin, rifabutin, rifapentine, pyrazinamide, ethambutol — traditionally RIPE: rifampin, isoniazid, pyrazinamide, ethambutol.
- Education & prognosis
- Bilateral and diffuse versus unilateral and brawny is the whole distinction from atypical mycobacteria.
Slides 34
Fungal neck infection Urgent
Gives itself away by: Immunocompromised · Candida, Histoplasma, Aspergillus
- Presentation & who gets it
- Immunocompromised patients are particularly susceptible. The commonest organisms are Candida, Histoplasma and Aspergillus.
- Pain / where it sits / key finding
- Varies · Cervical nodes · Immunocompromised host; fungal culture and serology
- Testing & cause
- Fungal cultures and serology are required — the deck is emphatic about this.
- First-line treatment
- Amphotericin B, treated aggressively.
- Education & prognosis
- Non-infectious inflammatory causes sit on the same slide: Sjögren syndrome, sarcoidosis, IgG4-related sialadenitis and Kawasaki disease.
Slides 35
Also tested
- Neck mass by age. Under 40 most neck masses are inflammatory, except Hodgkin lymphoma; above 40 the probability shifts toward malignancy.
- Pulsatile neck mass. Pulsatility or a bruit means a vascular lesion, most likely a paraganglioma, which arises at the carotid body, the vagus or the jugulotympanic region. It must not be biopsied blindly and needs computed tomography angiography first.
- Persistent cervical node. A node over 1 centimeter is abnormal, and reactive nodes regress within one to two weeks. Persistence beyond four to six weeks, or continued enlargement, triggers investigation, with biopsy for fungal, granulomatous or neoplastic causes.
- Suppurative lymphadenitis. A hot, tender, fluctuant node with fever after sore throat is most often Staphylococcus aureus or group A beta-hemolytic streptococcus, in the submandibular or jugulodigastric regions. Empirical antibiotics come first, with aspiration or drainage if they fail.
- Persistent lymphadenopathy in an immunocompromised host. If bacterial cultures are negative and antibiotics fail, send fungal cultures and serology; fungal causes are most commonly Candida, Histoplasma and Aspergillus.
- Persistent generalized lymphadenopathy in HIV. It is defined by the absence of an identifiable infectious or neoplastic cause, and is treated by treating the HIV with antiretroviral therapy.
- Actinomycosis. It presents as a painless fluctuant mass in the submandibular or upper digastric region; painlessness with fluctuance separates it from an ordinary pyogenic abscess, which is exquisitely tender. Diagnosis is clinical and by biopsy, and penicillin is the treatment.
- Oropharyngeal tularemia. Exposure to rabbits, ticks or contaminated water points to Francisella tularensis; tonsillitis with painful adenopathy and systemic symptoms is the oropharyngeal form. Diagnosis is by serology and culture, and streptomycin is the treatment of choice.
- Kaposi sarcoma. One of the conditions to exclude in an HIV-positive patient with lymphadenopathy, alongside tuberculosis, Pneumocystis and lymphoma; its vascular nature gives a purple appearance, unlike the follicular hyperplasia behind most adenopathy in this group.
- Kawasaki disease. A non-infectious inflammatory cause of neck masses, alongside Sjogren syndrome, sarcoidosis and IgG4-related disease. The cervical node is one criterion among several, and untreated Kawasaki disease causes coronary artery aneurysms.
- Kawasaki disease. A non-infectious inflammatory cause of neck masses, alongside Sjogren syndrome, sarcoidosis and IgG4-related disease. Features are high fever for five days, red eyes without discharge, strawberry tongue, cracked lips, rash and one large cervical node. Untreated, it causes coronary artery aneurysms.
4.5 · Neoplastic neck masses
Neck neoplasm — general Emergent
Gives itself away by: Presume any new neck mass is MALIGNANT until proven otherwise · firm, slowly progressive, asymptomatic
- Presentation & who gets it
- Benign tumors arise from the soft tissue of the neck — fat, salivary tissue, lymph nodes, blood vessels, nerves. Malignant ones are usually metastatic squamous cell carcinoma from skin or the upper aerodigestive tract. Hoarseness, dysphagia and odynophagia are the symptoms; the lesion itself is asymptomatic, slowly progressive and firm.
- Pain / where it sits / key finding
- No — asymptomatic · Cervical nodes, often jugulodigastric · Firm, immobile, over 1.5 cm, present over 2 weeks
- Testing & cause
- Complete head and neck examination, then fine needle aspiration biopsy rather than excisional biopsy — excision spills tumor and complicates definitive treatment. Fiberoptic laryngoscopy for an occult primary; ultrasound, contrast computed tomography, magnetic resonance imaging, positron emission tomography.
- First-line treatment
- Directed by the primary once it is found. Once the diagnosis is confirmed, all mucosal surfaces of the head and neck, the thyroid, the salivary glands and the skin are examined — the office examination usually finds the primary.
- Education & prognosis
- The malignancy features from slide 13: no infectious origin, duration over 2 weeks, size over 1.5 cm, firm and non-tender with little mobility, age over 40, tobacco and alcohol, and ulceration.
Slides 37, 39
Primary neck tumors — the list Emergent
Gives itself away by: Slide 38 is a picture of a table · malignant against benign, primary in the neck
- Presentation & who gets it
- Malignant: sarcomas (rhabdomyosarcoma, fibrosarcoma, malignant fibrous histiocytoma, liposarcoma, leiomyosarcoma); malignant peripheral nerve sheath tumors; lymphoma; and metastasis — mucosal cancer from head and neck, salivary malignancies, skin malignancies. Benign: vascular neoplasms, chiefly paragangliomas (carotid body, vagal, jugulotympanic); arteriovenous malformations; peripheral nerve neoplasms (schwannomas, neurofibromas, neuromas); and lipomas.
- Pain / where it sits / key finding
- Varies · Neck soft tissue · Pulsatile or bruit means paraganglioma
- Testing & cause
- As for any neck neoplasm — fine needle aspiration first.
- First-line treatment
- By tumor type.
- Education & prognosis
- A pulsatile mass or a bruit means vascular, and paraganglioma heads that list.
Slides 38
Also tested
- Squamous cell neck node. The neck disease is a metastasis, so the primary must be located; its site determines the extent of resection and the radiotherapy field. Every mucosal surface, the thyroid, the salivary glands and the skin are examined systematically.
- Examining a cervical mass. Also palpate the inguinal, axillary and supraclavicular nodes to distinguish regional disease from generalized lymphadenopathy, which points to a systemic cause such as lymphoma, mononucleosis or HIV. Examine the thyroid, liver and spleen, and auscultate any vascular abnormality.
- Neck mass history. Ask about recent travel and possible tuberculosis exposure, along with recent infection, exposure to pets and animals, malignancy risk factors, recent trauma and immunodeficiency.
- Exposure history for cervical adenopathy. Ask about tuberculosis contact and animal exposure; recent travel makes the tuberculosis and zoonotic causes considerably more relevant.
- General symptoms of a concerning neck mass. Fever, postnasal drip, rhinorrhea, sore throat, otalgia, night sweats, weight loss, malaise, dysphagia and hoarseness accompany it; hoarseness and dysphagia suggest upper aerodigestive tract involvement.
- Neck mass that swells at mealtimes. Swelling that varies with eating points to a salivary rather than a nodal cause, because eating stimulates salivary flow and an obstructed gland distends; lymph nodes and neoplasms do not change size over minutes.
- Size of hyperplastic lymph nodes. Reactive hyperplastic nodes are rarely larger than 2 centimeters, so exceeding that adds weight to the concern raised by the other features.
4.6 · The thyroid
Thyroid nodule and mass Urgent
Gives itself away by: MIDLINE mass that ELEVATES WITH SWALLOWING · the main cause of an anterior neck lump
- Presentation & who gets it
- The main cause of anterior neck masses and lumps. An immobile midline neck mass that elevates with swallowing is likely thyroid. Risk factors: age under 30 or over 60, childhood head and neck irradiation, full body irradiation for bone marrow transplant, family history of thyroid cancer, and multiple endocrine neoplasia type 2. Recent growth, dysphagia or obstruction are the concerning symptoms.
- Pain / where it sits / key finding
- No · Midline anterior neck · Elevates with swallowing; hot nodule needs no biopsy
- Testing & cause
- Ultrasound with fine needle aspiration, thyroid-stimulating hormone, T3 and T4. Incidental nodules over 1 cm need evaluation. If hyperthyroid with a low thyroid-stimulating hormone, do a radionuclide scan with technetium BEFORE the aspiration: a “hot” (hyperfunctioning) nodule needs no biopsy, while a “cold” or “warm” nodule does.
- First-line treatment
- Determined by the biopsy. Fine needle aspiration is the diagnostic procedure of choice once primary thyroid disease has been excluded on labs.
- Education & prognosis
- If thyroid cancer is suspected, avoid iodine-contrast computed tomography — it compromises radioiodine treatment afterwards.
Slides 40–41
Papillary thyroid carcinoma Urgent
Gives itself away by: Commonest (75%) · best prognosis · young women
- Presentation & who gets it
- The commonest thyroid cancer at 75%, with the best prognosis, commonest in young females. Involves thyroid epithelial cells.
- Pain / where it sits / key finding
- No · Thyroid · Commonest at 75%, best prognosis, young women
- Testing & cause
- Fine needle aspiration.
- First-line treatment
- Lobectomy or thyroidectomy, with or without neck dissection, ablation and surveillance. Almost all thyroid cancers need thyroidectomy, except a well-differentiated cancer localized to one lobe with no metastasis.
- Education & prognosis
- Commonest and kindest — the pairing is the exam point.
Slides 42, 44
Follicular thyroid carcinoma Urgent
Gives itself away by: Second commonest (16%) · spreads by BLOOD to bone and lung
- Presentation & who gets it
- 16% of thyroid cancers, involving thyroid epithelial cells. Spreads to local lymph nodes or by blood to bone and lungs. The Hürthle cell variant is more aggressive, with a higher risk of metastases and recurrence.
- Pain / where it sits / key finding
- No · Thyroid · Spreads by blood to bone and lung
- Testing & cause
- Fine needle aspiration.
- First-line treatment
- As for papillary: lobectomy or thyroidectomy with or without neck dissection and ablation.
- Education & prognosis
- Hematogenous spread is what separates it from papillary.
Slides 42, 44
Medullary thyroid carcinoma Urgent
Gives itself away by: About 5% · parafollicular C cells · calcitonin · screen for MEN
- Presentation & who gets it
- About 5%. A disorder of the parafollicular or C cells, which produce calcitonin. More insidious, most likely to metastasise, and can go undiagnosed until a metastasis is found.
- Pain / where it sits / key finding
- No · Thyroid · C cells and calcitonin; screen for multiple endocrine neoplasia
- Testing & cause
- Fine needle aspiration; calcitonin.
- First-line treatment
- Thyroidectomy with monitoring for recurrence on screening labs, with or without external beam radiation for nodal disease. Screen family members for multiple endocrine neoplasia.
- Education & prognosis
- The only one of the four with a familial syndrome to chase in the relatives.
Slides 42, 44
Anaplastic thyroid carcinoma Emergent
Gives itself away by: 1% · elderly · death in 6–36 months · resistant to all treatment
- Presentation & who gets it
- 1% of thyroid cancers, commonly in elderly patients. Small cell, giant cell and spindle cell types. The most aggressive form — death in 6 to 36 months — and resistant to all treatment modalities.
- Pain / where it sits / key finding
- Varies · Thyroid · Elderly; death in 6–36 months
- Testing & cause
- Fine needle aspiration; staging imaging.
- First-line treatment
- Isthmectomy rather than thyroidectomy.
- Education & prognosis
- The one thyroid cancer where the prognosis is measured in months.
Slides 42, 44
Primary thyroid lymphoma Urgent
Gives itself away by: Associated with Hashimoto thyroiditis · non-Hodgkin B cell
- Presentation & who gets it
- Most commonly non-Hodgkin B cell tumors, associated with Hashimoto thyroiditis.
- Pain / where it sits / key finding
- No · Thyroid · Hashimoto thyroiditis in the background
- Testing & cause
- Fine needle aspiration alone cannot separate lymphoma from Hashimoto — a biopsy is needed to confirm, along with lymphoma staging.
- First-line treatment
- Chemotherapy and radiation — not primarily surgical, unlike the carcinomas above.
- Education & prognosis
- The one thyroid malignancy where the answer is not an operation.
Slides 45
Also tested
- Surgery for papillary thyroid carcinoma. Almost all thyroid cancers require thyroidectomy. The exception is disease localized to one lobe, well differentiated and without metastasis, where lobectomy may be sufficient, preserving the contralateral gland and reducing risk to the recurrent laryngeal nerves and parathyroids.
- Thyroid mass on Hashimoto background. Primary thyroid lymphoma is usually a non-Hodgkin B cell tumor arising on Hashimoto thyroiditis. Aspiration cannot reliably separate a reactive from a monoclonal infiltrate, so proceed to open biopsy, then lymphoma staging.
- Incidental thyroid nodule. Nodules over 1 centimeter found incidentally warrant evaluation: ultrasound with fine needle aspiration plus thyroid-stimulating hormone and thyroid hormones, asking about recent growth, dysphagia or obstruction.
- Thyroid carcinoma prognosis. Papillary is best, then follicular, then medullary, with anaplastic worst. Papillary is commonest; follicular spreads hematogenously; medullary is insidious and most likely to metastasize; anaplastic is most aggressive, causing death in 6 to 36 months and resistant to all treatment.
- Medullary thyroid carcinoma surveillance. The tumor arises from parafollicular C cells, whose normal product is calcitonin, so it secretes calcitonin and the level tracks tumor burden, making it a specific marker for residual or recurrent disease.
- Anaplastic thyroid carcinoma operation. Almost all thyroid cancers require thyroidectomy; the two exceptions are well-differentiated disease localized to a single lobe with no metastasis, and anaplastic carcinoma, where isthmectomy is specified because it is not curable by resection.
5 · Disorders of the Oral Cavity, Salivary Glands and Neck
Instructional Objectives
DISORDERS OF THE EARS, NOSE, THROAT AND NECK — Disorders of the Oral Cavity, Salivary Glands, and Neck
- Compare and contrast the etiologies, epidemiology, risk factors, clinical
manifestations, differential diagnosis, diagnostic testing (including ordering and
interpretation), management (acute and chronic, including applicable rehabilitative and
palliative care), appropriate referrals, patient education, and prognosis of the following
disorders of the oral cavity, salivary glands, and neck:
- Stomatitis
- Ulcers
- Aphthous ulcerations
- Recurrent aphthous stomatitis (including herpetiform morphology)
- Herpes simplex virus ulcers
- Sialadenitis
- Sialolithiasis
- Parotitis
- Laryngitis
- Vocal cords
- Nodules
- Polyps
- Papillomatosis
- Paralysis
- Epiglottitis
- Pharyngitis
- Epstein-Barr virus (EBV) and infectious mononucleosis
- Rheumatic fever (as potential complication of strep pharyngitis)
- Oral Candidiasis
- Tonsillitis
- Cervical adenitis
- Deep neck infections
- Peritonsillar abscess
- Retropharyngeal abscess
- Ludwig angina
- Diphtheria
- Gingivitis
- Dental caries
- Dental abscess
- Temporomandibular joint disorders
- Diseases of gingiva
- Diseases of teeth
- Lichen Planus
- Oral leukoplakia
- Neoplasms: 1. Benign · 2. Malignant
- Oropharyngeal trauma
- Identify medical care strategies for disorders of the oral cavity, salivary glands, and neck in the lecture topic list for the following populations: 1. adolescent · 2. adult · 3. elderly
The biggest lecture in the block by a distance — 151 slides, and the objective list above runs to 35 conditions. It has no recording, so everything below is slide content.
5.1 · Examining the mouth, and the salivary anatomy
The oral cavity is the outer aspects of the lips and buccal mucosa, the teeth and gingiva, the anterior two thirds of the tongue, the floor of the mouth, the hard palate and the retromolar trigone. Over 80% of surveyed clinicians believe oral examination is important, and far fewer actually do one — which is the lecture's argument for the section. Take a careful medical and medication history first: xerostomia, immunosuppression and chemotherapy change what you are looking at.
| Gland | Duct | Where it opens |
|---|---|---|
| Parotid | Stensen duct | Sides of the face; the duct crosses the masseter and opens opposite the upper second molar. The gland most often affected by suppurative sialadenitis and by neoplasm. |
| Submandibular | Wharton duct | Beneath the floor of the mouth. The long, upward-running duct is why 80–90% of stones form here. |
| Sublingual | Sublingual ducts | Floor of the mouth. The source of a ranula. |
| Minor | — | Exocrine tissue in buccal, labial and palatal mucosa. Only 35% of minor gland tumors are benign — the smaller the gland, the likelier a tumor is malignant. |
The scrape test settles three diagnoses at the bedside. Wipe the lesion with a tongue depressor. It comes off → oral candidiasis. It does not come off and it is white → leukoplakia (premalignant, 5–20% become squamous cell carcinoma). It does not come off and it is lacy → lichen planus (Wickham striae). And a fourth: a grayish-white change that disappears when you stretch the mucosa is leukoedema, a normal variant.
Prof. Shah, [1:34:40]: “Centor criteria is something that everyone most definitely needs to know. Like, you absolutely need to know the Centor criteria, no matter what… So I don’t know how you’re going to know that, but you need to know that. That means you need to come up with an acronym, you need to come up with a song, you need to dance it out — whatever you need to do to make sure you know it. You’re going to be using this all the time.” She then worked it through component by component and score by score [1:22:47–1:24:23], and framed it around the question students get stuck on — the rapid test is negative, now what? Answer: throat culture, and whether you treat “depends on how sick they are.”
The antipyretic trap on the fever point [1:33:00], which is not on the slide. Fever scores a point, but a normal temperature in clinic does not automatically score zero. If they took ibuprofen six hours ago and are still 102 °F in front of you, that counts. If they took it two hours ago and read 99.9, the number in front of you is not the answer — ask what their maximum temperature was, how many days they have had fever, the highest reading in the past 24 hours, and whether the fever returns as the next dose comes due.
Centor criteria, and what to do with the score (slides 74–77). One point each for absence of cough, tonsillar exudate, fever, and tender anterior cervical lymphadenopathy; plus +1 for age 3–14, 0 for age 15–44, and −1 for age 45 or over.
Score 0 to 1 — risk of group A streptococcus roughly 1–10%; no further testing and no antibiotics. Score 2 to 3 — risk roughly 11–35%; perform a rapid antigen test or culture and treat only if positive. Score 4 or more — risk roughly 51–53%; consider empiric treatment. In children and adolescents, a negative rapid test is confirmed with a throat culture (the slide says “always”; the Infectious Diseases Society of America does not require it in adults). The slide calls antistreptolysin O the definitive test, because carriers culture positive while asymptomatic, but the titer rises only over weeks: it shows recent past infection, as in rheumatic fever, and does not diagnose an acute sore throat.
Streptococcal against viral pharyngitis (the comparison on slide 71). The streptococcal picture is tonsillar and pharyngeal erythema with purulent exudate, fever above 100.4 °F, tender cervical nodes and NO cough. The viral picture brings the things streptococcus does not: cough, rhinitis, hoarseness, conjunctivitis, and sometimes herpangina — ulcerative vesicles over the tonsils. Cough is worth a Centor point in its absence precisely because its presence argues so strongly against strep.
The thumbprint sign (slide 64) is the swollen epiglottis seen on a lateral neck X-ray, set against the thin, curved normal epiglottis. It is worth recognizing and worth not ordering: the lecture is explicit that it is not necessary for diagnosis, and that once epiglottitis is suspected, examinations that agitate the patient can complete the obstruction.
Four times in this lecture — two diagnoses, and two single findings that turn an ordinary presentation into an urgent one, which is the more useful half of the list. She also uses it once in the negative, which is what shows the phrase is a deliberate grade rather than a verbal tic.
Chronic laryngitis [59:40]. “Chronic laryngitis is where you have vocal disturbances that go on for more than two weeks… Here, your brain should automatically be thinking of cancer or polyps, right? Something bad, right? Bad, bad, bad. And in these instances, you have to refer to ENT as soon as possible, like ASAP, like yesterday.” The two-week mark is the trigger and the referral is the answer — not a longer course of anything.
Epiglottitis [1:00:05]. She notes first that supraglottitis is “a much more correct terminology”, because the inflammation involves several supraglottic structures rather than one. Then: “This is an absolute emergency, okay? Emergency. This is bad. This is bad, bad, bad. You cannot miss this diagnosis. This will hurt the patient. This will kill the patient if it’s missed.” Read it with the thumbprint paragraph above: the film is not what makes the diagnosis, and examining the throat can finish the airway.
A neck mass that does not move. Running through what a node examination must document — site, size, consistency, tenderness — she reaches mobility: “If it’s immobile, not moving, that is bad. That is bad, bad, bad.” And she gives the word to write: document it as immobile or FIXED, “because that’s telling whoever’s reading it that it’s not moving and it’s stuck to whatever location it is.” The finding is the alarm; the wording is how you pass the alarm on.
A rim-enhancing hypodense collection on computed tomography. Her described classic for a deep neck abscess — an enhancing rim around a sac of fluid. “So this is bad. Now we’ve like bad, bad, bad, right? Protect the airway. This is a surgical emergency.” Antibiotics must cover streptococci, staphylococci and anaerobes. She was counting as she went — this was the second emergency of the lecture.
And the one she says is NOT. Leukoplakia [2:37:42]: it does not scrape off, and it may bleed if you try — “This is a pre-malignant lesion. This is bad… not bad, bad, bad, but bad enough where we have to work it up relatively quickly.” Useful in both directions: it fixes leukoplakia one rung below the four above, and it confirms the phrase is how she grades urgency out loud.
5.2 · Normal variants of the oral mucosa
Leukoedema Routine
Gives itself away by: Normal variant · grayish-white buccal mucosa that DISAPPEARS WHEN STRETCHED
- Presentation & who gets it
- A common, benign mucosal change and a normal variant, caused by accumulation of fluid within the epithelial cells. Diffuse grayish-white appearance of the buccal mucosa.
- Pain / where it sits / key finding
- No · Buccal mucosa · Disappears when the mucosa is stretched
- Testing & cause
- Clinical. The distinguishing maneuver is stretching the mucosa — the change disappears, which is what separates it from leukoplakia.
- First-line treatment
- None — reassurance.
- Education & prognosis
- Naming it as a variant is the whole job; it needs no biopsy and no follow-up.
Slides 9
Fordyce granules Routine
Gives itself away by: Normal variant · ectopic sebaceous glands · yellow-white papules on lip or buccal mucosa
- Presentation & who gets it
- Normal variants — ectopic sebaceous glands in a site where sebaceous glands are not expected. Small yellow-white papules on the vermilion of the lip and the buccal mucosa.
- Pain / where it sits / key finding
- No · Vermilion of lip, buccal mucosa · Yellow-white papules — ectopic sebaceous glands
- Testing & cause
- Clinical.
- First-line treatment
- None — reassurance.
- Education & prognosis
- Patients find them alarming because they appear suddenly to the person looking; they have always been there.
Slides 10
Physiologic pigmentation Routine
Gives itself away by: Normal variant · symmetrical melanin pigmentation, commoner in darker skin
- Presentation & who gets it
- Physiologic oral pigmentation is commonly seen and is a normal variant, from melanin.
- Pain / where it sits / key finding
- No · Gingiva and mucosa · Symmetrical melanin pigmentation, a normal variant
- Testing & cause
- Clinical.
- First-line treatment
- None — reassurance.
- Education & prognosis
- The reason it matters is the differential it sits in, not the lesion itself.
Slides 11
5.3 · Stomatitis and oral ulcers
Aphthous stomatitis (canker sores) Routine
Gives itself away by: Painful round ulcer, YELLOW-GRAY fibrinoid center with a RED HALO · on non-keratinized, freely moving mucosa
- Presentation & who gets it
- The commonest cause of acute recurrent oral ulcers in adolescents and young adults. Found on freely moving, non-keratinized mucosa — buccal and labial mucosa, non-attached gingiva, palate. Trauma (cheek biting, a dental procedure) and stress are exacerbating factors; the cause is unknown, though human herpesvirus 6 has been suggested. Minor (<1 cm) are commonest, burn and tingle first, and last 7–10 days. Major (>1 cm) are more painful, multiple, scar, and last over a month. Herpetiform are numerous 1–3 mm ulcers, scar, and last over a month.
- Pain / where it sits / key finding
- Yes — painful · Non-keratinized, freely moving mucosa · Yellow-gray fibrinoid center with a red halo
- Testing & cause
- Clinical.
- First-line treatment
- Observation — it is self-limiting. Anti-inflammatories, antibiotics, antivirals, oral and topical corticosteroids (triamcinolone, fluocinonide), cauterization with silver nitrate, Lactobacillus capsules, dilute water rinses.
- Education & prognosis
- Recurrent aphthous stomatitis is called Sutton disease. Non-keratinized mucosa is the location rule that separates it from herpes.
Slides 15–17
Herpes simplex ulcers Routine
Gives itself away by: Prodrome of burning and tingling ~24 h BEFORE the lesion · recurrence from the trigeminal ganglion
- Presentation & who gets it
- Herpes simplex virus 1 and 2. Herpetic gingivostomatitis is the commonest manifestation of primary infection in children and young adults, with fever, malaise and cervical lymphadenopathy. Secondary disease is recurrence of dormant virus from the trigeminal ganglion, triggered by stress, trauma, immunosuppression or ultraviolet light. Small painful lesions that ulcerate, leaving an erythematous base with a gray cover; heals without a scar; resolves in 1–2 weeks.
- Pain / where it sits / key finding
- Yes · Perioral and oral, keratinized surfaces · Burning prodrome ~24 h before the lesion
- Testing & cause
- Clinical, but confirm with polymerase chain reaction for HSV DNA — most sensitive and specific. Serology with IgG and IgM distinguishes HSV 1 from HSV 2. Tzanck smear shows multinucleated giant cells but is also positive in varicella zoster, so it is not the best test.
- First-line treatment
- Oral acyclovir for treatment and prophylaxis.
- Education & prognosis
- The 24-hour prodrome is the window in which treatment works best, so patients are taught to recognize it.
Slides 25–27
Behcet syndrome Urgent
Gives itself away by: Oral ulcers in up to 100% · GENITAL ulcers in 75% · multisystem
- Presentation & who gets it
- An inflammatory, multisystem disorder with vascular, articular, gastrointestinal, neurologic, urogenital, pulmonary and cardiac involvement. Oral ulcers are the commonest feature, affecting up to 100% of patients. Genital ulcers occur in about 75% and look like oral aphthae.
- Pain / where it sits / key finding
- Yes · Oral and genital · Oral ulcers in up to 100%, genital in 75%
- Testing & cause
- Clinical — recurrent aphthous ulceration in the context of the characteristic systemic manifestations.
- First-line treatment
- No cure. Corticosteroids, intravenous immunoglobulin, immunosuppressives — colchicine, azathioprine, cyclosporine-A, interferon alpha, cyclophosphamide.
- Education & prognosis
- The oral ulcers look ordinary; it is the genital ulcers and the systemic features that make the diagnosis.
Slides 19
Oral lichen planus Urgent
Gives itself away by: WICKHAM STRIAE — lacy white lines on buccal mucosa · 1–4% become squamous cell carcinoma
- Presentation & who gets it
- A common chronic inflammatory autoimmune disorder in which the basal layer is destroyed by activated lymphocytes. May be familial or drug-induced (penicillamine, methyldopa, phenothiazine, antimalarials). Classically purple, polygonal, pruritic papules on flexor surfaces and trunk; 60–70% affect lips, oral mucosa and eyelids, and the oral lesions are more chronic. Kobner isomorphic phenomenon — lesions provoked by physical trauma. Types: reticular (lacy white Wickham striae), plaque (looks like leukoplakia), atrophic, erosive and bullous, ulcerative, annular.
- Pain / where it sits / key finding
- Varies — erosive types hurt · Buccal mucosa, tongue, lips · Wickham striae — lacy white lines
- Testing & cause
- Clinical, with biopsy where malignancy is a concern.
- First-line treatment
- Aimed at pain relief. Identify reversible contributors — medications, dental restorations, oral hygiene, tobacco and alcohol. Topical or oral corticosteroids; lidocaine, tacrolimus, cyclosporine.
- Education & prognosis
- 1–4% progress to squamous cell carcinoma, and the risk is higher with ulcerative lesions — which is why close follow-up is the point of the diagnosis.
Slides 20–22
Systemic lupus erythematosus — oral Urgent
Gives itself away by: 40% of patients with lupus · oral lesions may be the FIRST SIGN · honeycomb patches
- Presentation & who gets it
- 40% of patients with systemic lupus erythematosus have mucous membrane involvement, and oral lesions may be the first sign of lupus. Painful or painless, with no correlation to systemic activity. Lesions: cheilitis, erythematous patches, honeycomb patches, discoid and discrete ulcers. White plaques, erythematous areas and punched-out erosions with surrounding erythema on the soft and buccal mucosa.
- Pain / where it sits / key finding
- Varies · Lips, soft and buccal mucosa · Honeycomb patches; may be the first sign of lupus
- Testing & cause
- Clinical, with serology for the systemic disease.
- First-line treatment
- Photoprotection plus medication: topical or intralesional corticosteroids, topical calcineurin inhibitors, systemic glucocorticoids, and systemic antimalarials — hydroxychloroquine or chloroquine.
- Education & prognosis
- The oral ulcers do not track disease activity, so they cannot be used to judge control.
Slides 23–24
Also tested
- Oral lichen planus. It carries a 1 to 4 percent risk of carcinoma (squamous cell), higher if ulcerative, which is why close follow-up is the point of the diagnosis.
- Minor aphthous ulcers. They are the commonest form, under 1 centimeter, preceded by burning and tingling, painful, and heal in 7 to 10 days without scarring.
- Oral lichen planus. 1 to 4 percent progress to squamous cell carcinoma, higher with ulcerative lesions, so close follow-up is the point of making the diagnosis.
- Mucous membrane involvement in systemic lupus. About 40 percent of patients have it, and oral lesions may be the first sign; the oral ulcers do not correlate with systemic activity.
- Oral ulcers in Behcet syndrome. They are the commonest feature, affecting up to 100 percent of patients, with genital ulcers in about 75 percent that look identical to oral aphthae.
- Causes of stomatitis. Listed causes include chemotherapy or radiation, ill-fitting dentures or braces, cheek and tongue biting, surgery, herpes or coxsackievirus, candidiasis, xerostomia, tobacco, zinc or iron deficiency, allergy, and idiopathic aphthous ulceration.
5.4 · Salivary glands
Acute suppurative sialadenitis Urgent
Gives itself away by: PAROTID swelling, firm and diffusely tender · PUS EXPRESSED FROM THE DUCT · dehydrated post-operative or elderly patient
- Presentation & who gets it
- Bacterial infection of a salivary gland, beginning with stasis of salivary flow. Occurs in post-operative patients, elderly patients with chronic conditions, and children under 2 months. Risk factors: dehydration, trauma, immunosuppression, chemotherapy or radiation, age over 50, HIV, xerostomia, sialolithiasis, anorexia and bulimia. Staphylococcus aureus is the commonest pathogen. The parotid is most commonly affected: unilateral, firm, diffusely tender, with overlying erythema, trismus, purulent ductal discharge, induration, fever and chills.
- Pain / where it sits / key finding
- Yes — firm, diffusely tender · Parotid, unilateral · Pus expressed from the duct
- Testing & cause
- Clinical is usually sufficient. If uncertain: culture, and ultrasound, computed tomography or magnetic resonance imaging to look for stones, abscess or gland inflammation.
- First-line treatment
- Rehydration plus intravenous antibiotics with penicillinase-resistant gram-positive cover (nafcillin or cefazolin), then oral (dicloxacillin, clindamycin). Warm compresses, massage, sialogogues (lemon drops or vitamin C lozenges), oral hygiene. No improvement in 48 hours means presume an abscess.
- Education & prognosis
- Submandibular disease that fails treatment can mimic Ludwig angina, which threatens the airway.
Slides 34–39
Sialolithiasis Routine
Gives itself away by: Recurrent swelling and pain WORSE WITH EATING (salivary colic) · 80–90% SUBMANDIBULAR
- Presentation & who gets it
- Salivary calculi. Change in saliva viscosity, ductal injury or stagnation causes calcium phosphate and calcium carbonate to precipitate. 80–90% occur in the submandibular gland — the duct runs a longer course, and the saliva has higher mucin, alkaline content, calcium and phosphate. 10–20% parotid. Commoner in men. Risk: long illness with dehydration, gout, diabetes, hypertension.
- Pain / where it sits / key finding
- Yes — with eating · Submandibular duct in 80–90% · Salivary colic — swelling and pain on eating
- Testing & cause
- Usually clinical. Submandibular stones are calcium phosphate and hydroxyapatite, so they are RADIOPAQUE and visible on plain films. Ultrasound shows an echogenic structure with acoustic shadow; computed tomography is the most sensitive; digital subtraction sialography is the most accurate. Stones may be palpable in the anterior two thirds of the duct.
- First-line treatment
- By location and size: intraoral extraction if palpable or visible anteriorly; gland excision for large stones in the hilum or body; sialoendoscopy, the minimally invasive option that can avoid removing the gland; lithotripsy. Conservative: hydration, hot compresses, massage, non-steroidal anti-inflammatories, lozenges.
- Education & prognosis
- Pain that arrives with the first mouthful and settles afterwards is the history that makes this diagnosis without any test.
Slides 40–43
Parotitis Routine
Gives itself away by: Painful parotid swelling · mumps (paramyxovirus) is the classic viral cause
- Presentation & who gets it
- Painful swelling of the parotid gland. Causes: viral — mumps (paramyxovirus), herpes, Epstein-Barr virus — and also bacterial infection, diabetes, tumors, stones and dental problems.
- Pain / where it sits / key finding
- Yes · Parotid · Mumps is the classic viral cause
- Testing & cause
- Clinical; serology where mumps is suspected.
- First-line treatment
- Directed at the cause.
- Education & prognosis
- It is a presentation, not a single disease — the work is deciding which of the causes it is.
Slides 44
Also tested
- Chronic granulomatous sialadenitis. Chronic gland swelling with minimal pain is the picture; consider primary tuberculosis where risk factors exist. The wide differential (cat scratch disease, sarcoidosis, actinomycosis, granulomatosis with polyangiitis, syphilis) means fine needle aspiration biopsy is needed.
- Acute bacterial parotitis. Dehydration causes salivary stasis, letting bacteria ascend the duct; Staphylococcus aureus is commonest, and pus from Stensen duct confirms infection. Treat with rehydration and antistaphylococcal antibiotics, plus warm compresses, massage and sialogogues.
- No improvement at 48 hours. Failure to improve after 48 hours of rehydration, antibiotics, warm compresses, massage and sialogogues means an abscess should be presumed. The gland becomes doughy and indurated; ultrasound or computed tomography locates the loculation for drainage or guided aspiration.
- Sialolithiasis. It causes recurrent swelling and pain that worsens with eating, because eating stimulates salivary flow and the obstructing stone traps saliva behind it.
- Parotid gland duct. The parotid gland drains through Stensen duct, which crosses the masseter and opens opposite the upper second molar; pus is expressed from it in acute suppurative sialadenitis, characteristically a parotid disease.
- Salivary stones. 80 to 90 percent form in the submandibular gland because its duct (Wharton) is long and uphill, and its saliva is alkaline and mucin-rich with high calcium and phosphate, favoring precipitation of calcium phosphate and carbonate.
5.5 · Vocal cords and larynx
Vocal cord nodules Routine
Gives itself away by: BILATERAL and SYMMETRIC · junction of the anterior one third and posterior two thirds · vocal abuse
- Presentation & who gets it
- Smooth, paired lesions at the junction of the anterior one third and posterior two thirds of the vocal folds, from vocal abuse. The commonest cause of persistent dysphonia in children — screamers' nodules, and a frequent cause of voice deterioration in professional singers — singers' nodules.
- Pain / where it sits / key finding
- No · Anterior third / posterior two thirds junction · Bilateral and symmetric
- Testing & cause
- Laryngoscopy: small, well-defined lesions with a whitish hue, bilateral and symmetric.
- First-line treatment
- Speech therapy is first line in adults and children. Photodocumentation in the voice clinic tracks progress; microlaryngoscopy if needed.
- Education & prognosis
- Bilateral and symmetric is the finding that separates nodules from a polyp, which is unilateral.
Slides 46–47
Vocal cord polyps Urgent
Gives itself away by: UNILATERAL, pedunculated · men with vocal abuse and heavy smoking
- Presentation & who gets it
- Unilateral masses forming within the superficial lamina propria of the vocal fold, commoner in men with a history of vocal abuse and heavy smoking. Fluid-filled and gelatinous, pedunculated, sometimes with visible vascular markings, at the point of maximal vibration.
- Pain / where it sits / key finding
- No · Superficial lamina propria, one fold · Unilateral and pedunculated
- Testing & cause
- Microlaryngoscopic examination with excision — which both confirms the diagnosis and excludes other pathology.
- First-line treatment
- Excision of the polyp, with continued vocal rest and smoking cessation.
- Education & prognosis
- A large polyp may conceal an occult early laryngeal squamous cell carcinoma, which is why it is excised rather than watched.
Slides 48
Vocal cord papillomatosis Urgent
Gives itself away by: Warty exophytic growths in the larynx · HPV 6 and 11 · bimodal — ages 2–4 and the 30s
- Presentation & who gets it
- Recurrent respiratory papillomatosis: benign, non-contagious, rare, with exophytic warty lesions usually in the larynx but also nose, pharynx and trachea. Human papillomavirus subtypes 6 and 11, rarely 16. Bimodal: juvenile between 2 and 4 years, adult peaking in the 30s. Multiple friable irregular warty growths affecting true and false cords, at points of air turbulence and at the change from ciliary to squamous epithelium. Glottic lesions cause dysphonia; supraglottic lesions cause stridor.
- Pain / where it sits / key finding
- No · True and false cords · Warty exophytic growths; HPV 6 and 11
- Testing & cause
- Laryngoscopy.
- First-line treatment
- No curative measure for the virus — the aim is removing symptomatic lesions with minimal morbidity: carbon dioxide laser resection, cold steel dissection, laryngeal microdebrider. Avoid tracheostomy, which introduces another squamociliary junction the papillomas favor. Adjuvant intralaryngeal cidofovir is off-label.
- Education & prognosis
- 3–7% risk of malignant transformation. Gardasil and Gardasil 9 offer eventual prevention.
Slides 49–52
Vocal cord paralysis Urgent
Gives itself away by: Unilateral: hoarse BREATHY voice · bilateral: STRIDOR with a weak cry
- Presentation & who gets it
- One or both folds fail to open or close properly. Causes: injury during surgery to thyroid, parathyroid, esophagus, neck or chest; neck or chest injury; tumors; infections (Lyme disease, Epstein-Barr virus, herpes); neurological disease (stroke, multiple sclerosis, Parkinson disease). Unilateral gives hoarse breathy dysphonia, aspiration, dysphagia, vocal fatigue — and may be asymptomatic. Bilateral gives inspiratory or biphasic stridor, weak cry, aspiration.
- Pain / where it sits / key finding
- No · One or both folds · Unilateral breathy voice; bilateral stridor
- Testing & cause
- Mirror laryngoscopy or flexible nasolaryngoscopy plus a full neurological examination. Determine whether the lesion is the recurrent laryngeal nerve or the vagus, and whether it is unilateral or bilateral.
- First-line treatment
- Decide whether it is self-limiting or permanent. Observation with voice therapy; surgical medialisation of the affected fold, or thyroplasty.
- Education & prognosis
- Laryngeal electromyography predicts recovery: a transected or tumor-infiltrated nerve will not recover, while a bruised or stretched one may return over 6 months to a year.
Slides 53–56
Acute laryngitis Routine
Gives itself away by: Commonest cause of hoarseness · persists about a week after the upper respiratory infection clears
- Presentation & who gets it
- The commonest cause of hoarseness, persisting about a week after upper respiratory symptoms have cleared. Viral (rhinovirus commonest, parainfluenza, respiratory syncytial virus, adenovirus, influenza, pertussis), bacterial or fungal; also acid reflux, smoking, toxic inhalation, cough, vocal abuse, direct injury and allergy. Dysphonia, low-grade fever, hoarseness, cough, rhinitis and postnasal drip.
- Pain / where it sits / key finding
- Mild · Larynx · Hoarseness persisting a week after the cold clears
- Testing & cause
- Clinical.
- First-line treatment
- Conservative: hydration, antipyretics, voice rest, decongestants, humidification, smoking cessation. Antibiotics are not indicated unless a secondary bacterial infection is suspected.
- Education & prognosis
- Voice rest is the treatment patients most often skip and most need.
Slides 57
Chronic laryngitis Urgent
Gives itself away by: Voice disturbance lasting more than 2 weeks · NOT a true diagnosis — work it up
- Presentation & who gets it
- Voice disturbance lasting more than two weeks. Not a true diagnosis — always work up the underlying condition.
- Pain / where it sits / key finding
- No · Larynx · Over 2 weeks — scope it, do not treat it
- Testing & cause
- Refer to ear, nose and throat for laryngoscopy. Laryngeal cancer and vocal cord polyps must be considered.
- First-line treatment
- Treat what the laryngoscopy finds.
- Education & prognosis
- Two weeks of hoarseness is the threshold at which a smoker gets scoped, not reassured.
Slides 58
Also tested
- Recurrent respiratory papillomatosis. Avoid tracheostomy, because it creates another squamociliary junction, a site the papillomas favor, and spreads disease distally into the trachea.
- Laryngeal electromyography in vocal cord paralysis. It predicts whether function will return by showing whether the nerve is still in continuity, which decides between waiting and proceeding to medialization or thyroplasty.
5.6 · The airway emergency
Epiglottitis (supraglottitis) Emergent
Gives itself away by: ENT EMERGENCY · the 4 Ds in children — Drooling, Dysphagia, Dysphonia, Distress · TRIPOD position
- Presentation & who gets it
- More correctly supraglottitis: cellulitis involving multiple areas of the supraglottis. Acute disease presents in children aged 2 to 6, though any age can be affected. Commonest pathogen is Haemophilus influenzae type B — incidence has fallen over 90% since the vaccine. Others: Streptococcus pneumoniae, Staphylococcus aureus, beta-hemolytic streptococci. Children: the 4 Ds. Adults: severe sore throat, dysphagia, odynophagia, fever, dyspnea, cough; muffled voice, stridor and drooling in under 10%. Sudden onset progressing over hours in children, more slowly in adults. Classic picture is an irritable patient sitting or leaning forward, neck hyperextended, chin thrust forward. Inspiratory stridor is a LATE finding — the airway is nearly obstructed.
- Pain / where it sits / key finding
- Severe — odynophagia · Supraglottis · Tripod position, drooling, muffled voice; thumbprint sign
- Testing & cause
- Once suspected, do NOT perform an intraoral examination or venipuncture — the anxiety they cause may complete the obstruction. Lateral neck X-ray shows the “thumb print” sign, but is not necessary for diagnosis. Mirror or fiberoptic laryngoscopy is the gold standard.
- First-line treatment
- Airway, antibiotics, prevention. Pediatric: to theater for rigid bronchoscopy and emergency tracheotomy standby; inhalation anesthesia, confirm the diagnosis, secure the airway by intubation; blood cultures and supraglottic swab; parenteral antibiotics — extubation is often possible within 48 to 72 hours. Adult: observation, intubation or tracheostomy if the airway obstructs, humidification, glucocorticoids, intravenous antibiotics, nebulized adrenaline. Third-generation cephalosporin plus an antistaphylococcal agent — ceftriaxone or cefotaxime with vancomycin for 7–10 days.
- Education & prognosis
- The mortality is what justifies the caution: rare, but high if it is not recognized and treated promptly.
Slides 60–67
Also tested
- Suspected epiglottitis. Avoid intraoral examination and venipuncture once it is suspected, because anxiety-provoking examinations may precipitate complete airway obstruction. Mirror or fiberoptic laryngoscopy in a controlled setting is the gold standard.
- Adult supraglottitis. Admit for observation, intravenous antibiotics and airway monitoring; it progresses more slowly than the pediatric form and often does not require immediate intubation, but intubation or tracheostomy becomes necessary if the airway obstructs.
- Declining epiglottitis. Haemophilus influenzae type B vaccination explains it: the commonest pediatric pathogen, with routine immunization reducing supraglottitis by over 90 percent. It still occurs in unimmunized children.
- Suspected supraglottitis in a child. Do not examine the throat; secure the airway with the appropriate team. Intraoral examination and venipuncture increase anxiety and may precipitate complete airway obstruction.
5.7 · Pharyngitis and its sequelae
Viral pharyngitis Routine
Gives itself away by: 70% of pharyngitis · COUGH, rhinitis, conjunctivitis · herpangina — ulcerative vesicles over the tonsils
- Presentation & who gets it
- 70% of pharyngitis. Adenovirus, Epstein-Barr virus, herpes simplex, HIV, influenza, parainfluenza, rhinovirus, coronavirus, echovirus, enteroviruses, coxsackievirus. Sore throat with earache or headache, cough, rhinitis, laryngitis, hoarseness, fever, conjunctivitis, lymphadenopathy. Herpangina is ulcerative vesicles over the tonsils.
- Pain / where it sits / key finding
- Yes — sore throat · Pharynx · Cough, rhinitis and conjunctivitis alongside
- Testing & cause
- Clinical — no further testing.
- First-line treatment
- Supportive: hydration, antipyretics, analgesia.
- Education & prognosis
- The presence of cough and coryza is what argues against streptococcal disease, and it is a Centor point.
Slides 70, 72
Bacterial pharyngitis (GABHS) Urgent
Gives itself away by: Group A beta-hemolytic Streptococcus · fever, exudate, tender nodes and NO COUGH
- Presentation & who gets it
- 30% of pharyngitis; the commonest bacterial cause is group A beta-hemolytic Streptococcus. Common in adolescents and children but not under 3 years. Peaks in winter and spring; droplet spread; incubation 2–5 days. Fever above 100.4 °F, sore throat, cervical lymphadenopathy, dysphagia, odynophagia, LACK OF COUGH, abdominal pain. Tonsillar and pharyngeal erythema with purulent exudate.
- Pain / where it sits / key finding
- Yes · Tonsils and pharynx · Exudate, fever, tender nodes and NO cough
- Testing & cause
- Rapid antigen detection test; in children and adolescents a negative rapid test is confirmed with a throat culture (the slide says “always”; adults usually need no backup culture). The slide calls antistreptolysin O the definitive test because carriers culture positive while asymptomatic, but the titer rises over weeks: it shows recent past infection, as in rheumatic fever, and does not diagnose an acute sore throat. Centor criteria (slide 76): age 3–14 +1, age 15–44 0, age 45 or over −1; absence of cough +1; tonsillar exudate +1; fever +1; tender anterior cervical lymphadenopathy +1.
- First-line treatment
- Symptomatic care plus antibiotics: penicillin VK for 10 days, or amoxicillin. Intramuscular penicillin G if compliance or oral intake is a concern. Mild penicillin allergy: cephalexin or cefadroxil. Severe allergy: macrolides or clindamycin.
- Education & prognosis
- Treatment is as much about preventing rheumatic fever as about the sore throat.
Slides 73–77
Rheumatic fever Urgent
Gives itself away by: Sequela of untreated GABHS · appears 2–3 weeks after · peak ages 5–15
- Presentation & who gets it
- A rare complication of untreated group A beta-hemolytic streptococcal infection, from cross-reactive antibodies produced against the streptococcus that attack heart muscle — endocarditis, myocarditis or pericarditis. Signs appear 2 to 3 weeks after the infection, sometimes as early as one week or as late as five. Peak incidence between 5 and 15 years; rare before 4 and after 40. Typically resolves after about six weeks.
- Pain / where it sits / key finding
- Varies · Heart, joints, skin · 2–3 weeks after an untreated strep throat
- Testing & cause
- Clinical, against the Jones criteria (slide 79), with evidence of preceding streptococcal infection.
- First-line treatment
- Treat and eradicate the streptococcal infection; manage the carditis.
- Education & prognosis
- This is the reason a sore throat gets an antibiotic at all — the throat would settle without one.
Slides 78–79
Chronic pharyngitis Routine
Gives itself away by: Constant throat clearing · thickened, granular pharyngeal wall with crusting
- Presentation & who gets it
- Causes: postnasal drip from chronic rhinosinusitis, irritants (dust, dry heat, chemicals, smoking, alcohol), chronic mouth breathing, voice abuse, allergy, granulomatous disease, connective tissue disorder, malignancy. Constant throat clearing, dry throat, odynophagia, a thickened and granular pharyngeal wall, and pharyngeal crusting.
- Pain / where it sits / key finding
- Mild · Pharyngeal wall · Thickened, granular wall with crusting
- Testing & cause
- Clinical; culture and biopsy if treatment fails.
- First-line treatment
- Address the underlying disorder, avoid precipitants, treat symptoms.
- Education & prognosis
- Malignancy is on the causes list, so failed therapy earns a biopsy rather than another course of something.
Slides 80
Infectious mononucleosis Urgent
Gives itself away by: Triad: fever, tonsillar pharyngitis, cervical lymphadenopathy · 15–24 years · splenomegaly
- Presentation & who gets it
- Highly contagious; 90–95% of adults are Epstein-Barr virus seropositive. Commonly 15 to 24 years. Spread by oral contact or infected saliva. Epstein-Barr virus in 90%, cytomegalovirus and others in 10%. Prodrome of malaise, headache and low-grade fever — or asymptomatic under 10 years. Triad of fever, tonsillar pharyngitis with or without exudate, and cervical lymphadenopathy. Also palatal petechiae, hepatomegaly, splenomegaly, and a maculopapular rash in 5%.
- Pain / where it sits / key finding
- Yes · Tonsils and cervical nodes · Fever, tonsillar pharyngitis, cervical adenopathy plus splenomegaly
- Testing & cause
- Clinical plus confirmation. Monospot / heterophile antibody test is very sensitive and specific — positive means no further testing, but it can be falsely negative in the first week, because heterophile antibodies take about a week to develop. Slide 84 prints “falsely positive”, which is an error. Prof. Shah read it as written at [1:45:26], a student asked whether it was supposed to say false negative, and she confirmed it at [1:47:49]. Minutes earlier she had taught the false-negative pathway herself: “you order that monospot test and you’re like, hold on, that came back NEGATIVE but this patient walks and talks like they have mono… serology will help you”. The same slide already contradicts itself: it sends you to serology for a negative heterophile test in suspected mono, which is the false-negative pathway. Serology: IgG means past infection, IgM means current; useful under 4 years, with a negative heterophile test, or with atypical symptoms. Polymerase chain reaction detects viral DNA.
- First-line treatment
- Supportive — there is no antiviral therapy. Corticosteroids for severe respiratory compromise. Avoid heavy lifting and contact sports for about a month, until the splenomegaly has resolved, to prevent splenic rupture.
- Education & prognosis
- Giving penicillin triggers an exanthem — the classic sequence is a sore throat treated as strep, a rash, and then the real diagnosis.
Slides 81–87
Diphtheria Emergent
Gives itself away by: Tenacious GRAY MEMBRANE over tonsils and pharynx · unimmunized child
- Presentation & who gets it
- Corynebacterium diphtheriae, attacking the respiratory tract and sometimes mucous membrane or skin wounds, spread by respiratory secretions. Nasal, laryngeal, pharyngeal (commonest) and cutaneous forms. Common in unimmunized children over 6 years. Nasal: discharge. Laryngeal: upper airway and bronchial obstruction. Pharyngeal: a tenacious gray membrane covering tonsils and pharynx, with mild sore throat, fever, malaise, toxemia and prostration. Complications: myocarditis (arrhythmia, heart block, failure) and neuropathy involving cranial nerves first — diplopia, slurred speech, difficulty swallowing.
- Pain / where it sits / key finding
- Mild sore throat · Tonsils and pharynx · Tenacious gray membrane
- Testing & cause
- Clinical, confirmed by culture. Differentiate from streptococcal pharyngitis, mononucleosis, adenovirus, herpes simplex and candidiasis.
- First-line treatment
- Laryngoscopy or bronchoscopy to prevent or relieve obstruction. Antitoxin for all — obtained from the Centers for Disease Control. Penicillin 250 mg four times daily or erythromycin 500 mg four times daily for 14 days. Isolate until three consecutive cultures after therapy are negative. Treat contacts with erythromycin for 7 days.
- Education & prognosis
- Prevention is immunization: childhood schedule plus boosters, and Tdap in every pregnancy between 27 and 36 weeks.
Slides 112–114
Also tested
- Pharyngitis, tonsillitis, pharyngotonsillitis. The terms name which structure is inflamed: tonsillitis if the tonsils, pharyngitis if the throat, pharyngotonsillitis if both. They are not different diseases and the same organisms cause all; tonsillar involvement raises the possibility of peritonsillar abscess.
- Monospot timing. The test can be falsely negative early in the illness, in the first week, because antibodies take time to appear; serology for Epstein-Barr antibodies is then used. A positive result needs no further testing.
- Negative rapid antigen test. In a child with high clinical probability, send a throat culture before deciding about antibiotics; rapid antigen tests are specific but not sufficiently sensitive, so a negative result is confirmed by culture.
- Rash after an aminopenicillin for sore throat. Infectious mononucleosis, with the aminopenicillin triggering a widespread exanthem; fever, tonsillar pharyngitis and cervical lymphadenopathy fit mononucleosis rather than streptococcus.
- Cause of pharyngitis. About 70 percent is viral; the remaining 30 percent is bacterial, chiefly group A beta-hemolytic streptococcus.
- Viral pharyngitis. Cough, hoarseness, rhinitis and conjunctivitis point to viral pharyngitis, about 70 percent of cases; with a minimal Centor score, management is supportive care with no further testing (hydration, antipyretics, analgesia), and antibiotics are not indicated.
- Infectious mononucleosis. Tonsils so enlarged that they nearly meet, under a thick gray-white membranous exudate.
- Epstein-Barr virus serology. A positive IgM indicates current infection, since IgM appears during acute infection, while a positive IgG means past infection, since IgG persists. Serology is particularly useful in patients under four years, with a negative heterophile test, or with atypical symptoms.
5.8 · Deep neck infections
Cervical adenitis Urgent
Gives itself away by: A SIGN, NOT A DIAGNOSIS · typically unilateral, solitary, anterior node
- Presentation & who gets it
- Inflammation of a lymph node, often used synonymously with lymphadenopathy. Cervical lymphadenopathy is a sign, not a diagnosis. Infectious causes include toxoplasmosis, tuberculosis, brucellosis, primary herpes simplex, syphilis, cytomegalovirus, HIV, histoplasmosis and chickenpox; also inflammatory, degenerative and neoplastic causes. The typical case is a unilateral, solitary, anterior cervical node: about 70% beta-hemolytic streptococcus, 20% staphylococcus including MRSA, 10% viruses, atypical mycobacteria and Bartonella henselae.
- Pain / where it sits / key finding
- Varies — tender means inflammatory · Anterior cervical node · Unilateral solitary node; immobile suggests malignancy
- Testing & cause
- Response to specific antibiotics can help confirm or exclude. Fine needle aspiration if the node persists or keeps enlarging — that can signal malignancy. Describe size, shape, mobility (immobile suggests malignancy), consistency and tenderness (tender = inflammatory, non-tender = malignancy).
- First-line treatment
- Treat the underlying cause. Incision and drainage if there is an abscess.
- Education & prognosis
- Scarred nodes may stay palpable long after the infection has gone, which is not failure.
Slides 91–94
Peritonsillar abscess (quinsy) Emergent
Gives itself away by: Classic triad: TRISMUS, UVULAR DEVIATION, DYSPHONIA · “hot potato” voice
- Presentation & who gets it
- Purulence between the capsule of the palatine tonsil and the pharyngeal muscles, beginning as a complication of untreated strep throat or tonsillitis. The commonest deep infection of the head and neck, especially in young adults, adolescents and children; commoner in males. Aerobes: group A beta-hemolytic streptococcus, Staphylococcus aureus, Haemophilus influenzae. Anaerobes: Prevotella, Porphyromonas, Fusobacterium, Streptococcus. Severe sore throat, fever, odynophagia, medial deviation of the soft palate and peritonsillar fold, uvular deviation, hot potato voice, trismus, dysphagia.
- Pain / where it sits / key finding
- Severe · Between tonsil capsule and pharyngeal muscle · Trismus, uvular deviation, hot potato voice
- Testing & cause
- Clinical, confirmed by the purulent drainage obtained. Contrast computed tomography shows the extent; ultrasound distinguishes abscess from cellulitis and can guide needle aspiration.
- First-line treatment
- Secure the airway first if needed. Needle aspiration and incision and drainage. Antibiotics: parenteral amoxicillin-clavulanate or clindamycin, adding MRSA cover if severe; oral if tolerated. Tonsillectomy for recurrent tonsillitis and recurrent abscesses, usually after the acute infection settles — quinsy tonsillectomy during infection is occasional.
- Education & prognosis
- Trismus is the most reliable symptom; the dysphonia comes from vagus nerve involvement failing to elevate the palate.
Slides 96–101
Retropharyngeal abscess Emergent
Gives itself away by: SURGICAL EMERGENCY · child under 5 · widened retropharyngeal space on lateral neck X-ray
- Presentation & who gets it
- An abscess in the retropharyngeal space, running from the base of skull to the posterior mediastinum. May spread from a peritonsillar abscess or from a node in that space. Commoner in children under 5 after upper respiratory infection, otitis media or sinusitis; in adults it follows intraoral procedures, trauma, foreign bodies such as fishbone, immunocompromise or odontogenic spread. Group A beta-hemolytic streptococcus, Staphylococcus aureus, Haemophilus influenzae, mixed flora. Early: fever, sore throat, pharyngeal erythema, dysphagia, odynophagia, neck stiffness, trismus. Late: ill appearance, drooling, leaning forward with the neck extended, respiratory distress.
- Pain / where it sits / key finding
- Yes · Retropharyngeal space · Widened retropharyngeal space on lateral X-ray
- Testing & cause
- Labs; lateral neck X-ray shows a widened retropharyngeal space; lateral neck computed tomography is the gold standard, showing a rim-enhancing hypodense collection. Distinguishing abscess from adenitis is the point.
- First-line treatment
- Protect the airway. Surgical emergency. Antibiotics covering streptococci, anaerobes and Staphylococcus aureus: ampicillin-sulbactam, or clindamycin with ceftriaxone; vancomycin or linezolid if not improving; switch to oral on clinical improvement.
- Education & prognosis
- Mediastinitis carries 50% mortality. Other complications: respiratory distress, rupture with aspiration pneumonia, and spread into the danger space, which is continuous left to right and leads directly to the thorax.
Slides 103–107
Ludwig angina Emergent
Gives itself away by: EMERGENCY · floor of mouth, submental, sublingual and submandibular spaces · TONGUE PUSHED UP AND BACK
- Presentation & who gets it
- A severe infection of the floor of the mouth and the submental, sublingual and submandibular spaces. Can rapidly compromise the upper airway and force a surgical airway. Streptococci, staphylococci, Bacteroides, Fusobacterium, Klebsiella — the last usually in patients with diabetes, who have a more aggressive course. Edema and erythema of the upper neck under the chin and the floor of the mouth; the tongue is displaced upwards and backwards by posterior spread of cellulitis; pus coalescing at the floor of the mouth.
- Pain / where it sits / key finding
- Yes · Floor of mouth, submental and submandibular · Tongue displaced up and back
- Testing & cause
- Computed tomography with contrast, to separate inflammation and phlegmon from abscess and define the extent for the surgeon.
- First-line treatment
- Antibiotics: penicillin with metronidazole, ampicillin-sulbactam, clindamycin, or selected cephalosporins. External drainage via bilateral submental incision if the airway is threatened or medical therapy fails. Dental consultation to deal with the offending tooth.
- Education & prognosis
- It is usually odontogenic, which is why the dental referral is part of the treatment rather than an afterthought.
Slides 108–111
Also tested
- Cervical node features suggesting malignancy. Immobility (fixation to surrounding structures by tumor) and non-tenderness (inflamed nodes hurt) suggest malignancy. Persistence or continued enlargement triggers fine needle aspiration.
- Unilateral solitary anterior cervical node. Beta-hemolytic streptococcus accounts for about 70 percent, about 20 percent are staphylococcal including MRSA, and 10 percent are viral, atypical mycobacterial or Bartonella.
- Ludwig angina in diabetes. Klebsiella is more often involved in patients with diabetes, and those patients may have a more aggressive clinical course.
- Retropharyngeal abscess. The space extends to the posterior mediastinum, giving infection a direct route into the chest; mediastinitis carries a 50 percent mortality.
- Recurrent tonsillitis with peritonsillar abscesses. Tonsillectomy is indicated, usually after the acute infection resolves, because the tissue planes are cleaner and bleeding is less.
- Ludwig angina. This rapidly spreading cellulitis of the submental, sublingual and submandibular spaces swells the floor of the mouth and pushes the tongue up and back into the airway, so secure the airway, then antibiotics (penicillin and metronidazole, or ampicillin-sulbactam), with external drainage through bilateral submental incisions if needed.
- Peritonsillar abscess. Asymmetry is the finding: one side bulges medially and the uvula is displaced away from it.
- Retropharyngeal abscess complications. Mediastinitis carries a 50 percent mortality because the space extends from the base of the skull to the posterior mediastinum; other complications are respiratory distress, rupture with aspiration pneumonia, and spread into the danger space.
- Peritonsillar abscess. Limited mouth opening is called trismus, caused by pus tracking beside the medial pterygoid and irritating it into spasm; it is the most reliable of the triad of trismus, uvular deviation and dysphonia, and makes examination and drainage difficult.
5.9 · Dentition and the jaw
Dental abscess Urgent
Gives itself away by: Pus inside the tooth or gums · from bacterial infection of the soft pulp
- Presentation & who gets it
- A build-up of pus inside the teeth or gums, from bacterial infection accumulating in the soft pulp of the tooth. Slide 116 divides them into periapical (at the root tip), gingival (in the space between gum and tooth), periodontal (in a periodontal pocket) and pericoronal (around an impacted or partially erupted tooth).
- Pain / where it sits / key finding
- Yes · Tooth pulp or gum · Periapical, gingival, periodontal or pericoronal pus
- Testing & cause
- Clinical, with dental imaging.
- First-line treatment
- Antibiotics — amoxicillin, ampicillin-sulbactam, amoxicillin-clavulanate, azithromycin, clindamycin, erythromycin, cephalexin, metronidazole, penicillin VK. Incision and drainage. Root canal if the tooth can be restored; extraction with curettage of apical tissue if it cannot.
- Education & prognosis
- Untreated, infection from a tooth can spread to the jaw, the brain or the sinus — and Ludwig angina is the neck version of that spread.
Slides 116–117
Dental caries, pulpitis and periapical abscess Urgent
Gives itself away by: Tooth decay is the commonest cause; injury second · severe inflammation kills the pulp
- Presentation & who gets it
- Common teeth diseases are cavities, pulpitis, periapical abscess, impacted teeth and malocclusion. The commonest cause of pulpitis and periapical abscess is tooth decay, and the second commonest is injury. Mild inflammation, if relieved, may not damage the pulp permanently; severe inflammation kills it. Pulpitis can lead to a pocket of pus at the root — a periapical abscess.
- Pain / where it sits / key finding
- Yes · Tooth · Decay first, injury second
- Testing & cause
- Clinical and dental imaging.
- First-line treatment
- Dental treatment of the decay; root canal or extraction as for dental abscess.
- Education & prognosis
- Untreated, infection from a tooth can spread to the jaw or beyond — brain or sinus.
Slides 123–124
Gingivitis and periodontitis Routine
Gives itself away by: Gums erythematous, edematous and BLEED EASILY with little discomfort · gingivitis is REVERSIBLE
- Presentation & who gets it
- Chronic infection of the gingiva beginning with bacterial plaque at the gum line. Gingivitis is the mildest form: erythematous, edematous gums that bleed easily, with little or no discomfort, caused by inadequate oral hygiene — and reversible with professional treatment and good home care. Untreated it becomes periodontitis: plaque spreads below the gum line, bacterial toxins provoke a chronic inflammatory response in which the body turns on itself, gums separate from teeth, pockets form and become infected, the periodontal ligament and bone are destroyed, and teeth loosen and fall out. Risk: diabetes, smoking, aging, genetics, stress, poor nutrition, puberty, pregnancy, substance abuse, HIV and certain medications. Gram-negative organisms.
- Pain / where it sits / key finding
- Little to none · Gum line · Gums bleed easily; gingivitis is reversible
- Testing & cause
- Clinical and dental examination.
- First-line treatment
- Professional cleaning and oral hygiene — brushing, flossing, mouthwash — and modifying risk.
- Education & prognosis
- Periodontal disease and dental caries are the primary causes of tooth loss. The slides also link gum disease to endocarditis risk, pneumonia, osteoporosis and, in men, kidney, pancreatic and blood cancers.
Slides 118–122
Impacted teeth Routine
Gives itself away by: Overcrowding · wisdom teeth are the usual ones · more likely to become infected
- Presentation & who gets it
- Impaction is usually caused by overcrowding and insufficient room for a new tooth to emerge. Wisdom teeth are the usual culprits, being the last permanent teeth to erupt into a jaw that may not accommodate them. Impacted teeth are more likely to become infected.
- Pain / where it sits / key finding
- Varies · Usually wisdom teeth · Overcrowding with no room to erupt
- Testing & cause
- Clinical and dental imaging.
- First-line treatment
- Usually removed — they are of little use in chewing.
- Education & prognosis
- A pericoronal abscess is the complication that links this row to the dental abscess row.
Slides 125
Malocclusion Routine
Gives itself away by: Abnormal alignment of teeth and bite · Class I, II and III
- Presentation & who gets it
- Abnormal alignment of the teeth and the way upper and lower teeth fit together. Normal chewing produces about 150 lb of force on the molars, and about 250 lb when clenching during sleep; if that force is unevenly distributed, teeth wear, fracture or loosen. Causes: size mismatch between jaw and teeth, thumb sucking or tongue thrusting, lost teeth, birth defects. Slide 126 illustrates Class I normal occlusion, Class II distal occlusion and Class III mesial occlusion.
- Pain / where it sits / key finding
- No · Bite · Class I, II or III occlusion
- Testing & cause
- Clinical and dental assessment.
- First-line treatment
- Braces or aligners, removal of teeth, or surgery.
- Education & prognosis
- The force numbers are the reason a bite problem becomes a structural one.
Slides 126
Temporomandibular joint disorders Routine
Gives itself away by: Second commonest musculoskeletal cause of pain and disability · jaw pain with clicking, popping or locking
- Presentation & who gets it
- Disorders affecting the temporomandibular joint, the masticatory muscles, or both. The second commonest musculoskeletal condition causing pain and disability. Common in women of childbearing age, with a possible link to female sex hormones. Predisposing: trauma — a blow to the jaw or whiplash — and stress, which disrupts sleep and increases nocturnal bruxism. Perpetuated by stress, poor coping, clenching and grinding, and poor posture. Three categories: myofascial pain, internal derangement (displaced disc, dislocated jaw, condylar injury), and arthritis. Jaw, face and head pain; limited opening, catching or locking; clicking, popping or grating; headache, neck and shoulder pain; tinnitus, ear fullness, hearing loss, dizziness; abnormal tooth wear and sensitivity.
- Pain / where it sits / key finding
- Yes · Temporomandibular joint and muscles · Clicking, popping or locking with limited opening
- Testing & cause
- Clinical. Computed tomography or magnetic resonance imaging is reserved for abnormal pain or dysfunction not responding to short-term therapy, or a sudden change in bite or mandibular asymmetry.
- First-line treatment
- Eliminate pain and restore function: self care; non-steroidal anti-inflammatories, muscle relaxants (cyclobenzaprine), low-dose tricyclics (amitriptyline, desipramine, nortriptyline); oral steroids if there is synovitis; physical therapy, transcutaneous electrical nerve stimulation, acupuncture, local anesthesia, mouth guards, arthrocentesis, arthroscopy, surgery.
- Education & prognosis
- The ear symptoms are the trap — tinnitus, fullness and dizziness send these patients to an ear examination that is normal.
Slides 128–131
Also tested
- Dental abscess in an unrestorable tooth. Extraction followed by curettage of the apical tissue, because leaving infected granulation tissue behind lets infection persist in the socket.
- Periodontal disease. It raises the risk of endocarditis and other systemic disease, including pneumonia and decreased bone density, and with caries is a primary cause of tooth loss.
5.10 · Lesions of the oral cavity
Oral candidiasis (thrush) Routine
Gives itself away by: Creamy white curd-like patches that WIPE OFF, leaving an erythematous base
- Presentation & who gets it
- Candida albicans; Aspergillus may also be cultured. Common in infants and the immunosuppressed. Risk factors: dentures, poor oral hygiene, diabetes, anemia, chemotherapy or local irradiation, corticosteroids, broad-spectrum antibiotics, age, HIV. Creamy white curd-like patches on an erythematous base, painful, granular, usually on buccal mucosa and tongue, with fever, lymphadenopathy, odynophagia and taste change.
- Pain / where it sits / key finding
- Yes · Buccal mucosa and tongue · White patches that RUB OFF
- Testing & cause
- Clinical. Potassium hydroxide preparation shows spores and pseudohyphae.
- First-line treatment
- Saline and peroxide washes; topical antifungals — nystatin suspension, clotrimazole, ketoconazole, fluconazole. HIV patients may need longer fluconazole; refractory disease needs itraconazole or voriconazole.
- Education & prognosis
- The patches rub off with a tongue depressor. Leukoplakia and lichen planus do not — that single maneuver separates three diagnoses.
Slides 88–90
Oral leukoplakia Urgent
Gives itself away by: White lesion that CANNOT be scraped off · premalignant — 5–20% become squamous cell carcinoma
- Presentation & who gets it
- A premalignant squamous lesion: altered epithelium at increased risk of progression to squamous cell carcinoma, 5–20%. Defined as a white lesion of the oral mucosa that cannot be scraped off and cannot be attributed to another definable lesion. Causes include chronic irritation, smoking and infection.
- Pain / where it sits / key finding
- No · Oral mucosa · White and CANNOT be scraped off
- Testing & cause
- Excisional biopsy to rule out malignancy. Complete intraoral examination and palpation for lymphadenopathy.
- First-line treatment
- Observation after eliminating carcinogenic irritants — smoking, chewing tobacco, alcohol — with serial biopsies and excisions.
- Education & prognosis
- The scrape test is the bedside discriminator: candidiasis wipes off, leukoplakia does not.
Slides 133–134
Erythroplakia Emergent
Gives itself away by: Like leukoplakia but RED · 90% are dysplastic or carcinoma · far more dangerous
- Presentation & who gets it
- As leukoplakia but with an erythematous component. 90% are either dysplastic or already carcinoma, and the risk of malignancy is around 25% — substantially higher than leukoplakia. Alcohol and tobacco are the major risk factors.
- Pain / where it sits / key finding
- No · Oral mucosa · Red — 90% dysplastic or carcinoma
- Testing & cause
- As for leukoplakia — excisional biopsy.
- First-line treatment
- As for leukoplakia, but the threshold for excision is lower.
- Education & prognosis
- Red is worse than white. If one lesion on the slide deck earns urgency, it is this one.
Slides 133, 135
Hairy leukoplakia Urgent
Gives itself away by: Painless LATERAL TONGUE lesion that waxes and wanes · EBV · strongly associated with HIV
- Presentation & who gets it
- Benign mucosal hyperplasia associated with Epstein-Barr virus, long-term systemic corticosteroids and solid organ transplantation. Strongly associated with HIV and a common early finding in HIV infection. Painless lateral tongue lesions that wax and wane over time.
- Pain / where it sits / key finding
- No — painless · Lateral tongue · Waxes and wanes; think HIV
- Testing & cause
- Clinical and biopsy.
- First-line treatment
- Observation. Acyclovir, valacyclovir or famciclovir produce temporary resolution.
- Education & prognosis
- The lesion itself is benign; its value is as a pointer to undiagnosed HIV.
Slides 136
Also tested
- Oral thrush in infants. Common because immune systems and oral flora are still establishing; topical antifungal therapy is the first step, using nystatin oral suspension, which acts locally with negligible systemic absorption.
5.11 · Neoplasms
Salivary gland neoplasm Urgent
Gives itself away by: Slow-growing PAINLESS mass at the TAIL OF THE PAROTID · the smaller the gland, the likelier it is malignant
- Presentation & who gets it
- 64–80% arise in the parotid, and 75–80% of those are benign. 7–15% submandibular, 50–60% benign. 1% sublingual. About 15% are minor salivary gland, and only 35% of those are benign. Most benign parotid tumors are epithelial; in minor glands the commonest is pleomorphic adenoma, then basal cell adenoma. Malignant disease is 3–4% of head and neck malignancy; mucoepidermoid carcinoma is the commonest, and in minor glands adenoid cystic carcinoma and adenocarcinoma. No specific risk factors are known. Benign parotid tumors are slow-growing painless masses often at the tail of the parotid.
- Pain / where it sits / key finding
- No — painless · Tail of the parotid · Slow-growing painless mass; pain suggests malignancy
- Testing & cause
- Fine needle aspiration is less specific and sensitive here than for other tumors, though it helps separate malignant from benign. Diffusion-weighted magnetic resonance imaging or computed tomography helps with deep lobe tumors.
- First-line treatment
- Benign: complete surgical excision, no radiation. Malignant: surgical removal, radiotherapy for T1 and T2, palliative chemotherapy. Complications include recurrence with positive margins and transient or permanent facial paralysis.
- Education & prognosis
- Prognosis is poor with pain, facial or other nerve involvement, high-grade histology, skin or tissue invasion, or recurrent disease.
Slides 139–143
Oral cavity and oropharyngeal cancer Emergent
Gives itself away by: NON-HEALING ULCER · tobacco and alcohol · referred otalgia and ill-fitting dentures in advanced disease
- Presentation & who gets it
- Oral cavity means the anterior two thirds of tongue, buccal mucosa, floor of mouth, hard palate, upper and lower gingiva and retromolar trigone — the lip is no longer part of the oral cavity under the 8th staging system. Oropharynx means posterior third of tongue, palatine tonsil, soft palate and posterior pharyngeal wall. Males are 2–4 times more likely for oral cavity and 3–5 times for oropharyngeal. 60–80% of oropharyngeal cancer is human papillomavirus related; 90% of oral cavity cases relate to chronic sun exposure. Mean age 62. Risks: tobacco chewed and smoked, alcohol, betel nut, poor oral hygiene, immunosuppression. Squamous cell carcinoma is commonest; lymphoma is the second commonest tumor of the tonsillar fossa. Non-healing ulcers, bleeding, pain, ill-fitting dentures; advanced: dysarthria, dysphagia, neck mass, referred otalgia from cranial nerve involvement; tonsillar lesions give odynophagia and trismus.
- Pain / where it sits / key finding
- Varies · Tongue, floor of mouth, tonsil · Non-healing ulcer with referred otalgia
- Testing & cause
- Labs including high-risk human papillomavirus testing and in situ hybridization; computed tomography or magnetic resonance imaging for the primary and nodes; chest X-ray and positron emission tomography for metastases; flexible fiberoptic endoscopy; biopsy; dental evaluation.
- First-line treatment
- Surgical resection alone for oral cavity; resection plus radiotherapy for oropharyngeal, where radiotherapy gives better functional outcomes.
- Education & prognosis
- Prevention is tobacco and alcohol cessation. An ulcer that has not healed is the symptom that should never be watched.
Slides 144–148
Also tested
- Salivary tumors and gland size. The smaller the gland, the higher the proportion that are malignant: parotid tumors are 75 to 80 percent benign, submandibular 50 to 60 percent, and minor salivary gland tumors only about 35 percent.
- Glottic tumor. Hoarseness is the expected and usually earliest symptom, since a mass replacing the true vocal cord prevents normal vibration and apposition. Referred ear pain reflects shared vagal innervation between the larynx and the ear.
- Oral cancer risk factors. Risk factors are tobacco chewed and smoked, alcohol, betel nut chewing, poor oral hygiene and immunosuppression. Squamous cell carcinoma is the commonest malignancy of the oral cavity and oropharynx, and prevention rests on tobacco and alcohol cessation.
- Oral or oropharyngeal malignancy. Suspect possible oral or oropharyngeal malignancy when ill-fitting dentures accompany non-healing ulcers, bleeding, pain, vague discomfort or a foreign body sensation in the throat.
- Salivary gland tumor prognosis. A parotid mass with pain and facial nerve palsy suggests a malignant salivary tumor, with a poor prognosis. Prognosis is poor with pain, facial or other nerve involvement, high-grade histology, skin or tissue invasion, or recurrent disease; facial nerve palsy indicates invasion rather than compression.